Tag Archive for: Treatment of Bulky Uterus

Enlarged Uterus: Causes, Symptoms, and Treatment

Introduction to Enlarged Uterus

Enlarged Uterus – The uterus is a hollow organ in the pelvis and comprises two parts: the endometrium, which thickens during pregnancy, and the myometrium, which supports the uterus internally. Three layers comprise the uterus: the innermost layer is called the glandular or functional layer; this portion of the uterine wall secretes mucus and blood vessels that feed the endometrium.

The middle layer is called the serous or storage layer; this portion of the uterine wall stores blood in case of anemia. Finally, there is an outermost layer called muscular or adventitial; this portion of the uterine wall helps support and shape the uterus. A woman’s reproductive organs comprise her cervix, vagina, fallopian tubes, and ovaries (the ovary).

The term “enlarged uterus” describes a condition in which the size of the endometrium (uterine lining) increases beyond normal limits. The syndrome may start after menopause or present at birth and last for the rest of one’s life. Significant uterus syndrome is sometimes called leiomyomata.

The most common cause of significant uterus syndrome is an inherited disorder called uterine leiomyoma (unlike fibroids, leiomyomas are not cancerous). Leiomyomas are usually benign tumors composed of smooth muscle cells which frequently line the uterus’ interior. They can grow and increase over time, resulting in a larger uterus with an enlarged endometrium.

The most common cause of infertility is an enlarged uterus (endometriosis). An enlarged uterus can occur due to pelvic inflammatory disease (PID), endometriosis, or adenomyosis (a condition in which endometrial tissue grows outside of the uterus). 

Causes of Enlarged Uterus
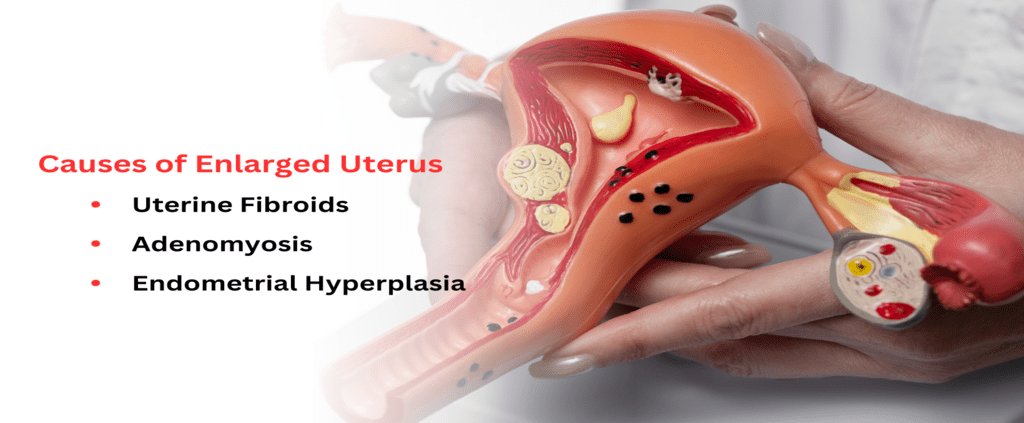
Causes of Enlarged Uterus

The common causes of an enlarged uterus may be medical illnesses in the background, like polycystic ovarian syndrome (PCOS), endometriosis, or pelvic inflammatory disease (PID). However, other factors, such as excessive weight gain or breastfeeding, can play a role occasionally.

1. Uterine Fibroids

Fibroids are benign tumors that usually occur in the uterus, although they can sometimes be found elsewhere in the body. The fibroid may be a single tumor, or it may consist of several smaller tumors. Fibroids can cause pain at the time of menstruation, as well as abnormal bleeding and other problems. If a woman thinks she has fibroids, she should see her doctor to get checked out.

2. Adenomyosis

Adenomyosis is when the muscle layer around your uterus becomes thick and lumpy instead of smooth and elastic like normal muscle tissue. This can cause problems with your periods and make them irregular or heavy, possibly leading to anemia or blood clots that may cause a stroke or a heart attack.

If you have adenomyosis, you may also experience painful cramps or bleeding between periods or irregular intervals during your cycle. Your doctor will check for adenomyosis based on the symptoms you report, your medical History, and any physical exam findings he observes during an exam of your cervix (the lower part of your uterus).

3. Endometrial Hyperplasia

Endometrial hyperplasia can develop if a woman has multiple risk factors for endometrial cancer, such as:

  1. Women after 35 years of age.
  2. Previous History of breast cancer
  3. History of blood clots in your veins (deep-vein thrombosis)
  4. Family history of endometrial cancer
  5. A family history of uterine polyps

Symptoms and Impact on Fertility
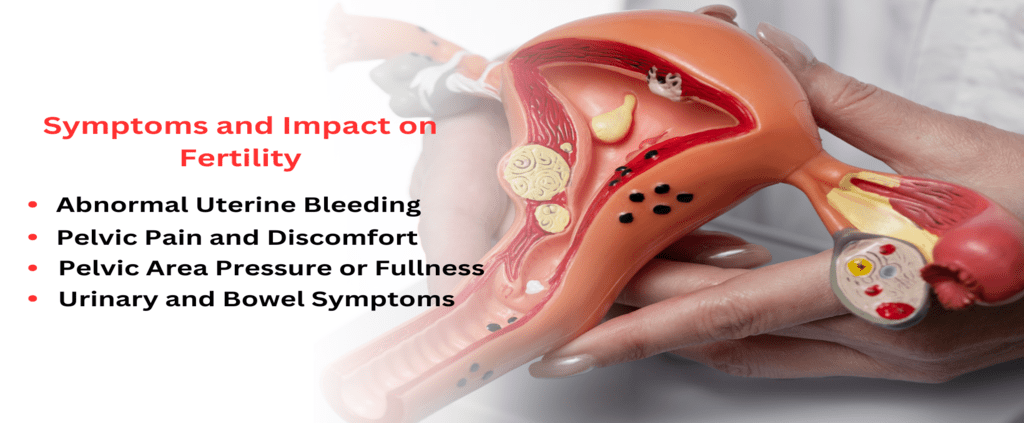
Symptoms of Enlarged Uterus

1. Abnormal Uterine Bleeding

Abnormal uterine bleeding can be a sign of an enlarged uterus. This is also known as menorrhagia. It occurs because the blood flow to the uterus is restricted due to an enlarged uterus. In most cases, it happens due to pregnancy and childbirth. An enlarged uterus may be to blame for lower back or abdomen pain and bleeding between periods.

2. Pelvic Pain and Discomfort

If your uterus has grown too large for its good, it may press against other organs in your pelvis (it comprises two bones: ilium and pubic bone). This pressure can cause pelvic pain, back pain, and lower abdominal discomfort. Another symptom is constipation due to pressure on the rectum from the enlarged uterus pressing against it during childbirth or periods (for example, during menopause).

3. Pelvic Area Pressure or Fullness

Pelvic pain and discomfort are common complaints of women with enlarged uteri. This can be due to pressure or fullness in the pelvis and may also result in spasms or cramping that can be uncomfortable for both you and your doctor to deal with. 

4. Urinary and Bowel Symptoms

Urinary and bowel symptoms such as urgency, frequency, incontinence (leakage) of urine or stool, constipation, painful urination; sexual dysfunction including vaginal dryness or pain during intercourse

Diagnosing an Enlarged Uterus

1. Medical History and Examination

The medical history and physical examination should focus on ruling out pregnancy, fibroids, and cancer. Medical History includes:

  • History of recent illnesses, injuries, or surgeries that may have affected the uterus.
  • Any current or past health conditions may affect fertility or pregnancy, such as diabetes and high blood pressure.
  • The woman’s age, race, and medical History should be considered when diagnosing a possible enlarged uterus since the condition is more common in older women than in young women.

2. Imaging Tests

The diagnosis is usually benign if an ultrasound shows an enlarged uterus with a thin wall. However, if there is no evidence of pregnancy (e.g., vaginal bleeding or missed period), the diagnosis may be more likely to be uterine fibroids or endometriosis. In this case, a laparoscopy may be performed to confirm the diagnosis and remove any fibroids if they are found during surgery. An MRI may also help assess the embryo’s viability so that it can be frozen for future use if needed.

3. Biopsy or Sampling

A biopsy sample can be obtained with laparoscopy; however, there are risks involved in obtaining this type of tissue (invasive surgery).

Treatment Options for Enlarged Uterus and Infertility
Treatment of Enlarged Uterus

1. Uterine Fibroids

Uterine fibroids are benign tumors that grow in the fibrous lining of the uterus. Numerous symptoms, such as painful or irregular periods, heavy menstrual flow, pain during sex, or bowel motions, might be brought on by them. If fibroids push on the Fallopian tubes and prevent them from carrying eggs from the ovary to the uterus, this can also result in infertility.

2. Adenomyosis

Adenomyosis is when the lining of the uterus becomes thicker than usual and grows into adjacent tissues. The condition may cause infertility, abdominal pain, and urinary symptoms such as an increased need to urinate and blood in the urine.

3. Endometrial Hyperplasia

Endometrial hyperplasia is a disorder when the lining of the uterus experiences an increase in cells, thickening and expanding abnormally. Women with endometrial hyperplasia may have irregular periods or heavy bleeding. 

4. Uterine Polyps

Uterine polyps are growths on the villi or fingerlike projections that line the end of the fallopian tubes — structures that carry eggs from ovaries to the uterus — or other body areas such as the cervix (neck of the womb). Polyps can cause cervical cancer if they become large enough to block the cervical opening (birth canal).

Fertility Treatment Planning and Considerations

An enlarged uterus is a common medical condition, which is more common in women of childbearing age. The uterus is the organ that holds and nourishes the developing fetus during pregnancy.

Although the exact etiology of this ailment is unknown, it could be brought on by hormone imbalances, pregnancy, tumors, growth hormones, or other factors. It usually affects women after the age of 35 and is more common in those with children.

1. Individualized Approach

For mild cases, there are no special considerations for fertility treatment. However, IVF Treatment may be considered if there is no chance of conceiving naturally. If there is a possibility of having problems conceiving later on, egg donation may be an option.

2. Collaboration with Fertility Specialists

In the case of a large size of uterus, Fertility specialists recommend surgical treatment for the removal of extra tissue or organ from the body or removing part of an organ from the body with minimized damage to surrounding tissues. The procedure has been successfully performed using laparoscopy(minimally invasive surgical technique), which provides several advantages like minimized pain during surgery, no open abdomen surgery required, and less risk of infection compared to open abdomen surgery like laparotomy.

Conclusion

It would be best to see a doctor to find the underlying cause of your enlarged uterus. Making an appointment with your gynecologist is an intelligent approach to accomplish this. Calling their office and making an appointment over the phone is an option if you cannot visit them in person.

A regular doctor will check your health history and ask questions about your menstrual cycle, fertility, family history, and other relevant information. They will also conduct a physical exam and ask you questions about your health. This way, they can look at all possible causes of your enlarged uterus and find suitable treatment options.

Why Choose Imprimis IVF for Enlarged Uterus Treatment

Imprimis IVF is ideal for enlarged uterus treatment due to its specialized expertise, advanced technology, comprehensive approach, diverse treatment options, and supportive care. Their team of experienced fertility specialists focuses exclusively on reproductive medicine, ensuring personalized and effective treatment for an enlarged uterus. Equipped with state-of-the-art facilities, Imprimis IVF provides accurate diagnosis and utilizes cutting-edge technology for optimal treatment outcomes. 

Their holistic approach considers various factors contributing to the condition, addressing underlying causes and developing individualized treatment plans. Imprimis IVF ensures that patients receive the most appropriate and effective care with a wide range of treatment options available, including medications, minimally invasive procedures, and fertility preservation techniques.

Recurrent Pregnancy Loss: Causes, Diagnosis & Treatment

Experiencing a miscarriage can be emotionally and physically difficult. While miscarriage is relatively common, recurrent pregnancy loss (RPL) requires medical evaluation to understand whether an underlying cause may be contributing to repeated pregnancy losses.

Recurrent pregnancy loss is a distinct reproductive health condition and is different from infertility. According to the latest American Society for Reproductive Medicine (ASRM) guidance, recurrent pregnancy loss is defined as two or more spontaneous pregnancy losses, excluding confirmed molar or ectopic pregnancies. The losses do not necessarily have to occur consecutively.

Many miscarriages, particularly those occurring early in pregnancy, are related to chromosomal abnormalities in the embryo. The likelihood of chromosomal abnormalities also increases with maternal age. However, recurrent pregnancy loss can have several possible causes, and sometimes no single cause is identified even after a detailed evaluation.

If you have experienced repeated miscarriages, consulting an experienced fertility specialist or obstetrician-gynaecologist can help determine whether further testing or treatment is appropriate.

What Is Recurrent Pregnancy Loss?

Recurrent pregnancy loss (RPL) refers to repeated spontaneous pregnancy losses.

Current ASRM guidance defines RPL as the spontaneous loss of two or more pregnancies, excluding confirmed molar and ectopic pregnancies. Pregnancy losses do not have to be consecutive for evaluation to be considered.

The term recurrent miscarriage is also commonly used. Older medical literature may use the term recurrent abortion, but “recurrent pregnancy loss” is generally preferred for patient-focused medical communication.

Recurrent pregnancy loss can be associated with genetic, anatomical, hormonal, metabolic, immune-related and other factors. In some couples, no clear cause is identified.


What Causes Recurrent Pregnancy Loss?

Causes Recurrent Pregnancy Loss

There is no single cause of recurrent miscarriage. A detailed evaluation may consider several factors involving the embryo, chromosomes, uterus, hormones, metabolism, and the health of both partners.

1. Chromosomal Abnormalities

Chromosomal abnormalities are an important cause of early pregnancy loss.

Approximately 50%–60% of first-trimester miscarriages are associated with embryonic aneuploidy, and the likelihood of aneuploidy is strongly influenced by maternal age.

Most chromosomal abnormalities occur sporadically during egg or embryo development. In some cases, however, chromosome abnormalities involving one of the parents may contribute to recurrent pregnancy loss.

When possible, chromosome testing of miscarriage tissue may provide useful information during recurrent pregnancy loss evaluation. The latest ASRM guidance recommends chromosome analysis of pregnancy-loss tissue, when feasible, as an important part of evaluation.

2. Uterine Abnormalities

Problems affecting the structure of the uterus may contribute to pregnancy loss in some women.

These may include:

  • Uterine septum
  • Certain congenital uterine anomalies
  • Fibroids
  • Endometrial polyps
  • Intrauterine adhesions

Your fertility specialist may recommend imaging or other investigations based on your history and symptoms.

3. Antiphospholipid Syndrome

Antiphospholipid syndrome (APS) is an autoimmune condition associated with abnormal blood clotting and specific pregnancy complications.

APS is an established and potentially treatable cause of recurrent pregnancy loss. Testing may be recommended when a patient’s history suggests an increased risk.

Treatment for confirmed obstetric APS may include medications such as low-dose aspirin and heparin under specialist supervision. These medicines should not be started without medical advice. Current evidence does not support routinely prescribing aspirin or anticoagulants to everyone with recurrent pregnancy loss.

4. Thyroid and Metabolic Conditions

Certain medical conditions may be associated with pregnancy loss.

Depending on the individual’s history, evaluation may include conditions such as:

  • Thyroid disease
  • Diabetes
  • Other metabolic disorders

The latest ASRM guidance supports targeted assessment for conditions such as thyroid disease and diabetes when clinically appropriate.

5. Age-Related Factors

Maternal age is an important factor in miscarriage risk because chromosomal abnormalities in eggs and embryos become more common with increasing age.

This does not mean that pregnancy after 35 is impossible or necessarily unsuccessful. However, age should be considered when evaluating recurrent pregnancy loss and planning future pregnancy.

6. Other Factors

Depending on the clinical history, doctors may also consider:

  • Genetic factors
  • Certain anatomical conditions
  • Lifestyle factors
  • Chronic medical conditions
  • Previous pregnancy complications

Not every proposed cause of recurrent miscarriage has strong evidence. Current guidelines recommend targeted evaluation rather than routinely performing every available test.


Recurrent Pregnancy Loss Symptoms

Recurrent Pregnancy Loss Symptoms

Recurrent pregnancy loss itself does not usually have a specific set of symptoms between pregnancies. The main concern is repeated pregnancy loss.

During an individual miscarriage, symptoms may include:

  • Vaginal bleeding or spotting
  • Lower abdominal or pelvic cramping
  • Back pain
  • Passing tissue or clots
  • Decreasing pregnancy symptoms

However, these symptoms do not always mean that a miscarriage is occurring. Bleeding and abdominal pain during pregnancy can have several causes.

Seek urgent medical care if you experience heavy bleeding, severe abdominal or pelvic pain, dizziness, fainting, fever or other concerning symptoms during pregnancy.


When Should You See a Doctor for Recurrent Miscarriage?

If you have experienced two or more pregnancy losses, it is reasonable to discuss recurrent pregnancy loss evaluation with a qualified obstetrician-gynaecologist or fertility specialist. Current ASRM guidance recognises RPL after two spontaneous pregnancy losses.

You should especially seek specialist advice if:

  • You have had two or more miscarriages.
  • You have experienced a second-trimester pregnancy loss.
  • You have irregular menstrual cycles.
  • You have a known uterine abnormality.
  • You have a history suggesting autoimmune or metabolic disease.
  • You or your partner has a known genetic condition.
  • You have been trying to conceive again after repeated pregnancy loss.

Tests for Recurrent Pregnancy Loss

There is no single test that can identify every cause of recurrent pregnancy loss.

Your doctor may recommend targeted investigations based on your pregnancy history, age, previous test results and other health factors.

Common Tests

Depending on the individual situation, evaluation may include:

Genetic Testing

Chromosome testing of pregnancy-loss tissue can help determine whether a chromosomal abnormality contributed to the miscarriage.

In selected cases, parental genetic testing may also be considered.

Uterine Evaluation

Tests used to assess the uterus may include:

The appropriate test depends on the suspected condition.

Antiphospholipid Antibody Testing

Testing for antiphospholipid syndrome may be recommended when clinically appropriate.

Thyroid and Metabolic Assessment

Your doctor may recommend blood tests to assess thyroid function, diabetes or other metabolic conditions depending on your medical history.

Evaluation of Other Health Factors

A detailed medical, reproductive and family history can help determine whether additional investigations are required.


Can Recurrent Pregnancy Loss Be Prevented?

There is no guaranteed way to prevent every miscarriage because many early pregnancy losses are caused by chromosomal abnormalities that occur during embryo development.

However, addressing treatable medical conditions and maintaining good preconception health may support a healthy pregnancy.

Steps That May Support a Healthy Pregnancy

Maintain a Healthy Lifestyle

Aim for a balanced diet, regular physical activity and a healthy weight appropriate for your individual circumstances.

Avoid Smoking and Tobacco

Smoking is associated with adverse reproductive and pregnancy outcomes. Avoid tobacco and exposure to tobacco smoke when planning pregnancy.

Avoid Alcohol During Pregnancy

Alcohol should be avoided during pregnancy.

Review Medications Before Pregnancy

Speak with your doctor before starting, stopping or changing any medication while trying to conceive or during pregnancy.

Manage Existing Health Conditions

Conditions such as diabetes and thyroid disease should be appropriately evaluated and managed before and during pregnancy.

Take Recommended Prenatal Supplements

Your doctor may recommend folic acid and other prenatal supplements based on your individual needs.

Attend Preconception Care

A preconception consultation can help identify medical or reproductive factors that may need attention before another pregnancy.


Recurrent Pregnancy Loss Treatment

Recurrent Pregnancy Loss Treatment

Treatment for Recurrent Miscarriage depends on the underlying cause.

There is no single treatment that works for every couple.

After evaluation, treatment may involve:

  • Management of thyroid or metabolic conditions
  • Treatment of confirmed antiphospholipid syndrome
  • Treatment of certain uterine abnormalities
  • Genetic counselling
  • Fertility treatment where appropriate
  • Psychological and emotional support

Current guidelines emphasise evidence-based, targeted treatment and caution against the routine use of tests or therapies that have not demonstrated clear benefit.


Treatment for Uterine Abnormalities

If a uterine abnormality is identified and is considered relevant to the pregnancy losses, treatment may sometimes be recommended.

Depending on the condition, treatment can include procedures such as hysteroscopic surgery.

For example, a uterine septum may be treated surgically in selected patients after appropriate evaluation and counselling.

The decision to operate should be individualised rather than based solely on an ultrasound finding.


Treatment for Antiphospholipid Syndrome

Women with confirmed obstetric antiphospholipid syndrome may benefit from specific treatment during pregnancy.

Depending on the clinical situation, a specialist may prescribe low-dose aspirin and heparin or another appropriate anticoagulant.

These medications are not appropriate for everyone with recurrent miscarriage or for people without a confirmed indication. They can have important side effects and should only be used under medical supervision.


Can IVF Help With Recurrent Pregnancy Loss?

IVF is not automatically required for Recurrent Miscarriage

Many couples with recurrent pregnancy loss can achieve a successful pregnancy without IVF, depending on the cause, age and other fertility factors.

However, IVF may be considered when there is another indication for assisted reproductive treatment or in selected couples where genetic factors are relevant.

IVF allows eggs to be fertilised in the laboratory and embryos to be transferred to the uterus.

IVF and Genetic Testing

In selected cases, preimplantation genetic testing (PGT) may be discussed when there is a known genetic or chromosomal indication.

However, PGT is not a universal treatment for recurrent pregnancy loss. The benefits, limitations, cost and possibility of obtaining a suitable embryo should be discussed with a fertility specialist.

Current ASRM guidance notes that evidence concerning PGT-A in recurrent pregnancy loss is still nuanced, and treatment should be individualised rather than offered routinely to every patient with RPL.


Chances of a Successful Pregnancy

Experiencing recurrent miscarriage does not mean that a future healthy pregnancy is impossible.

The outcome depends on several factors, including:

  • Maternal age
  • Number and timing of previous pregnancy losses
  • Chromosomal findings
  • Underlying medical conditions
  • Uterine factors
  • Whether a treatable cause is identified

Importantly, many cases remain unexplained even after evaluation. The latest ASRM guidance reports that 50%–80% of patients with unexplained recurrent pregnancy loss may go on to have a successful pregnancy, depending on individual circumstances.

Your individual prognosis should be discussed with your fertility specialist rather than estimated from a general percentage.


Emotional Support After Recurrent Miscarriage

Recurrent Miscarriage can be emotionally challenging for both partners.

Feelings of sadness, anxiety, grief, frustration or fear during a subsequent pregnancy are understandable.

Psychological support and counselling are an important part of recurrent pregnancy loss care. Current ASRM guidance specifically recommends emotional support for patients and couples experiencing RPL.

Seeking professional support does not mean that your concerns are being dismissed. Emotional wellbeing is an important part of reproductive healthcare.


Recurrent Pregnancy Loss Treatment in Srinagar

If you are looking for recurrent pregnancy loss treatment in Srinagar, an evaluation by a fertility specialist can help identify possible causes and determine whether further investigations or treatment are appropriate.

At Imprimis IVF & Fertility Centre, Srinagar, couples can seek fertility evaluation and discuss recurrent miscarriage, infertility and available fertility treatment options.

The centre provides fertility-related services including infertility evaluation, IUI and IVF treatment.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

If you have experienced repeated miscarriages, consult a qualified fertility specialist before starting medicines or fertility treatment on your own.


Frequently Asked Questions

What is recurrent pregnancy loss?

Recurrent pregnancy loss is generally defined as two or more spontaneous pregnancy losses. Current ASRM guidance does not require the losses to be consecutive.

Is recurrent abortion the same as recurrent miscarriage?

The terms may be used to describe repeated pregnancy loss, but recurrent pregnancy loss (RPL) is the preferred modern clinical terminology for patient education.

How many miscarriages are considered recurrent pregnancy loss?

Current ASRM guidance defines recurrent pregnancy loss as two or more spontaneous pregnancy losses.

What is the most common cause of recurrent miscarriage?

Chromosomal abnormalities are a major cause of early pregnancy loss. However, recurrent pregnancy loss can have several possible causes, and some cases remain unexplained.

Can PCOS cause recurrent miscarriage?

PCOS may be associated with certain reproductive and metabolic risks, but recurrent pregnancy loss should not automatically be attributed to PCOS. A proper medical evaluation is needed to identify possible contributing factors.

Can thyroid problems cause recurrent miscarriage?

Thyroid disorders can affect reproductive and pregnancy health. Appropriate thyroid assessment may be part of the evaluation of recurrent pregnancy loss when clinically indicated.

Can recurrent pregnancy loss be treated?

Yes, in some cases an underlying cause can be identified and treated. However, there is no single treatment for all cases of recurrent pregnancy loss.

Is IVF necessary after recurrent miscarriage?

No. IVF is not automatically required after recurrent miscarriage. It may be considered when there is another indication for IVF or in selected situations involving genetic or fertility factors.

Can IVF prevent miscarriage?

IVF cannot guarantee that miscarriage will be prevented. In selected cases, IVF with appropriate genetic testing may be discussed, but it is not a universal treatment.

Should I take aspirin or heparin after repeated miscarriages?

Do not start aspirin or heparin without medical advice. These medications may be appropriate for selected patients, particularly those with confirmed antiphospholipid syndrome, but they are not routinely recommended for everyone.

Can I have a healthy pregnancy after recurrent miscarriage?

Yes. Many people with recurrent pregnancy loss subsequently have a successful pregnancy. Your individual chances depend on factors such as age, medical history, previous pregnancy losses and whether an underlying cause is identified.


Take the Next Step After Recurrent Pregnancy Loss

Experiencing repeated pregnancy loss can be difficult, but it does not mean that a successful pregnancy is impossible.

The right approach is to identify possible causes, treat conditions that can be addressed and develop an individualised pregnancy or fertility plan.

If you have experienced two or more pregnancy losses, consider speaking with a qualified fertility specialist or obstetrician-gynaecologist for appropriate evaluation.

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 979775611

Medical Reviewer: Imprimis IVF & Fertility Centre Team

Last Updated: September 19, 2026

Bulky Uterus: Causes, Symptoms, Treatment & Effect on Fertility

If your ultrasound or transvaginal scan says “bulky uterus” or “enlarged uterus,” it is understandable to feel worried. However, a bulky uterus is not a diagnosis by itself. It is a description in which the uterus appears larger than expected on examination or imaging.

The important question is why the uterus is enlarged.

Conditions such as adenomyosis and uterine fibroids are common causes, although other factors may also contribute. Some women with an enlarged uterus have no symptoms and may not need treatment at all. Others may experience heavy periods, pelvic pain, pressure, or fertility problems depending on the underlying condition.

Therefore, if your ultrasound report mentions a bulky uterus, there is no need to panic. Instead, discuss the scan findings, symptoms, age, reproductive plans, and other fertility factors with a qualified gynaecologist or fertility specialist.

What Is a Bulky Uterus?

The uterus (womb) is a muscular reproductive organ located in the pelvis. Its size can vary considerably depending on factors such as age, pregnancy history, hormonal status and individual anatomy.

A bulky uterus generally means that the uterus appears enlarged on pelvic examination or imaging, such as an ultrasound scan. There is no single measurement that defines a bulky uterus for every woman because uterine size varies with age, parity, menopausal status and other factors.

More importantly, the word “bulky” does not tell you the cause.

For example, an enlarged uterus may be associated with:

  • Adenomyosis
  • Uterine fibroids
  • Pregnancy or the postpartum period
  • Less commonly, other uterine or pelvic conditions

Transvaginal ultrasound can help doctors assess the uterus, including the uterine muscle and endometrial cavity, and can identify conditions such as fibroids and adenomyosis.

Is a Bulky Uterus Always a Problem?

No.

A bulky uterus does not automatically mean cancer, infertility, or a serious disease.

Some women have an enlarged uterus with few or no symptoms. Treatment depends on the underlying cause, the severity of symptoms, whether fertility is a concern, and the woman’s reproductive plans.

For this reason, the ultrasound finding should be interpreted in the context of the complete clinical picture rather than treated as a diagnosis in itself.


Bulky Uterus Causes

Causes of Bulky Uterus

Several conditions can make the uterus appear enlarged. The most important causes include adenomyosis and uterine fibroids.

1. Adenomyosis

Adenomyosis occurs when tissue similar to the endometrium grows into the muscular wall of the uterus. This can cause the uterine muscle to become thickened and the uterus to appear enlarged or “bulky” on ultrasound.

Common symptoms can include:

  • Heavy menstrual bleeding
  • Painful periods
  • Pelvic pain
  • Abdominal bloating or heaviness
  • Pain during sex

However, some women with adenomyosis have no symptoms at all.

Adenomyosis becomes more commonly diagnosed with increasing age and is particularly seen in women over 30. Previous pregnancy may also be associated with a higher likelihood of the condition.

2. Uterine Fibroids

Uterine fibroids are non-cancerous growths that develop in or around the uterus. They can vary greatly in number, location and size.

Large or multiple fibroids can increase the overall size of the uterus.

Depending on their location and size, fibroids may cause:

  • Heavy or prolonged periods
  • Painful periods
  • Pelvic pressure or pain
  • Lower back pain
  • Frequent urination
  • Constipation or bloating
  • Pain during sex
  • Difficulty becoming pregnant in some women

However, many fibroids cause no symptoms and do not always require treatment.

3. Pregnancy and the Postpartum Period

The uterus naturally enlarges substantially during pregnancy. After childbirth, it gradually contracts toward its pre-pregnancy size.

Therefore, uterine size needs to be interpreted in the context of pregnancy status and recent childbirth. A uterus that appears enlarged during or shortly after pregnancy should not automatically be labeled abnormal.

4. Other Uterine Conditions

Less commonly, other uterine abnormalities or pelvic conditions may affect uterine size or appearance.

This is why an ultrasound report should be interpreted by a clinician who can assess the uterine shape, myometrium, endometrial cavity, and surrounding pelvic structures, rather than focusing solely on the term “bulky.”


Symptoms of Bulky Uterus


A bulky uterus itself may not cause symptoms. Symptoms usually depend on the underlying condition responsible for the uterine enlargement.

Possible symptoms include:

  • Heavy menstrual bleeding
  • Prolonged periods
  • Painful periods
  • Pelvic pain or pressure
  • Lower abdominal discomfort
  • Bloating or abdominal heaviness
  • Lower back pain
  • Pain during sexual intercourse
  • Frequent urination
  • Constipation or difficulty passing stools
  • Fatigue related to heavy menstrual blood loss

Adenomyosis, for example, commonly causes painful or heavy periods, pelvic pain, bloating or heaviness, and pain during sex.

Fibroids can also cause heavy or painful periods, pelvic or back pain, urinary symptoms, bowel symptoms and, in some women, difficulty getting pregnant.

When Should You See a Doctor?

You should consider a medical evaluation if you have:

  • Very heavy or prolonged periods
  • Severe or worsening pelvic pain
  • Bleeding between periods or after sex
  • Persistent abdominal or pelvic swelling
  • Pain during sex
  • Difficulty becoming pregnant
  • Repeated miscarriage
  • An ultrasound report showing a bulky uterus along with other abnormalities

Severe or persistent symptoms should not be ignored.


How Is a Bulky Uterus Diagnosed?

A bulky uterus is usually identified during a pelvic examination or imaging test.

Transvaginal Ultrasound

A transvaginal ultrasound (TVS) is commonly used to evaluate the uterus and ovaries. It can provide information about:

  • Uterine size
  • Uterine shape
  • Thickness and appearance of the uterine muscle
  • Endometrial lining
  • Fibroids
  • Adenomyosis
  • Ovaries and surrounding pelvic structures

ASRM notes that transvaginal ultrasound can visualize many uterine conditions, including leiomyomas (fibroids), endometrial polyps, and adenomyosis, which may be relevant when evaluating infertility.

MRI

In some situations, your doctor may recommend a pelvic MRI, particularly when ultrasound findings require further clarification.

MRI can provide additional information about the uterine muscle and may help evaluate suspected adenomyosis or other pelvic conditions.

Additional Fertility Tests

If you are trying to conceive, your doctor may recommend additional investigations depending on your history, such as:

  • Ovarian reserve testing
  • Hormonal tests
  • Semen analysis
  • Fallopian tube evaluation
  • Assessment of the uterine cavity
  • Other infertility investigations

A bulky uterus should therefore be assessed as part of the complete fertility evaluation, not in isolation.


Bulky Uterus and Infertility: Can You Get Pregnant?

Yes, many women with a bulky uterus can become pregnant.

The effect on fertility depends primarily on what is causing the uterus to enlarge.

For example, some fibroids may have little effect on fertility, while fibroids that distort the uterine cavity can be more clinically important.

Similarly, adenomyosis may be associated with fertility difficulties in some women. Current evidence suggests an association between adenomyosis and reduced implantation in certain fertility-treatment populations, although the best treatment approach before embryo transfer is still an area of ongoing research.

Therefore, the phrase “bulky uterus” does not mean “infertile.”

Your fertility specialist will consider:

  • Your age
  • Menstrual symptoms
  • Ovarian reserve
  • Ovulation
  • Sperm parameters
  • Fallopian tube status
  • Uterine cavity
  • Fibroids or adenomyosis
  • Previous pregnancy or IVF history

Can a Bulky Uterus Affect IVF Success?

A bulky uterus does not automatically prevent IVF.

However, if the enlargement is due to a condition such as adenomyosis or fibroids, the underlying condition may need to be evaluated before treatment.

For example, fibroids can sometimes affect fertility depending on their size and location. Adenomyosis has also been associated with reduced implantation and fertility-treatment outcomes in some studies.

The appropriate IVF plan therefore depends on the individual patient.

In some cases, treatment may be recommended before embryo transfer. In others, especially when the patient has no significant symptoms or the uterine cavity is not affected, immediate treatment may not be necessary.


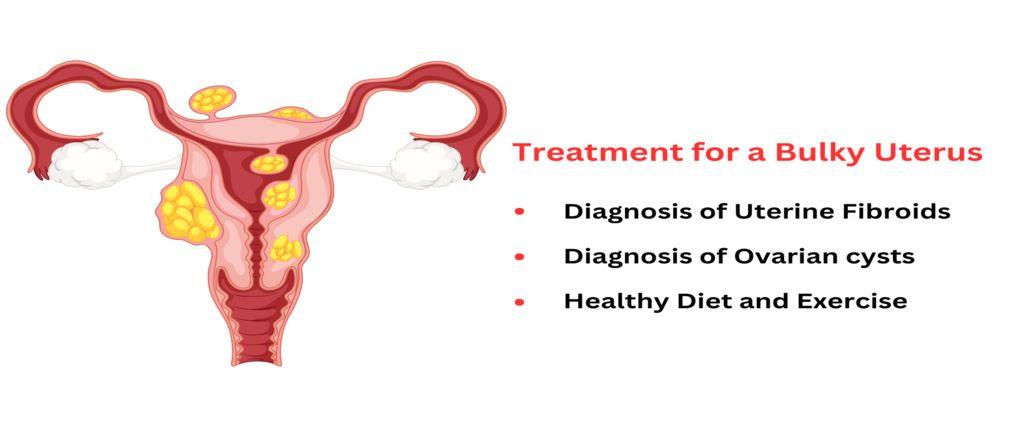
Treatment of Bulky Uterus


There is no single treatment for a bulky uterus.

Treatment depends on the cause, symptoms, age, fertility plans, and severity of the condition.

Treatment for Uterine Fibroids

If fibroids are small and asymptomatic, treatment may not be necessary.

When symptoms are significant, treatment options may include:

  • Pain-relieving medicines
  • Medicines to reduce heavy menstrual bleeding
  • Hormonal treatments in selected patients
  • Myomectomy to remove fibroids
  • Other procedures depending on the location and size of the fibroids

The treatment choice is highly individual. Women who want future pregnancy require a different treatment discussion from those who have completed their family.

Treatment for Adenomyosis

Treatment for adenomyosis depends on symptoms and reproductive goals.

Depending on the individual situation, doctors may consider:

  • Pain-relieving medicines
  • Medicines to reduce heavy menstrual bleeding
  • Hormonal treatment
  • An intrauterine system in appropriate patients
  • Other specialist treatments
  • Surgery in selected severe cases

A hysterectomy removes the uterus and therefore ends the possibility of carrying a future pregnancy, so it is generally considered only in appropriate circumstances, particularly when other treatments have not worked and pregnancy is no longer desired.


Bulky Uterus Treatment for Women Trying to Conceive

If you are trying to become pregnant, treatment needs to balance symptom control with fertility preservation.

For example, a fertility specialist may first determine:

  1. Why the uterus is enlarged
  2. Whether the uterine cavity is distorted
  3. Whether fibroids are present
  4. Whether adenomyosis is suspected
  5. Whether the fallopian tubes are open
  6. Whether ovulation is occurring normally
  7. Whether there are male-factor fertility issues
  8. Whether IVF or another fertility treatment is appropriate

Not every woman with a bulky uterus needs surgery.

In fact, unnecessary treatment can be avoided when the underlying condition is mild and does not interfere with fertility or cause significant symptoms.


Can Diet and Exercise Cure a Bulky Uterus?

A healthy lifestyle is beneficial for overall reproductive and general health, but diet and exercise cannot be considered a cure for an enlarged uterus caused by fibroids or adenomyosis.

A balanced diet, regular physical activity, adequate sleep, and maintaining a healthy weight can support general health. However, they should not replace medical evaluation or treatment when symptoms are present.

If you have heavy bleeding, pelvic pain, or fertility problems, speak with a gynecologist or fertility specialist rather than relying only on dietary changes.


Bulky Uterus: When Is It a Concern?

A bulky uterus deserves closer evaluation when it is associated with:

  • Heavy menstrual bleeding
  • Severe period pain
  • Persistent pelvic pain
  • Rapidly increasing abdominal or pelvic swelling
  • Fibroids
  • Suspected adenomyosis
  • Abnormal uterine bleeding
  • Difficulty conceiving
  • Recurrent pregnancy loss
  • Abnormal findings involving the uterine cavity

On the other hand, an incidental finding of a mildly enlarged uterus does not necessarily mean that you have a serious condition.

The cause matters more than the word “bulky.”


Frequently Asked Questions About Bulky Uterus

Is a bulky uterus dangerous?

Not necessarily. “Bulky uterus” is an imaging description rather than a diagnosis. The significance depends on the cause of the enlarged uterus and whether you have symptoms or other abnormal findings.

Can a bulky uterus cause infertility?

Sometimes, depending on the underlying cause. Fibroids that affect the uterine cavity and adenomyosis may be relevant to fertility in some women. However, having a bulky uterus does not automatically mean infertility.

Can I get pregnant with a bulky uterus?

Yes. Many women with an enlarged uterus can conceive. Your individual fertility outlook depends on the underlying cause, age, ovarian function, sperm quality, fallopian tubes, and uterine anatomy.

Does a bulky uterus mean adenomyosis?

No. Adenomyosis is one possible cause of an enlarged or bulky uterus, but fibroids and other conditions can also cause uterine enlargement. Ultrasound and, when necessary, MRI can help evaluate the cause.

Does a bulky uterus mean fibroids?

No. Fibroids can enlarge the uterus, but a bulky uterus does not automatically mean that fibroids are present. An ultrasound can help identify fibroids and describe their number, size, and location.

Can a bulky uterus affect IVF treatment?

It can, depending on the underlying condition. For example, some fibroids or adenomyosis may affect fertility treatment outcomes. Your fertility specialist can determine whether the uterus requires treatment or monitoring before embryo transfer.

Is surgery always needed for a bulky uterus?

No. Treatment is not automatically required simply because an ultrasound describes the uterus as bulky. Treatment depends on symptoms, the underlying cause, fertility plans, and other clinical findings.

Which test is best for a bulky uterus?

A transvaginal ultrasound is commonly used as an initial evaluation because it can assess the uterus, endometrium and surrounding pelvic structures. MRI may be recommended when additional evaluation is needed.


Bulky Uterus: The Bottom Line

Seeing the words **“bulky uterus” on an ultrasound report can be worrying, but the term itself does not tell you whether you have a serious condition or whether you will have difficulty becoming pregnant.

The next step is to identify the underlying cause.

Adenomyosis and uterine fibroids are important causes of an enlarged uterus, but not every bulky uterus requires treatment. A doctor may recommend monitoring, medicines, further imaging, or fertility-focused treatment depending on your symptoms and reproductive goals.

If you are trying to conceive and your ultrasound has reported a bulky or enlarged uterus, a fertility evaluation can help determine whether the finding is relevant to your fertility and whether any treatment is necessary.

Related Fertility Resources

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: September 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: Second Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu and Kashmir – 190014
Phone: 7678556881, 9650777084