IVF Diet Chart: Foods to Eat and Avoid During IVF Treatment

IVF Diet Chart: Starting IVF treatment can bring many questions, including one of the most common: What should I eat during IVF?

An IVF diet chart cannot guarantee a successful IVF cycle, and there is no single food that can make an embryo implant or increase IVF success on its own. However, eating a balanced, nutritious diet can support overall health, provide essential nutrients, and help you maintain a healthy lifestyle before and during fertility treatment.

Research on specific dietary patterns and IVF outcomes remains mixed. Some studies have reported associations between healthier dietary patterns and IVF outcomes, while others have not found a consistent benefit. Therefore, diet should be viewed as part of overall preconception and fertility care rather than a replacement for medical treatment.

What Is an IVF Diet Chart?

An IVF diet chart is a practical eating plan designed to help you maintain good nutrition during fertility treatment.

Instead of focusing on a “miracle IVF food,” the goal should be to include a variety of:

  • Vegetables and leafy greens
  • Fresh fruits
  • Whole grains
  • Beans, lentils and other legumes
  • Nuts and seeds
  • Healthy sources of protein
  • Healthy fats
  • Dairy or suitable alternatives
  • Adequate fluids

A healthy dietary pattern can support general health, while fertility treatment addresses the specific medical causes of infertility. The World Health Organisation also recommends healthy lifestyle measures, including a healthy diet and physical activity, for people planning or attempting pregnancy.

Does Diet Increase IVF Success Rate?

This is one of the most searched questions about IVF nutrition.

The short answer is: no specific IVF diet has been proven to guarantee IVF success.

Studies investigating Mediterranean-style diets, fertility diets and individual nutrients have produced inconsistent findings in people undergoing assisted reproductive treatment. Therefore, it is not appropriate to promise that a particular food, drink or diet will improve implantation, egg quality or live birth rates.

However, maintaining a nutritious diet can help support overall health during IVF and pregnancy planning.

Your IVF outcome depends on several factors, including:

  • Age
  • Ovarian reserve
  • Egg and embryo factors
  • Sperm quality
  • Uterine and tubal factors
  • Underlying medical conditions
  • Previous fertility treatment
  • Embryo genetics in selected cases
  • The specific IVF treatment plan

For more information, read our guide to [IVF Success Rate].

IVF Diet Chart: Foods to Eat During IVF Treatment

IVF Diet Chart


There is no mandatory list of “fertility foods.” Instead, aim for a varied and minimally processed diet.

1. Protein-Rich Foods

Protein is an important part of a balanced diet and is needed for tissue growth and repair.

Good choices include:

  • Eggs, when fully cooked
  • Milk and yoghurt
  • Paneer in moderate portions
  • Dal and lentils
  • Chickpeas and kidney beans
  • Soy and tofu
  • Nuts and seeds
  • Chicken and other lean meats
  • Well-cooked fish

There is no universal requirement that every woman undergoing IVF consume exactly 60 grams of protein per day. Protein requirements vary according to body size, activity level, pregnancy status, and medical needs.

2. Green Leafy Vegetables

Include vegetables such as:

  • Spinach
  • Methi
  • Broccoli
  • Cabbage
  • Beans
  • Peas
  • Capsicum
  • Carrots
  • Other seasonal vegetables

Leafy greens also provide folate, fibre and several vitamins and minerals.

3. Whole Grains and High-Fibre Foods

Choose whole or minimally processed carbohydrates more often, such as:

  • Oats
  • Whole-wheat roti
  • Brown rice
  • Millets
  • Quinoa
  • Barley
  • Whole-grain bread

Legumes such as chickpeas, rajma, peas and lentils can also provide fibre and plant-based protein.

4. Fruits

Fresh fruits can be part of a healthy IVF diet.

Options include:

  • Apples
  • Oranges
  • Guava
  • Berries
  • Pomegranate
  • Bananas
  • Papaya
  • Pears
  • Seasonal fruits

There is no strong evidence that one particular fruit, including pineapple, guarantees implantation or improves IVF success. Choose fruits for overall nutrition rather than as a fertility treatment.

5. Healthy Fats

Include moderate amounts of unsaturated fats from foods such as:

  • Nuts
  • Seeds
  • Avocado
  • Olive oil
  • Groundnut oil
  • Mustard oil
  • Fatty fish that is low in mercury

Healthy fats can form part of a balanced dietary pattern, but they should not be viewed as an IVF success booster.

6. Folic Acid and Folate-Rich Foods

Folic acid is particularly important before conception because it helps reduce the risk of neural tube defects.

Women planning pregnancy are generally advised to take 400 micrograms (mcg) of folic acid daily, unless their healthcare professional recommends a different dose.

Food sources of folate include:

  • Green leafy vegetables
  • Beans
  • Lentils
  • Peas
  • Citrus fruits
  • Fortified grains

Your fertility specialist may recommend a prenatal vitamin based on your individual nutritional requirements.

7. Iron-Rich Foods

Iron is essential for making haemoglobin and supporting normal blood function.

Food sources include:

  • Lentils
  • Beans
  • Spinach and other leafy greens
  • Sesame seeds
  • Pumpkin seeds
  • Meat and poultry
  • Iron-fortified cereals

The required amount of iron varies by life stage and pregnancy status. Do not take high-dose iron supplements unless advised by your doctor or after an assessment of your iron status.

8. Calcium and Vitamin D

Calcium and vitamin D are important for overall health and are particularly important during pregnancy.

Dietary sources can include:

  • Milk
  • Curd/yoghurt
  • Fortified dairy alternatives
  • Paneer
  • Eggs
  • Certain fish

Vitamin D deficiency is relatively common, but taking high-dose vitamin D without testing or medical advice is not recommended.

9. Low-Mercury Fish

You do not need to avoid all seafood during IVF.

Cooked, low-mercury fish can be part of a healthy diet. However, certain fish contain higher levels of mercury and should be avoided or limited, particularly during pregnancy. ACOG advises avoiding fish such as shark, swordfish, king mackerel, marlin and bigeye tuna during pregnancy.

Choose fish according to current pregnancy food-safety recommendations and local guidance.

Hydration During IVF

Adequate hydration is important for general health.

Drink water regularly throughout the day, and increase your intake as needed due to heat, exercise, or other circumstances.

However, there is no established evidence that drinking a specific number of glasses of water thickens the uterine lining or directly improves embryo implantation.

If you have a medical condition that requires fluid restriction, follow your doctor’s instructions.

IVF Diet Chart: What to Avoid or Limit

Foods to avoid during IVF Treatment

1. Alcohol

It is safest to avoid alcohol when undergoing IVF and when pregnancy is possible.

Alcohol can have adverse effects during pregnancy, and there is no established safe level of alcohol consumption during pregnancy.

2. Smoking and Tobacco

Avoid smoking and exposure to secondhand smoke.

Tobacco use is associated with poorer reproductive outcomes, and evidence indicates that smoking can negatively affect assisted reproductive treatment outcomes.

3. Excessive Caffeine

You do not necessarily need to eliminate caffeine entirely, but keeping intake below 200 mg per day is a commonly recommended safety limit during pregnancy. Remember that caffeine is also found in tea, chocolate, cola and energy drinks—not only coffee.

If you are unsure about the caffeine content of your usual drinks, ask your fertility specialist or dietitian.

4. Raw or Undercooked Eggs

Avoid raw or undercooked eggs due to the risk of foodborne illness.

Be particularly careful with foods prepared using raw eggs, such as some homemade mayonnaise, mousse and certain desserts.

5. Unpasteurized Milk and Dairy Products

Choose pasteurised milk and dairy products.

Unpasteurized products can carry bacteria that may cause serious foodborne infections during pregnancy.

6. Raw or Undercooked Meat and Seafood

Cook meat, poultry, eggs and seafood thoroughly.

Avoid raw fish and shellfish because they can increase the risk of foodborne illness.

7. High-Mercury Fish

Avoid fish known to contain high levels of mercury, particularly once pregnancy is established.

Your fertility team can provide guidance on safe seafood choices.

8. Highly Processed Foods and Excess Added Sugar

You do not need to eliminate all packaged foods from your diet.

However, try to limit frequent consumption of:

  • Sugary beverages
  • Sweets
  • Cakes and pastries
  • Highly processed snacks
  • Deep-fried foods
  • Processed meats
  • Foods high in added sugar and saturated fat

A balanced diet is more sustainable than extreme food restrictions.

Simple 1-Day IVF Diet Chart

The following is a general example, not a personalised medical diet.

Time Example
Morning Water + prescribed prenatal/folic acid supplement
Breakfast Vegetable oats/poha/upma + fully cooked egg or yoghurt
Mid-morning One seasonal fruit + a small handful of nuts
Lunch Roti/brown rice + dal + vegetables + curd
Evening Roasted chana/makhana or fruit + unsweetened tea
Dinner Roti/millet + cooked vegetables + dal/paneer/chicken/fish
Bedtime Milk or suitable alternative, if tolerated

Your calorie and nutrient requirements may be different. Patients with PCOS, diabetes, thyroid disorders, anaemia, obesity, underweight, food allergies or other medical conditions may need an individualised plan.

Is Five Meals a Day Necessary During IVF?

No.

There is no universal requirement to eat five meals every day during IVF.

Some people prefer smaller, frequent meals because they experience nausea, bloating or reduced appetite during treatment. Others are comfortable with three main meals and one or two snacks.

The important point is to maintain adequate nutrition and follow the dietary advice given by your healthcare team.

Can I Eat Pineapple During IVF?

Yes, pineapple can be part of a normal, balanced diet if you tolerate it.

However, there is no strong evidence that pineapple or its core can improve embryo implantation or increase IVF success.

The same principle applies to other foods sometimes promoted online as “implantation foods.” They can be nutritious, but they should not be presented as fertility treatments.

What Should I Eat After Embryo Transfer?

After embryo transfer, you generally do not need a special “implantation diet.”

Focus on:

  • Balanced meals
  • Adequate protein
  • Vegetables and fruits
  • Whole grains
  • Healthy fats
  • Adequate fluids
  • Folic acid/prenatal supplements as prescribed
  • Safe food preparation

Avoid alcohol, smoking and unsafe foods such as raw or undercooked animal products and high-mercury fish.

Continue your prescribed IVF medications exactly as instructed.

For more information, see [Embryo Transfer] and [IVF Treatment in Srinagar].

Can Diet Improve Egg Quality During IVF?

Diet provides the nutrients required for normal bodily functions, but no specific food or diet has been proven to “repair” or guarantee better egg quality.

Egg quality is influenced by several factors, including age and ovarian biology. A healthy lifestyle can support overall reproductive health, but it should not be promoted as a guaranteed way to improve egg quality.

If you have concerns about ovarian reserve or egg quality, discuss them with your fertility specialist.

Do I Need Supplements During IVF?

Not everyone undergoing IVF needs the same supplements.

Your fertility specialist may recommend supplements based on your medical history, blood tests, dietary intake and pregnancy-planning needs.

Commonly discussed nutrients include:

  • Folic acid
  • Iron
  • Vitamin D
  • Vitamin B12
  • Calcium

Do not start high-dose vitamins, minerals or herbal fertility supplements without medical advice.

IVF Diet and Lifestyle: Other Important Tips

Diet is only one part of preparing for IVF.

Take IVF Medicines on Time

Follow your fertility specialist’s instructions for hormonal injections, tablets and other medications.

Do not change the dose or stop medication without consulting your treatment team.

Stay Physically Active as Advised

Regular physical activity can support overall well-being. However, your activity level may need to be modified during ovarian stimulation or after specific procedures.

Always follow your fertility team’s instructions.

Avoid Smoking and Recreational Drugs

Smoking, tobacco and recreational drug use can negatively affect reproductive health. Tobacco cessation is particularly important when planning pregnancy.

Prioritise Sleep and Emotional Wellbeing

IVF can be physically and emotionally demanding.

Good sleep, emotional support, counselling when needed and realistic expectations can help you manage the treatment journey.

You do not need to maintain “constant positivity” for IVF to be successful. Treatment outcomes are not determined by whether a patient feels positive or anxious.

Is Strict Bed Rest Required After Embryo Transfer?

Routine strict bed rest is generally not required after embryo transfer.

Your fertility clinic may provide specific instructions about activity based on your procedure and medical circumstances. Follow those instructions rather than remaining in bed unnecessarily.

If you experience significant pain, heavy bleeding, breathing difficulty, severe abdominal swelling or other concerning symptoms after treatment, contact your fertility clinic promptly.

Can an IVF Diet Guarantee IVF Success?

No.

There is no diet, food, supplement or lifestyle change that can guarantee pregnancy or live birth through IVF.

IVF outcomes depend on multiple medical and biological factors. A healthy diet can support your overall health, but it should complement—not replace—evidence-based fertility treatment.

The WHO’s current infertility guidance supports evidence-based, patient-centred fertility care alongside healthy lifestyle measures.

Frequently Asked Questions About IVF Diet

What is the best diet during IVF treatment?

A balanced diet containing vegetables, fruits, whole grains, legumes, healthy protein sources and unsaturated fats is a practical approach. Your individual diet should be adjusted for your medical and nutritional needs.

Which foods should I avoid during IVF?

Avoid alcohol and smoking. Also avoid or limit foods with food-safety risks, including raw or undercooked eggs, meat and seafood, unpasteurized products and high-mercury fish.

Can I drink tea or coffee during IVF?

Moderate caffeine intake may be acceptable, but during pregnancy and when pregnancy is possible, keeping caffeine below 200 mg per day is commonly advised.

Can I eat fish during IVF?

Yes. Seafood does not need to be completely eliminated. Choose properly cooked, low-mercury fish and avoid high-mercury varieties according to pregnancy food-safety recommendations.

Is pineapple good for IVF implantation?

Pineapple can be part of a healthy diet, but there is no strong evidence that eating pineapple increases embryo implantation or IVF success.

Should I take folic acid during IVF?

Women planning pregnancy are generally advised to take 400 mcg of folic acid daily, unless their doctor recommends another dose.

Do I need five meals a day during IVF?

No. There is no universal requirement to eat five meals daily. Choose a meal pattern that meets your nutritional needs and feels comfortable for you.

Can an IVF diet improve my chances of pregnancy?

A nutritious diet supports general health, but no specific IVF diet has been proven to guarantee pregnancy or live birth. IVF success depends on many individual factors.

Final Takeaway: IVF Diet Chart

Following a healthy IVF diet chart can help you maintain good nutrition throughout fertility treatment, but there is no miracle food that guarantees implantation or IVF success.

Focus on a varied diet with vegetables, fruits, whole grains, legumes, lean proteins, nuts, seeds, and appropriate sources of healthy fats. Take folic acid and other supplements only as recommended by your healthcare professional.

Most importantly, avoid smoking and recreational drugs, avoid alcohol, keep caffeine moderate, and follow pregnancy food-safety precautions.

Your fertility specialist can help you create an IVF nutrition plan based on your medical history, treatment protocol and nutritional requirements.

If you are planning IVF treatment in Srinagar, you can consult the fertility team at Imprimis IVF & Fertility Centre, Srinagar for an individualised fertility assessment and treatment plan.

Medical Review & Clinic Information

Medical Reviewer: Imprimis IVF Team
Last Updated: September 19, 2026
Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014

Medical Disclaimer: This article is intended for educational purposes and should not replace personalised medical advice, diagnosis or treatment. Dietary requirements during IVF can vary considerably. Consult your fertility specialist or qualified dietitian before making significant dietary or supplement changes.

IVF vs IUI: Which Fertility Treatment Is Right for You?

When you’re trying to conceive and fertility treatment has become part of your journey, one question often comes up: IVF vs IUI—which is better?

The answer is not the same for every couple.

Intrauterine insemination (IUI) and in vitro fertilisation (IVF) are different fertility treatments used for different clinical situations. IUI is generally less invasive and less expensive, while IVF is a more advanced treatment in which eggs are retrieved and fertilised in a laboratory before an embryo is transferred to the uterus.

The choice between IUI and IVF depends on several factors, including:

  • Age of the female partner
  • Duration of infertility
  • Cause of infertility
  • Ovulation status
  • Fallopian tube condition
  • Sperm count and motility
  • Ovarian reserve
  • Previous fertility treatments
  • Other medical conditions
  • Patient preferences and treatment goals

There is therefore no universal answer to “IVF vs IUI, which is better?” A fertility specialist can recommend an appropriate treatment after evaluating both partners.

IVF vs IUI: Quick Comparison

Factor IUI IVF
Full form Intrauterine Insemination In Vitro Fertilisation
Where fertilisation occurs Inside the reproductive tract In a laboratory
Egg retrieval No Yes
Embryo created in laboratory No Yes
Procedure complexity Less invasive More involved
Typical treatment cost Lower Higher
Treatment duration Usually shorter Usually longer
Useful for Selected infertility cases A wider range of infertility conditions
Multiple pregnancy risk Can increase with ovarian stimulation Can be reduced with single embryo transfer
Treatment choice Depends on diagnosis Depends on diagnosis

The table is a general comparison. Your fertility specialist may recommend a different approach depending on your individual medical circumstances.


What Is IUI?

IUI (Intrauterine Insemination) is a fertility treatment in which specially prepared sperm are placed directly inside the uterus around the time of ovulation.

The aim is to place a higher concentration of motile sperm closer to the fallopian tubes, where fertilisation can occur naturally.

IUI may be performed during a natural ovulatory cycle or together with medicines that stimulate ovulation, depending on the patient’s fertility diagnosis.

How Does IUI Work?

A typical IUI cycle may involve:

  1. Monitoring the menstrual cycle and ovulation.
  2. Using fertility medicines when clinically appropriate.
  3. Monitoring follicular development through ultrasound.
  4. Preparing a semen sample in the laboratory.
  5. Placing the prepared sperm into the uterus using a thin catheter.
  6. Monitoring for pregnancy after the procedure.

The actual insemination procedure is usually brief and does not generally require anaesthesia.

IUI does not involve egg retrieval or laboratory fertilisation.


What Is IVF?

IVF (In Vitro Fertilisation) is an assisted reproductive technology in which eggs are retrieved from the ovaries and fertilised with sperm in a laboratory.

After fertilisation, embryos are cultured, and one or more embryos may be transferred into the uterus.

A typical IVF cycle may involve:

  1. Ovarian stimulation
  2. Ultrasound and hormone monitoring
  3. Trigger medication when appropriate
  4. Egg retrieval
  5. Fertilisation with sperm
  6. Embryo culture
  7. Embryo transfer or freezing
  8. Pregnancy testing

Depending on the treatment plan, additional procedures such as ICSI, embryo freezing or genetic testing may be considered.


IVF vs IUI: What Is the Main Difference?

The biggest difference between IUI and IVF is where fertilisation occurs.

With IUI, sperm are placed inside the uterus and fertilisation must occur naturally within the reproductive tract.

With IVF, eggs are retrieved and fertilised in a laboratory. The resulting embryo is then transferred into the uterus.

This makes IVF a more involved treatment, but it also allows fertility specialists to address a broader range of fertility problems.


When Is IUI Recommended?

IUI may be considered for selected patients with:

Unexplained Infertility

IUI with ovarian stimulation is commonly used as an initial treatment approach for many couples with unexplained infertility.

Current guidance supports treatment pathways that may progress from less invasive approaches such as stimulated IUI to IVF when appropriate. (asrm.org)

Mild Male-Factor Infertility

IUI may be considered when sperm parameters are suitable for insemination after evaluation and processing.

The decision should not be based on a single semen analysis result.

Ovulation Problems

Women with ovulation disorders may sometimes undergo ovulation induction followed by IUI, depending on the underlying condition.

Selected Cases of Cervical-Factor Infertility

IUI can bypass the cervix by placing prepared sperm directly into the uterus.

Donor Sperm Treatment

IUI may also be used with donor sperm when clinically appropriate.

The suitability of IUI depends on factors such as ovarian function, ovulation, fallopian tube status, sperm quality and age.


When Is IVF Recommended?

IVF may be considered when there is a medical reason for a more advanced fertility treatment or when simpler treatments have not been successful.

Potential situations include:

Blocked or Severely Damaged Fallopian Tubes

Because IVF bypasses the fallopian tubes during fertilisation, it may be recommended when the tubes are blocked or significantly damaged.

Severe Male-Factor Infertility

IVF, often combined with ICSI when indicated, may be considered for severe sperm abnormalities or certain situations involving very low or absent sperm in the ejaculate.

Repeatedly Unsuccessful IUI

If appropriately selected IUI cycles do not result in pregnancy, a fertility specialist may recommend moving to IVF.

The number of IUI cycles before IVF is not identical for every patient.

Reduced Ovarian Reserve or Age-Related Fertility Decline

Age and ovarian reserve are important when deciding how quickly to progress through fertility treatment.

For some patients, proceeding directly to IVF may be discussed rather than spending several cycles on less effective treatments.

Endometriosis

Depending on the severity of endometriosis, age and other fertility factors, IVF may be considered.

Genetic or Chromosomal Indications

IVF may be used when preimplantation genetic testing is being considered for an appropriate medical indication.

Other Infertility Factors

IVF may also be recommended when multiple fertility factors are present or when other treatments are unlikely to provide a reasonable opportunity for pregnancy.


IVF vs IUI for Male Infertility

Male-factor infertility can influence the choice between IUI and IVF.

A semen analysis evaluates several important parameters, including:

  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Semen volume

IUI may be suitable when there is an adequate number of motile sperm after semen processing.

When sperm abnormalities are more severe, IVF with ICSI (Intracytoplasmic Sperm Injection) may be considered.

ICSI involves injecting a single sperm directly into an egg. It is particularly relevant when there is a clear male-factor indication or a history of fertilisation failure. Current ASRM guidance cautions against using ICSI routinely for non-male-factor infertility without a specific indication. (asrm.org)


IVF vs IUI for Female Infertility

Female fertility can be affected by the ovaries, fallopian tubes, uterus, hormones and age.

IUI may be considered when:

  • At least one fallopian tube is functioning
  • Ovulation can be achieved
  • Sperm parameters are suitable
  • There is no major uterine or tubal factor requiring IVF

IVF may be considered when:

  • Both fallopian tubes are blocked
  • Ovarian reserve is reduced
  • There are significant fertility factors
  • Previous IUI treatment has failed
  • Age or other circumstances make a more direct treatment approach appropriate

A complete fertility evaluation helps determine which treatment is appropriate.


IVF vs IUI Success Rate

One of the most common searches is “IUI vs IVF success rate.”

However, quoting one fixed success percentage can be misleading.

Success depends on factors such as:

  • Age
  • Diagnosis
  • Ovarian reserve
  • Egg and embryo quality
  • Sperm quality
  • Number of treatment attempts
  • Treatment protocol
  • Previous fertility history
  • Clinic and laboratory factors

IVF generally offers a higher chance of pregnancy per treatment cycle than IUI for many infertility situations, but the comparison should be made using the same outcome measure and patient population.

A clinic should therefore not promise a specific pregnancy or live-birth rate without considering the individual patient’s circumstances.

For patients with unexplained infertility, evidence-based guidelines support stimulated IUI as a treatment option before IVF in many cases, while also recognising that factors such as age and treatment history can change the treatment pathway. (asrm.org)


IVF vs IUI Cost

Cost is another important factor when comparing IUI vs IVF.

Generally, IUI costs less per treatment cycle because it does not involve egg retrieval, laboratory fertilisation or embryo culture.

IVF usually costs more because it involves ovarian stimulation, monitoring, egg retrieval, laboratory fertilisation, embryo culture and embryo transfer.

However, the total cost can vary significantly depending on:

  • Medicines and injections
  • Diagnostic tests
  • Number of treatment cycles
  • ICSI
  • Embryo freezing
  • Frozen embryo transfer
  • Genetic testing
  • Donor eggs or sperm
  • Other clinically indicated procedures

Therefore, rather than relying on a single online price, ask the fertility clinic for a personalised treatment estimate and clarify what is included.

For information about local treatment pricing, see our IVF treatment cost in Srinagar and IUI treatment in Srinagar pages.


IUI vs IVF: Which Is More Painful?

Both IUI and IVF can involve some discomfort, but the experience varies from person to person.

IUI

IUI is generally a short procedure. Some women experience mild cramping or temporary discomfort when the catheter is inserted.

IVF

IVF involves more steps and usually includes injectable ovarian stimulation and an egg-retrieval procedure.

Egg retrieval is generally performed with appropriate pain relief or sedation, in accordance with the clinic’s protocol.

Therefore, it is not accurate to describe IVF simply as “painful” or IUI as completely “painless.” Individual experiences vary.


IUI vs IVF: Treatment Duration

IUI usually involves fewer treatment steps than IVF.

An IUI cycle may involve:

  • Cycle monitoring
  • Ovulation induction when required
  • Trigger medication when appropriate
  • Sperm preparation
  • Insemination
  • Pregnancy testing

IVF generally involves more appointments and procedures, including ovarian stimulation, monitoring, egg retrieval, fertilisation and embryo transfer.

The total IVF timeline varies depending on the treatment protocol and whether a fresh or frozen embryo transfer is planned.


Benefits and Limitations of IUI

Potential Benefits of IUI

  • Less invasive than IVF
  • Usually lower cost per cycle
  • Does not require egg retrieval
  • Short procedure
  • May be appropriate for selected infertility diagnoses

Limitations of IUI

  • Not suitable for every infertility condition
  • Requires suitable sperm parameters
  • Usually requires at least one functioning fallopian tube
  • Success can be lower per cycle than IVF
  • Several cycles may be needed
  • Ovarian stimulation can increase the risk of multiple pregnancy

Benefits and Limitations of IVF

Potential Benefits of IVF

  • Can bypass blocked fallopian tubes
  • Useful for many forms of infertility
  • Allows fertilisation to occur in the laboratory
  • Embryos can be frozen for future use
  • ICSI can be used when indicated
  • Genetic testing may be considered in selected cases
  • Can provide a treatment pathway when other fertility treatments have failed

Limitations of IVF

  • More invasive than IUI
  • Usually more expensive
  • Requires ovarian stimulation and egg retrieval
  • Takes more time and monitoring
  • Does not guarantee pregnancy
  • May involve additional procedures and costs

IVF vs IUI: Which One Is Better?

There is no universal answer to “Which is better, IUI or IVF?”

The more appropriate question is:

Which treatment is more suitable for my fertility diagnosis?

IUI may be a reasonable option when the fertility factors are relatively favourable and less invasive treatment is appropriate.

IVF may be more appropriate when there are significant tubal, sperm, ovarian, age-related or other fertility factors, or when previous treatments have not worked.

For some couples, starting with IUI may be appropriate. For others, moving directly to IVF may be discussed.

The WHO’s 2025 infertility guideline also emphasises evidence-based, patient-centred fertility care and progression from simpler to more complex treatment according to the individual’s clinical situation. (who.int)


IVF vs IUI: How Does a Doctor Decide?

Before recommending IUI or IVF, your fertility specialist may assess:

Female Partner

  • Age
  • Menstrual cycle
  • Ovulation
  • Ovarian reserve
  • Fallopian tubes
  • Uterus
  • Previous pregnancies
  • Previous fertility treatment

Male Partner

  • Semen analysis
  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Previous fertility history
  • Relevant medical conditions

Couple

  • Duration of infertility
  • Cause of infertility
  • Previous treatment outcomes
  • Genetic considerations
  • Financial and practical preferences
  • Time available for treatment

This assessment helps the fertility team develop an individualised treatment plan.


Can IUI Be Converted to IVF?

Yes. Fertility treatment is often progressive.

A couple may begin with IUI when it is clinically appropriate. If pregnancy does not occur after an appropriate number of cycles, or if new information changes the diagnosis, the fertility specialist may recommend IVF.

For unexplained infertility, ASRM guidance has historically supported a limited course of stimulated IUI followed by IVF when unsuccessful, while age and individual circumstances can influence whether IVF is considered earlier. (asrm.org)


IVF vs IUI Frequently Asked Questions

Is IUI better than IVF?

Neither treatment is universally better. IUI is less invasive and generally less expensive, while IVF can be appropriate for a broader range of infertility conditions. The right treatment depends on the couple’s diagnosis and circumstances.

Is IVF more successful than IUI?

IVF generally has a higher pregnancy potential per treatment cycle than IUI in many clinical situations, but success varies significantly with age, diagnosis and other factors. Comparing percentages without considering the patient population can be misleading.

Is IUI cheaper than IVF?

Generally, yes. IUI usually has a lower per-cycle cost because it does not involve egg retrieval or laboratory embryo development. However, total treatment costs vary.

How many IUI cycles should I try before IVF?

There is no single number for every patient. The decision depends on age, diagnosis, ovarian reserve, sperm parameters and previous treatment. In selected cases of unexplained infertility, several stimulated IUI cycles may be considered before IVF. (asrm.org)

Can IUI work with low sperm count?

It may be possible in selected cases, depending on the severity of the sperm abnormality and the number of motile sperm available after processing. Severe male-factor infertility may require IVF with ICSI.

Can IUI work with blocked fallopian tubes?

IUI generally requires at least one functioning fallopian tube because fertilisation still occurs inside the reproductive tract. If both tubes are blocked, IVF may be considered.

Is IVF painful?

IVF involves more procedures than IUI, including injections and egg retrieval. Pain and discomfort vary between individuals, and clinics use appropriate pain relief or sedation for egg retrieval.

Does IVF guarantee pregnancy?

No. IVF can provide an effective fertility treatment option, but it does not guarantee pregnancy or a live birth.

Which is better for older women: IUI or IVF?

Age is an important factor in fertility treatment planning. Depending on age, ovarian reserve, diagnosis and time available for treatment, a fertility specialist may discuss IVF sooner rather than spending multiple cycles on IUI.


IVF vs IUI in Srinagar

If you are searching for IVF vs IUI in Srinagar, the first step is to understand why pregnancy has not occurred.

At Imprimis IVF & Fertility Centre, Srinagar, a fertility specialist can evaluate both partners and discuss whether IUI, IVF or another fertility treatment is appropriate.

The evaluation may include assessment of ovulation, ovarian reserve, fallopian tubes, semen parameters and other relevant fertility factors.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

Treatment recommendations should be based on an individual medical evaluation rather than an online comparison.


Final Thoughts: IVF vs IUI

IVF and IUI are not competing treatments where one is always better than the other.

IUI is a less invasive fertility treatment that may be suitable for selected couples. IVF is a more involved treatment that can address a wider range of fertility problems.

The most appropriate option depends on your:

  • Age
  • Fertility diagnosis
  • Ovarian reserve
  • Ovulation
  • Fallopian tube status
  • Sperm parameters
  • Previous treatment
  • Overall reproductive health

If you are unsure whether IUI or IVF is right for you, consult a qualified fertility specialist for an individual assessment.


Medical Reviewer & Editorial Information

Medical Reviewer: Imprimis IVF

Last Updated: September 19, 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar

Medical Disclaimer: This article is intended for general educational purposes and does not replace professional medical advice, diagnosis or treatment. Fertility treatment should be selected after an appropriate evaluation by a qualified fertility specialist. Individual treatment outcomes vary.

Medical References: World Health Organization (WHO) 2025 Guideline for the Prevention, Diagnosis and Treatment of Infertility; American Society for Reproductive Medicine (ASRM) guidance; European Society of Human Reproduction and Embryology (ESHRE) guidance.

Recurrent Pregnancy Loss: Causes, Diagnosis & Treatment

Experiencing a miscarriage can be emotionally and physically difficult. While miscarriage is relatively common, recurrent pregnancy loss (RPL) requires medical evaluation to understand whether an underlying cause may be contributing to repeated pregnancy losses.

Recurrent pregnancy loss is a distinct reproductive health condition and is different from infertility. According to the latest American Society for Reproductive Medicine (ASRM) guidance, recurrent pregnancy loss is defined as two or more spontaneous pregnancy losses, excluding confirmed molar or ectopic pregnancies. The losses do not necessarily have to occur consecutively.

Many miscarriages, particularly those occurring early in pregnancy, are related to chromosomal abnormalities in the embryo. The likelihood of chromosomal abnormalities also increases with maternal age. However, recurrent pregnancy loss can have several possible causes, and sometimes no single cause is identified even after a detailed evaluation.

If you have experienced repeated miscarriages, consulting an experienced fertility specialist or obstetrician-gynaecologist can help determine whether further testing or treatment is appropriate.

What Is Recurrent Pregnancy Loss?

Recurrent pregnancy loss (RPL) refers to repeated spontaneous pregnancy losses.

Current ASRM guidance defines RPL as the spontaneous loss of two or more pregnancies, excluding confirmed molar and ectopic pregnancies. Pregnancy losses do not have to be consecutive for evaluation to be considered.

The term recurrent miscarriage is also commonly used. Older medical literature may use the term recurrent abortion, but “recurrent pregnancy loss” is generally preferred for patient-focused medical communication.

Recurrent pregnancy loss can be associated with genetic, anatomical, hormonal, metabolic, immune-related and other factors. In some couples, no clear cause is identified.


What Causes Recurrent Pregnancy Loss?

Causes Recurrent Pregnancy Loss

There is no single cause of recurrent miscarriage. A detailed evaluation may consider several factors involving the embryo, chromosomes, uterus, hormones, metabolism, and the health of both partners.

1. Chromosomal Abnormalities

Chromosomal abnormalities are an important cause of early pregnancy loss.

Approximately 50%–60% of first-trimester miscarriages are associated with embryonic aneuploidy, and the likelihood of aneuploidy is strongly influenced by maternal age.

Most chromosomal abnormalities occur sporadically during egg or embryo development. In some cases, however, chromosome abnormalities involving one of the parents may contribute to recurrent pregnancy loss.

When possible, chromosome testing of miscarriage tissue may provide useful information during recurrent pregnancy loss evaluation. The latest ASRM guidance recommends chromosome analysis of pregnancy-loss tissue, when feasible, as an important part of evaluation.

2. Uterine Abnormalities

Problems affecting the structure of the uterus may contribute to pregnancy loss in some women.

These may include:

  • Uterine septum
  • Certain congenital uterine anomalies
  • Fibroids
  • Endometrial polyps
  • Intrauterine adhesions

Your fertility specialist may recommend imaging or other investigations based on your history and symptoms.

3. Antiphospholipid Syndrome

Antiphospholipid syndrome (APS) is an autoimmune condition associated with abnormal blood clotting and specific pregnancy complications.

APS is an established and potentially treatable cause of recurrent pregnancy loss. Testing may be recommended when a patient’s history suggests an increased risk.

Treatment for confirmed obstetric APS may include medications such as low-dose aspirin and heparin under specialist supervision. These medicines should not be started without medical advice. Current evidence does not support routinely prescribing aspirin or anticoagulants to everyone with recurrent pregnancy loss.

4. Thyroid and Metabolic Conditions

Certain medical conditions may be associated with pregnancy loss.

Depending on the individual’s history, evaluation may include conditions such as:

  • Thyroid disease
  • Diabetes
  • Other metabolic disorders

The latest ASRM guidance supports targeted assessment for conditions such as thyroid disease and diabetes when clinically appropriate.

5. Age-Related Factors

Maternal age is an important factor in miscarriage risk because chromosomal abnormalities in eggs and embryos become more common with increasing age.

This does not mean that pregnancy after 35 is impossible or necessarily unsuccessful. However, age should be considered when evaluating recurrent pregnancy loss and planning future pregnancy.

6. Other Factors

Depending on the clinical history, doctors may also consider:

  • Genetic factors
  • Certain anatomical conditions
  • Lifestyle factors
  • Chronic medical conditions
  • Previous pregnancy complications

Not every proposed cause of recurrent miscarriage has strong evidence. Current guidelines recommend targeted evaluation rather than routinely performing every available test.


Recurrent Pregnancy Loss Symptoms

Recurrent Pregnancy Loss Symptoms

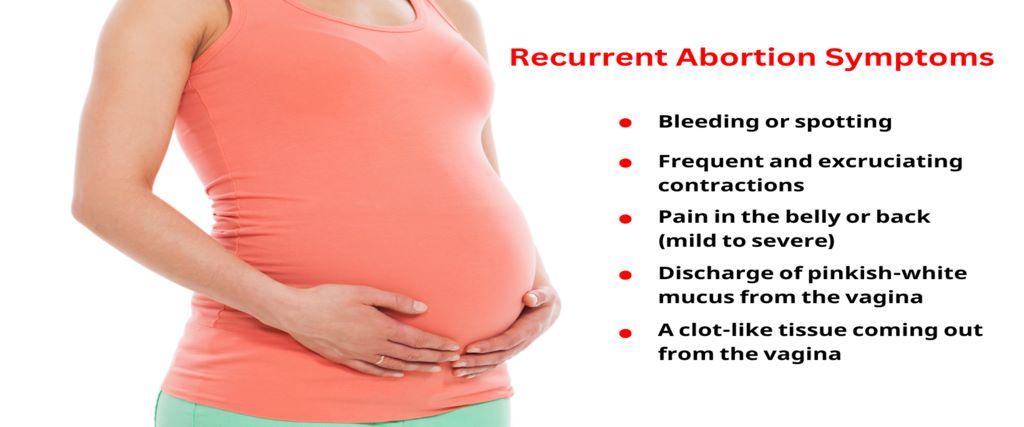
Recurrent pregnancy loss itself does not usually have a specific set of symptoms between pregnancies. The main concern is repeated pregnancy loss.

During an individual miscarriage, symptoms may include:

  • Vaginal bleeding or spotting
  • Lower abdominal or pelvic cramping
  • Back pain
  • Passing tissue or clots
  • Decreasing pregnancy symptoms

However, these symptoms do not always mean that a miscarriage is occurring. Bleeding and abdominal pain during pregnancy can have several causes.

Seek urgent medical care if you experience heavy bleeding, severe abdominal or pelvic pain, dizziness, fainting, fever or other concerning symptoms during pregnancy.


When Should You See a Doctor for Recurrent Miscarriage?

If you have experienced two or more pregnancy losses, it is reasonable to discuss recurrent pregnancy loss evaluation with a qualified obstetrician-gynaecologist or fertility specialist. Current ASRM guidance recognises RPL after two spontaneous pregnancy losses.

You should especially seek specialist advice if:

  • You have had two or more miscarriages.
  • You have experienced a second-trimester pregnancy loss.
  • You have irregular menstrual cycles.
  • You have a known uterine abnormality.
  • You have a history suggesting autoimmune or metabolic disease.
  • You or your partner has a known genetic condition.
  • You have been trying to conceive again after repeated pregnancy loss.

Tests for Recurrent Pregnancy Loss

There is no single test that can identify every cause of recurrent pregnancy loss.

Your doctor may recommend targeted investigations based on your pregnancy history, age, previous test results and other health factors.

Common Tests

Depending on the individual situation, evaluation may include:

Genetic Testing

Chromosome testing of pregnancy-loss tissue can help determine whether a chromosomal abnormality contributed to the miscarriage.

In selected cases, parental genetic testing may also be considered.

Uterine Evaluation

Tests used to assess the uterus may include:

The appropriate test depends on the suspected condition.

Antiphospholipid Antibody Testing

Testing for antiphospholipid syndrome may be recommended when clinically appropriate.

Thyroid and Metabolic Assessment

Your doctor may recommend blood tests to assess thyroid function, diabetes or other metabolic conditions depending on your medical history.

Evaluation of Other Health Factors

A detailed medical, reproductive and family history can help determine whether additional investigations are required.


Can Recurrent Pregnancy Loss Be Prevented?

There is no guaranteed way to prevent every miscarriage because many early pregnancy losses are caused by chromosomal abnormalities that occur during embryo development.

However, addressing treatable medical conditions and maintaining good preconception health may support a healthy pregnancy.

Steps That May Support a Healthy Pregnancy

Maintain a Healthy Lifestyle

Aim for a balanced diet, regular physical activity and a healthy weight appropriate for your individual circumstances.

Avoid Smoking and Tobacco

Smoking is associated with adverse reproductive and pregnancy outcomes. Avoid tobacco and exposure to tobacco smoke when planning pregnancy.

Avoid Alcohol During Pregnancy

Alcohol should be avoided during pregnancy.

Review Medications Before Pregnancy

Speak with your doctor before starting, stopping or changing any medication while trying to conceive or during pregnancy.

Manage Existing Health Conditions

Conditions such as diabetes and thyroid disease should be appropriately evaluated and managed before and during pregnancy.

Take Recommended Prenatal Supplements

Your doctor may recommend folic acid and other prenatal supplements based on your individual needs.

Attend Preconception Care

A preconception consultation can help identify medical or reproductive factors that may need attention before another pregnancy.


Recurrent Pregnancy Loss Treatment

Recurrent Pregnancy Loss Treatment

Treatment for Recurrent Miscarriage depends on the underlying cause.

There is no single treatment that works for every couple.

After evaluation, treatment may involve:

  • Management of thyroid or metabolic conditions
  • Treatment of confirmed antiphospholipid syndrome
  • Treatment of certain uterine abnormalities
  • Genetic counselling
  • Fertility treatment where appropriate
  • Psychological and emotional support

Current guidelines emphasise evidence-based, targeted treatment and caution against the routine use of tests or therapies that have not demonstrated clear benefit.


Treatment for Uterine Abnormalities

If a uterine abnormality is identified and is considered relevant to the pregnancy losses, treatment may sometimes be recommended.

Depending on the condition, treatment can include procedures such as hysteroscopic surgery.

For example, a uterine septum may be treated surgically in selected patients after appropriate evaluation and counselling.

The decision to operate should be individualised rather than based solely on an ultrasound finding.


Treatment for Antiphospholipid Syndrome

Women with confirmed obstetric antiphospholipid syndrome may benefit from specific treatment during pregnancy.

Depending on the clinical situation, a specialist may prescribe low-dose aspirin and heparin or another appropriate anticoagulant.

These medications are not appropriate for everyone with recurrent miscarriage or for people without a confirmed indication. They can have important side effects and should only be used under medical supervision.


Can IVF Help With Recurrent Pregnancy Loss?

IVF is not automatically required for Recurrent Miscarriage

Many couples with recurrent pregnancy loss can achieve a successful pregnancy without IVF, depending on the cause, age and other fertility factors.

However, IVF may be considered when there is another indication for assisted reproductive treatment or in selected couples where genetic factors are relevant.

IVF allows eggs to be fertilised in the laboratory and embryos to be transferred to the uterus.

IVF and Genetic Testing

In selected cases, preimplantation genetic testing (PGT) may be discussed when there is a known genetic or chromosomal indication.

However, PGT is not a universal treatment for recurrent pregnancy loss. The benefits, limitations, cost and possibility of obtaining a suitable embryo should be discussed with a fertility specialist.

Current ASRM guidance notes that evidence concerning PGT-A in recurrent pregnancy loss is still nuanced, and treatment should be individualised rather than offered routinely to every patient with RPL.


Chances of a Successful Pregnancy

Experiencing recurrent miscarriage does not mean that a future healthy pregnancy is impossible.

The outcome depends on several factors, including:

  • Maternal age
  • Number and timing of previous pregnancy losses
  • Chromosomal findings
  • Underlying medical conditions
  • Uterine factors
  • Whether a treatable cause is identified

Importantly, many cases remain unexplained even after evaluation. The latest ASRM guidance reports that 50%–80% of patients with unexplained recurrent pregnancy loss may go on to have a successful pregnancy, depending on individual circumstances.

Your individual prognosis should be discussed with your fertility specialist rather than estimated from a general percentage.


Emotional Support After Recurrent Miscarriage

Recurrent Miscarriage can be emotionally challenging for both partners.

Feelings of sadness, anxiety, grief, frustration or fear during a subsequent pregnancy are understandable.

Psychological support and counselling are an important part of recurrent pregnancy loss care. Current ASRM guidance specifically recommends emotional support for patients and couples experiencing RPL.

Seeking professional support does not mean that your concerns are being dismissed. Emotional wellbeing is an important part of reproductive healthcare.


Recurrent Pregnancy Loss Treatment in Srinagar

If you are looking for recurrent pregnancy loss treatment in Srinagar, an evaluation by a fertility specialist can help identify possible causes and determine whether further investigations or treatment are appropriate.

At Imprimis IVF & Fertility Centre, Srinagar, couples can seek fertility evaluation and discuss recurrent miscarriage, infertility and available fertility treatment options.

The centre provides fertility-related services including infertility evaluation, IUI and IVF treatment.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

If you have experienced repeated miscarriages, consult a qualified fertility specialist before starting medicines or fertility treatment on your own.


Frequently Asked Questions

What is recurrent pregnancy loss?

Recurrent pregnancy loss is generally defined as two or more spontaneous pregnancy losses. Current ASRM guidance does not require the losses to be consecutive.

Is recurrent abortion the same as recurrent miscarriage?

The terms may be used to describe repeated pregnancy loss, but recurrent pregnancy loss (RPL) is the preferred modern clinical terminology for patient education.

How many miscarriages are considered recurrent pregnancy loss?

Current ASRM guidance defines recurrent pregnancy loss as two or more spontaneous pregnancy losses.

What is the most common cause of recurrent miscarriage?

Chromosomal abnormalities are a major cause of early pregnancy loss. However, recurrent pregnancy loss can have several possible causes, and some cases remain unexplained.

Can PCOS cause recurrent miscarriage?

PCOS may be associated with certain reproductive and metabolic risks, but recurrent pregnancy loss should not automatically be attributed to PCOS. A proper medical evaluation is needed to identify possible contributing factors.

Can thyroid problems cause recurrent miscarriage?

Thyroid disorders can affect reproductive and pregnancy health. Appropriate thyroid assessment may be part of the evaluation of recurrent pregnancy loss when clinically indicated.

Can recurrent pregnancy loss be treated?

Yes, in some cases an underlying cause can be identified and treated. However, there is no single treatment for all cases of recurrent pregnancy loss.

Is IVF necessary after recurrent miscarriage?

No. IVF is not automatically required after recurrent miscarriage. It may be considered when there is another indication for IVF or in selected situations involving genetic or fertility factors.

Can IVF prevent miscarriage?

IVF cannot guarantee that miscarriage will be prevented. In selected cases, IVF with appropriate genetic testing may be discussed, but it is not a universal treatment.

Should I take aspirin or heparin after repeated miscarriages?

Do not start aspirin or heparin without medical advice. These medications may be appropriate for selected patients, particularly those with confirmed antiphospholipid syndrome, but they are not routinely recommended for everyone.

Can I have a healthy pregnancy after recurrent miscarriage?

Yes. Many people with recurrent pregnancy loss subsequently have a successful pregnancy. Your individual chances depend on factors such as age, medical history, previous pregnancy losses and whether an underlying cause is identified.


Take the Next Step After Recurrent Pregnancy Loss

Experiencing repeated pregnancy loss can be difficult, but it does not mean that a successful pregnancy is impossible.

The right approach is to identify possible causes, treat conditions that can be addressed and develop an individualised pregnancy or fertility plan.

If you have experienced two or more pregnancy losses, consider speaking with a qualified fertility specialist or obstetrician-gynaecologist for appropriate evaluation.

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 979775611

Medical Reviewer: Imprimis IVF & Fertility Centre Team

Last Updated: September 19, 2026