Tag Archive for: Ivf Success Rate by Age

10 Factors That Determine Your IVF Success Rate

In-vitro fertilization (IVF) is a frequently utilized strategy that aims to assist couples in conceiving when natural approaches have not proven effective. Achieving success through IVF is critically important. Determining the IVF success rate and understanding how it is calculated can help provide perspective and realistic expectations to prospective patients.

The success rate considers the percentage of IVF treatment cycles that lead to a confirmed pregnancy, which results in a live birth. It is impacted by multiple factors, including the age of the female partner, the cause of infertility, the number and quality of embryos transferred, and whether embryos have been previously frozen through the IVF process.

The IVF success rate is determined by dividing successful pregnancies by the number of IVF cycles performed. It’s often shown as a percentage. However, other factors affect IVF success, and patients need too and to know about them before starting IVF. Here we look at the top 10 factors that determine your IVF success.

Common Factors that Call for Successful IVF 

Among other important lists of factors for successful IVF, we have pointed out the top 10 that are probably the most important ones. Here are some of the factors that influence IVF success rate:
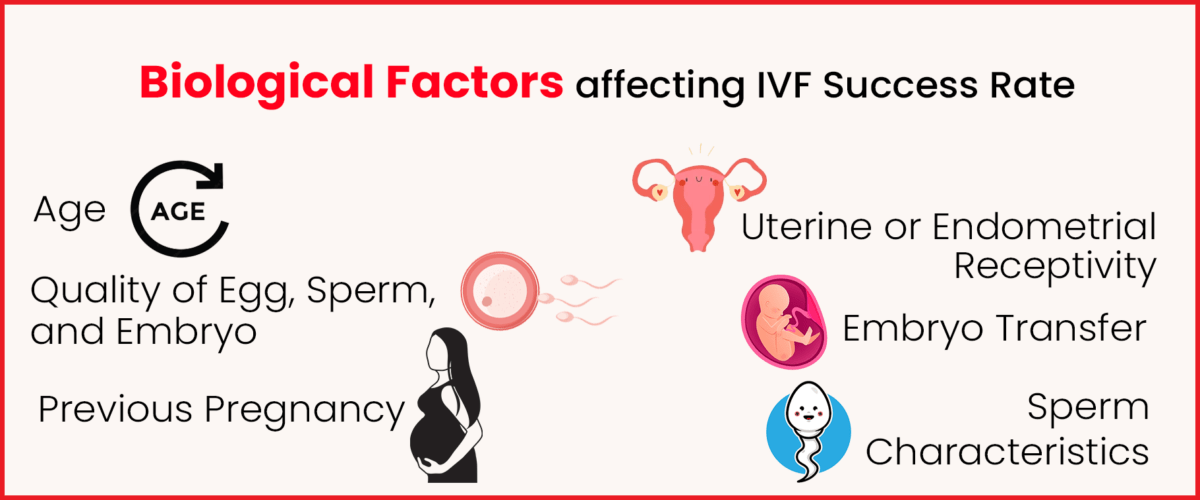
biological factors affecting IVF success rate

1. Age of the Patient

A person’s age is an important factor in determining the appropriate in vitro fertilization, or IVF, process, especially concerning the utilization of donor eggs. For many individuals, their eggs are employed, however, if one is over the age of forty, incorporating donor eggs has the potential to elevate the likelihood of success. While still relying on one’s biological material is usually preferable, the decline in egg quality that naturally accompanies advancing maternal age means those in their forties may want to take donor eggs into account as a viable option worth exploring.

Between the ages of 24 and 34, women have among the best chances of achieving success with in vitro fertilization, or IVF, as this period is typically viewed as the peak years of fertility. However, once a woman reaches 40 years old, the likelihood of a successful pregnancy through IVF treatment decreases. The 24 to 34 age group is considered the time of highest natural fertility when the quality and quantity of a woman’s eggs are at their prime.

As a woman ages past 35, both egg quantity and quality decline steadily each year. This is due to the natural ageing process of the ovaries over time. While IVF provides an opportunity for pregnancy beyond a woman’s natural fertile window, the odds of bringing home a baby continue to diminish the older a woman is when she begins treatment.

2. Previous Pregnancy 

Having experienced a successful pregnancy previously provides hope that in vitro fertilization (IVF) may be successful again, as the woman’s body has demonstrated its ability to support a healthy pregnancy and deliver a baby full-term. However, if prior IVF attempts or miscarriages are numerous, the likelihood of achieving a successful pregnancy may decline.

After all, each failed cycle or loss reduces the chances with each subsequent try. Still, medical advances continue and each new cycle brings a fresh opportunity, so it is important patients work closely with their doctors to optimize chances through customized treatment plans.

3. Fertility Issues

The nature of the fertility challenge holds significance. Certain difficulties can be more arduous to address than others, impacting both individuals and their partners. For example, those with blocked fallopian passages may encounter lower achievement quotas contrasted with people encountering issues with egg discharge. This component extraordinarily affects the achievement rate of the initial IVF treatment attempt. The sorts of fertility issues experienced can decide the seriousness of treatment and the prospects of achievement on the principal endeavour.

Blocked tubes regularly make it harder for eggs to meet sperm, bringing down the probability of standard conception. On the other hand, issues with ovulation regularly just require a prescription or different methods to trigger egg discharge, accomplishing pregnancy effectively. While each case merits individual consideration, understanding how the sort of issue influences the test of treatment can assist couples with choosing the most suitable course and setting sensible desires.

4. Quality of the Eggs and Embryos

Several aspects can impact the quality of eggs and embryos during in vitro fertilization, or IVF, treatment including a woman’s age, ovarian reserve, the stimulation protocol used, and sperm quality. Eggs and embryos of higher quality present a greater potential for success with IVF.

One of the most crucial factors is a woman’s ovarian reserve, which refers to the number of eggs in her ovaries. This has a direct impact on egg quality. Younger women are likely to produce maternal cells of better quality than those who are not in good ovarian reserve. Fertility medications that help eggs grow and ripen can alter quality. The stimulation procedure is the culprit. Several procedures might result in that.

5. Quality of the Sperm

The vast majority of chromosomal issues found in embryos, approximately 90%, are attributable to egg quality. However, male fertility problems also influence embryonic development. Scientific progress has provided valuable tools to mitigate these influences, raising the likelihood of achieving a healthy pregnancy.

While female reproductive health accounts for most chromosomal abnormalities observed in embryos, male factor infertility poses challenges as well. New technologies are helping to reduce the impact of these influences and boost the chances for successful conception. Further advancements in assisted reproduction hold promise for additionally lessening the effects of egg and sperm deficiencies, potentially aiding many hoping to start a family.

6. COH (Controlled Ovarian Stimulation) Protocol

After considering the woman’s age and hormonal levels, along with other health conditions, the doctor will decide on a suitable tolerance treatment plan. Usually, this plan involves medications, ranging from 10 to 14 days, during which growth is stimulated with the aid of hormonal monitoring, frequent blood tests, and ultrasound.

If the yield is disappointing with most eggs not reaching maturation, the current cycle which is in the production process may, therefore, be discontinued. In this example, the medical professionals would then assess what modifications could improve the treatment of the next round by correcting the medicine dose for example.

7. Lifestyle of the Patient:

Lifestyle factors affecting IVF success rate

Leading a healthy lifestyle sets the stage for a thriving embryo environment. Before starting IVF, it’s crucial to quit smoking and drinking alcohol for at least three months. Both habits reduce success chances, with smokers having 50% lower implantation rates.

Maintaining a healthy weight also boosts IVF success. Obesity affects hormone processing, fertility medications, menstrual cycles, and carrying a baby to term. The upside is, that you have control over your lifestyle, and these factors can be actively improved.

8. Embryo Transfer

The embryo transfer procedure plays an extremely important role in IVF treatment, according to many specialists in the field. Not only does it require a healthy embryo and successful implantation into the uterus, but the transfer itself must be executed perfectly. The timing and biological conditions involved in this process are critical, as any issues can negatively impact the chances of a successful outcome.

A flawless transfer represents one piece of the larger puzzle, and if done incorrectly, it could undermine the efforts of developing quality embryos and preparing the uterine lining. While physicians work to optimize the many factors within their control, couples also hope mother nature cooperates to allow the embryo’s implantation. Success at this phase means the chance for pregnancy continues, whereas problems may cut the process short. Perfection matters.

9. Uterine Receptivity 

A woman’s uterine lining is important in achieving success with in vitro fertilization. For an embryo to successfully implant, the uterine lining must be adequately thickened to support the development of a pregnancy.

Several factors can influence uterine receptivity, making it crucial to optimize the environment within the womb. Hormonal supplements are often prescribed to help strengthen and build up the endometrial lining. Tests such as a hysteroscopy procedure may also be used to examine the uterus and address any issues that could impact implantation.

10. Mental Health

Finally, the last but not the least key to maintaining a positive outlook when experiencing in vitro fertilization is to rate your mental health as anxiety, depression, and stress have been reported by many to seriously affect IVF success rates.

The emotional health of women taking IVF is very critical because cortisol and other stress hormones in large volumes worsen the uterus’s receptivity to implantation and embryo development in the early stages. There are various ways for patients have contribute to the reduction of stress or improvement of their mood condition, such as counselling or therapy. One of the major challenges of mental terms is finding the right words to speak about it.

 Conclusion

The IVF Success Rate is determined by various elements, ranging from patients to medical practitioners, and must be addressed collectively. Infertility treatment requires a lot of effort, from our age and the eggs and embryo quality to the way we live and the intricacy of the embryo transfer process; each of these features directly affects our chances for success.

Lastly, dealing with fertility problems, making the uterus more ready for pregnancy, and paying attention to emotional health are some of the measures that play a pivotal role in making the IVF treatment journey much more successful. The successful implementation of these troubleshooting factors will help patients approach IVF treatment with a more realistic approach and increase confidence, as they will know that they are taking the necessary steps to achieve their dream of being parents.

IVF vs IUI: Which Fertility Treatment Is Right for You?

When you’re trying to conceive and fertility treatment has become part of your journey, one question often comes up: IVF vs IUI—which is better?

The answer is not the same for every couple.

Intrauterine insemination (IUI) and in vitro fertilisation (IVF) are different fertility treatments used for different clinical situations. IUI is generally less invasive and less expensive, while IVF is a more advanced treatment in which eggs are retrieved and fertilised in a laboratory before an embryo is transferred to the uterus.

The choice between IUI and IVF depends on several factors, including:

  • Age of the female partner
  • Duration of infertility
  • Cause of infertility
  • Ovulation status
  • Fallopian tube condition
  • Sperm count and motility
  • Ovarian reserve
  • Previous fertility treatments
  • Other medical conditions
  • Patient preferences and treatment goals

There is therefore no universal answer to “IVF vs IUI, which is better?” A fertility specialist can recommend an appropriate treatment after evaluating both partners.

IVF vs IUI: Quick Comparison

Factor IUI IVF
Full form Intrauterine Insemination In Vitro Fertilisation
Where fertilisation occurs Inside the reproductive tract In a laboratory
Egg retrieval No Yes
Embryo created in laboratory No Yes
Procedure complexity Less invasive More involved
Typical treatment cost Lower Higher
Treatment duration Usually shorter Usually longer
Useful for Selected infertility cases A wider range of infertility conditions
Multiple pregnancy risk Can increase with ovarian stimulation Can be reduced with single embryo transfer
Treatment choice Depends on diagnosis Depends on diagnosis

The table is a general comparison. Your fertility specialist may recommend a different approach depending on your individual medical circumstances.


What Is IUI?

IUI (Intrauterine Insemination) is a fertility treatment in which specially prepared sperm are placed directly inside the uterus around the time of ovulation.

The aim is to place a higher concentration of motile sperm closer to the fallopian tubes, where fertilisation can occur naturally.

IUI may be performed during a natural ovulatory cycle or together with medicines that stimulate ovulation, depending on the patient’s fertility diagnosis.

How Does IUI Work?

A typical IUI cycle may involve:

  1. Monitoring the menstrual cycle and ovulation.
  2. Using fertility medicines when clinically appropriate.
  3. Monitoring follicular development through ultrasound.
  4. Preparing a semen sample in the laboratory.
  5. Placing the prepared sperm into the uterus using a thin catheter.
  6. Monitoring for pregnancy after the procedure.

The actual insemination procedure is usually brief and does not generally require anaesthesia.

IUI does not involve egg retrieval or laboratory fertilisation.


What Is IVF?

IVF (In Vitro Fertilisation) is an assisted reproductive technology in which eggs are retrieved from the ovaries and fertilised with sperm in a laboratory.

After fertilisation, embryos are cultured, and one or more embryos may be transferred into the uterus.

A typical IVF cycle may involve:

  1. Ovarian stimulation
  2. Ultrasound and hormone monitoring
  3. Trigger medication when appropriate
  4. Egg retrieval
  5. Fertilisation with sperm
  6. Embryo culture
  7. Embryo transfer or freezing
  8. Pregnancy testing

Depending on the treatment plan, additional procedures such as ICSI, embryo freezing or genetic testing may be considered.


IVF vs IUI: What Is the Main Difference?

The biggest difference between IUI and IVF is where fertilisation occurs.

With IUI, sperm are placed inside the uterus and fertilisation must occur naturally within the reproductive tract.

With IVF, eggs are retrieved and fertilised in a laboratory. The resulting embryo is then transferred into the uterus.

This makes IVF a more involved treatment, but it also allows fertility specialists to address a broader range of fertility problems.


When Is IUI Recommended?

IUI may be considered for selected patients with:

Unexplained Infertility

IUI with ovarian stimulation is commonly used as an initial treatment approach for many couples with unexplained infertility.

Current guidance supports treatment pathways that may progress from less invasive approaches such as stimulated IUI to IVF when appropriate. (asrm.org)

Mild Male-Factor Infertility

IUI may be considered when sperm parameters are suitable for insemination after evaluation and processing.

The decision should not be based on a single semen analysis result.

Ovulation Problems

Women with ovulation disorders may sometimes undergo ovulation induction followed by IUI, depending on the underlying condition.

Selected Cases of Cervical-Factor Infertility

IUI can bypass the cervix by placing prepared sperm directly into the uterus.

Donor Sperm Treatment

IUI may also be used with donor sperm when clinically appropriate.

The suitability of IUI depends on factors such as ovarian function, ovulation, fallopian tube status, sperm quality and age.


When Is IVF Recommended?

IVF may be considered when there is a medical reason for a more advanced fertility treatment or when simpler treatments have not been successful.

Potential situations include:

Blocked or Severely Damaged Fallopian Tubes

Because IVF bypasses the fallopian tubes during fertilisation, it may be recommended when the tubes are blocked or significantly damaged.

Severe Male-Factor Infertility

IVF, often combined with ICSI when indicated, may be considered for severe sperm abnormalities or certain situations involving very low or absent sperm in the ejaculate.

Repeatedly Unsuccessful IUI

If appropriately selected IUI cycles do not result in pregnancy, a fertility specialist may recommend moving to IVF.

The number of IUI cycles before IVF is not identical for every patient.

Reduced Ovarian Reserve or Age-Related Fertility Decline

Age and ovarian reserve are important when deciding how quickly to progress through fertility treatment.

For some patients, proceeding directly to IVF may be discussed rather than spending several cycles on less effective treatments.

Endometriosis

Depending on the severity of endometriosis, age and other fertility factors, IVF may be considered.

Genetic or Chromosomal Indications

IVF may be used when preimplantation genetic testing is being considered for an appropriate medical indication.

Other Infertility Factors

IVF may also be recommended when multiple fertility factors are present or when other treatments are unlikely to provide a reasonable opportunity for pregnancy.


IVF vs IUI for Male Infertility

Male-factor infertility can influence the choice between IUI and IVF.

A semen analysis evaluates several important parameters, including:

  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Semen volume

IUI may be suitable when there is an adequate number of motile sperm after semen processing.

When sperm abnormalities are more severe, IVF with ICSI (Intracytoplasmic Sperm Injection) may be considered.

ICSI involves injecting a single sperm directly into an egg. It is particularly relevant when there is a clear male-factor indication or a history of fertilisation failure. Current ASRM guidance cautions against using ICSI routinely for non-male-factor infertility without a specific indication. (asrm.org)


IVF vs IUI for Female Infertility

Female fertility can be affected by the ovaries, fallopian tubes, uterus, hormones and age.

IUI may be considered when:

  • At least one fallopian tube is functioning
  • Ovulation can be achieved
  • Sperm parameters are suitable
  • There is no major uterine or tubal factor requiring IVF

IVF may be considered when:

  • Both fallopian tubes are blocked
  • Ovarian reserve is reduced
  • There are significant fertility factors
  • Previous IUI treatment has failed
  • Age or other circumstances make a more direct treatment approach appropriate

A complete fertility evaluation helps determine which treatment is appropriate.


IVF vs IUI Success Rate

One of the most common searches is “IUI vs IVF success rate.”

However, quoting one fixed success percentage can be misleading.

Success depends on factors such as:

  • Age
  • Diagnosis
  • Ovarian reserve
  • Egg and embryo quality
  • Sperm quality
  • Number of treatment attempts
  • Treatment protocol
  • Previous fertility history
  • Clinic and laboratory factors

IVF generally offers a higher chance of pregnancy per treatment cycle than IUI for many infertility situations, but the comparison should be made using the same outcome measure and patient population.

A clinic should therefore not promise a specific pregnancy or live-birth rate without considering the individual patient’s circumstances.

For patients with unexplained infertility, evidence-based guidelines support stimulated IUI as a treatment option before IVF in many cases, while also recognising that factors such as age and treatment history can change the treatment pathway. (asrm.org)


IVF vs IUI Cost

Cost is another important factor when comparing IUI vs IVF.

Generally, IUI costs less per treatment cycle because it does not involve egg retrieval, laboratory fertilisation or embryo culture.

IVF usually costs more because it involves ovarian stimulation, monitoring, egg retrieval, laboratory fertilisation, embryo culture and embryo transfer.

However, the total cost can vary significantly depending on:

  • Medicines and injections
  • Diagnostic tests
  • Number of treatment cycles
  • ICSI
  • Embryo freezing
  • Frozen embryo transfer
  • Genetic testing
  • Donor eggs or sperm
  • Other clinically indicated procedures

Therefore, rather than relying on a single online price, ask the fertility clinic for a personalised treatment estimate and clarify what is included.

For information about local treatment pricing, see our IVF treatment cost in Srinagar and IUI treatment in Srinagar pages.


IUI vs IVF: Which Is More Painful?

Both IUI and IVF can involve some discomfort, but the experience varies from person to person.

IUI

IUI is generally a short procedure. Some women experience mild cramping or temporary discomfort when the catheter is inserted.

IVF

IVF involves more steps and usually includes injectable ovarian stimulation and an egg-retrieval procedure.

Egg retrieval is generally performed with appropriate pain relief or sedation, in accordance with the clinic’s protocol.

Therefore, it is not accurate to describe IVF simply as “painful” or IUI as completely “painless.” Individual experiences vary.


IUI vs IVF: Treatment Duration

IUI usually involves fewer treatment steps than IVF.

An IUI cycle may involve:

  • Cycle monitoring
  • Ovulation induction when required
  • Trigger medication when appropriate
  • Sperm preparation
  • Insemination
  • Pregnancy testing

IVF generally involves more appointments and procedures, including ovarian stimulation, monitoring, egg retrieval, fertilisation and embryo transfer.

The total IVF timeline varies depending on the treatment protocol and whether a fresh or frozen embryo transfer is planned.


Benefits and Limitations of IUI

Potential Benefits of IUI

  • Less invasive than IVF
  • Usually lower cost per cycle
  • Does not require egg retrieval
  • Short procedure
  • May be appropriate for selected infertility diagnoses

Limitations of IUI

  • Not suitable for every infertility condition
  • Requires suitable sperm parameters
  • Usually requires at least one functioning fallopian tube
  • Success can be lower per cycle than IVF
  • Several cycles may be needed
  • Ovarian stimulation can increase the risk of multiple pregnancy

Benefits and Limitations of IVF

Potential Benefits of IVF

  • Can bypass blocked fallopian tubes
  • Useful for many forms of infertility
  • Allows fertilisation to occur in the laboratory
  • Embryos can be frozen for future use
  • ICSI can be used when indicated
  • Genetic testing may be considered in selected cases
  • Can provide a treatment pathway when other fertility treatments have failed

Limitations of IVF

  • More invasive than IUI
  • Usually more expensive
  • Requires ovarian stimulation and egg retrieval
  • Takes more time and monitoring
  • Does not guarantee pregnancy
  • May involve additional procedures and costs

IVF vs IUI: Which One Is Better?

There is no universal answer to “Which is better, IUI or IVF?”

The more appropriate question is:

Which treatment is more suitable for my fertility diagnosis?

IUI may be a reasonable option when the fertility factors are relatively favourable and less invasive treatment is appropriate.

IVF may be more appropriate when there are significant tubal, sperm, ovarian, age-related or other fertility factors, or when previous treatments have not worked.

For some couples, starting with IUI may be appropriate. For others, moving directly to IVF may be discussed.

The WHO’s 2025 infertility guideline also emphasises evidence-based, patient-centred fertility care and progression from simpler to more complex treatment according to the individual’s clinical situation. (who.int)


IVF vs IUI: How Does a Doctor Decide?

Before recommending IUI or IVF, your fertility specialist may assess:

Female Partner

  • Age
  • Menstrual cycle
  • Ovulation
  • Ovarian reserve
  • Fallopian tubes
  • Uterus
  • Previous pregnancies
  • Previous fertility treatment

Male Partner

  • Semen analysis
  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Previous fertility history
  • Relevant medical conditions

Couple

  • Duration of infertility
  • Cause of infertility
  • Previous treatment outcomes
  • Genetic considerations
  • Financial and practical preferences
  • Time available for treatment

This assessment helps the fertility team develop an individualised treatment plan.


Can IUI Be Converted to IVF?

Yes. Fertility treatment is often progressive.

A couple may begin with IUI when it is clinically appropriate. If pregnancy does not occur after an appropriate number of cycles, or if new information changes the diagnosis, the fertility specialist may recommend IVF.

For unexplained infertility, ASRM guidance has historically supported a limited course of stimulated IUI followed by IVF when unsuccessful, while age and individual circumstances can influence whether IVF is considered earlier. (asrm.org)


IVF vs IUI Frequently Asked Questions

Is IUI better than IVF?

Neither treatment is universally better. IUI is less invasive and generally less expensive, while IVF can be appropriate for a broader range of infertility conditions. The right treatment depends on the couple’s diagnosis and circumstances.

Is IVF more successful than IUI?

IVF generally has a higher pregnancy potential per treatment cycle than IUI in many clinical situations, but success varies significantly with age, diagnosis and other factors. Comparing percentages without considering the patient population can be misleading.

Is IUI cheaper than IVF?

Generally, yes. IUI usually has a lower per-cycle cost because it does not involve egg retrieval or laboratory embryo development. However, total treatment costs vary.

How many IUI cycles should I try before IVF?

There is no single number for every patient. The decision depends on age, diagnosis, ovarian reserve, sperm parameters and previous treatment. In selected cases of unexplained infertility, several stimulated IUI cycles may be considered before IVF. (asrm.org)

Can IUI work with low sperm count?

It may be possible in selected cases, depending on the severity of the sperm abnormality and the number of motile sperm available after processing. Severe male-factor infertility may require IVF with ICSI.

Can IUI work with blocked fallopian tubes?

IUI generally requires at least one functioning fallopian tube because fertilisation still occurs inside the reproductive tract. If both tubes are blocked, IVF may be considered.

Is IVF painful?

IVF involves more procedures than IUI, including injections and egg retrieval. Pain and discomfort vary between individuals, and clinics use appropriate pain relief or sedation for egg retrieval.

Does IVF guarantee pregnancy?

No. IVF can provide an effective fertility treatment option, but it does not guarantee pregnancy or a live birth.

Which is better for older women: IUI or IVF?

Age is an important factor in fertility treatment planning. Depending on age, ovarian reserve, diagnosis and time available for treatment, a fertility specialist may discuss IVF sooner rather than spending multiple cycles on IUI.


IVF vs IUI in Srinagar

If you are searching for IVF vs IUI in Srinagar, the first step is to understand why pregnancy has not occurred.

At Imprimis IVF & Fertility Centre, Srinagar, a fertility specialist can evaluate both partners and discuss whether IUI, IVF or another fertility treatment is appropriate.

The evaluation may include assessment of ovulation, ovarian reserve, fallopian tubes, semen parameters and other relevant fertility factors.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

Treatment recommendations should be based on an individual medical evaluation rather than an online comparison.


Final Thoughts: IVF vs IUI

IVF and IUI are not competing treatments where one is always better than the other.

IUI is a less invasive fertility treatment that may be suitable for selected couples. IVF is a more involved treatment that can address a wider range of fertility problems.

The most appropriate option depends on your:

  • Age
  • Fertility diagnosis
  • Ovarian reserve
  • Ovulation
  • Fallopian tube status
  • Sperm parameters
  • Previous treatment
  • Overall reproductive health

If you are unsure whether IUI or IVF is right for you, consult a qualified fertility specialist for an individual assessment.


Medical Reviewer & Editorial Information

Medical Reviewer: Imprimis IVF

Last Updated: September 19, 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar

Medical Disclaimer: This article is intended for general educational purposes and does not replace professional medical advice, diagnosis or treatment. Fertility treatment should be selected after an appropriate evaluation by a qualified fertility specialist. Individual treatment outcomes vary.

Medical References: World Health Organization (WHO) 2025 Guideline for the Prevention, Diagnosis and Treatment of Infertility; American Society for Reproductive Medicine (ASRM) guidance; European Society of Human Reproduction and Embryology (ESHRE) guidance.

Recurrent Pregnancy Loss: Causes, Diagnosis & Treatment

Experiencing a miscarriage can be emotionally and physically difficult. While miscarriage is relatively common, recurrent pregnancy loss (RPL) requires medical evaluation to understand whether an underlying cause may be contributing to repeated pregnancy losses.

Recurrent pregnancy loss is a distinct reproductive health condition and is different from infertility. According to the latest American Society for Reproductive Medicine (ASRM) guidance, recurrent pregnancy loss is defined as two or more spontaneous pregnancy losses, excluding confirmed molar or ectopic pregnancies. The losses do not necessarily have to occur consecutively.

Many miscarriages, particularly those occurring early in pregnancy, are related to chromosomal abnormalities in the embryo. The likelihood of chromosomal abnormalities also increases with maternal age. However, recurrent pregnancy loss can have several possible causes, and sometimes no single cause is identified even after a detailed evaluation.

If you have experienced repeated miscarriages, consulting an experienced fertility specialist or obstetrician-gynaecologist can help determine whether further testing or treatment is appropriate.

What Is Recurrent Pregnancy Loss?

Recurrent pregnancy loss (RPL) refers to repeated spontaneous pregnancy losses.

Current ASRM guidance defines RPL as the spontaneous loss of two or more pregnancies, excluding confirmed molar and ectopic pregnancies. Pregnancy losses do not have to be consecutive for evaluation to be considered.

The term recurrent miscarriage is also commonly used. Older medical literature may use the term recurrent abortion, but “recurrent pregnancy loss” is generally preferred for patient-focused medical communication.

Recurrent pregnancy loss can be associated with genetic, anatomical, hormonal, metabolic, immune-related and other factors. In some couples, no clear cause is identified.


What Causes Recurrent Pregnancy Loss?

Causes Recurrent Pregnancy Loss

There is no single cause of recurrent miscarriage. A detailed evaluation may consider several factors involving the embryo, chromosomes, uterus, hormones, metabolism, and the health of both partners.

1. Chromosomal Abnormalities

Chromosomal abnormalities are an important cause of early pregnancy loss.

Approximately 50%–60% of first-trimester miscarriages are associated with embryonic aneuploidy, and the likelihood of aneuploidy is strongly influenced by maternal age.

Most chromosomal abnormalities occur sporadically during egg or embryo development. In some cases, however, chromosome abnormalities involving one of the parents may contribute to recurrent pregnancy loss.

When possible, chromosome testing of miscarriage tissue may provide useful information during recurrent pregnancy loss evaluation. The latest ASRM guidance recommends chromosome analysis of pregnancy-loss tissue, when feasible, as an important part of evaluation.

2. Uterine Abnormalities

Problems affecting the structure of the uterus may contribute to pregnancy loss in some women.

These may include:

  • Uterine septum
  • Certain congenital uterine anomalies
  • Fibroids
  • Endometrial polyps
  • Intrauterine adhesions

Your fertility specialist may recommend imaging or other investigations based on your history and symptoms.

3. Antiphospholipid Syndrome

Antiphospholipid syndrome (APS) is an autoimmune condition associated with abnormal blood clotting and specific pregnancy complications.

APS is an established and potentially treatable cause of recurrent pregnancy loss. Testing may be recommended when a patient’s history suggests an increased risk.

Treatment for confirmed obstetric APS may include medications such as low-dose aspirin and heparin under specialist supervision. These medicines should not be started without medical advice. Current evidence does not support routinely prescribing aspirin or anticoagulants to everyone with recurrent pregnancy loss.

4. Thyroid and Metabolic Conditions

Certain medical conditions may be associated with pregnancy loss.

Depending on the individual’s history, evaluation may include conditions such as:

  • Thyroid disease
  • Diabetes
  • Other metabolic disorders

The latest ASRM guidance supports targeted assessment for conditions such as thyroid disease and diabetes when clinically appropriate.

5. Age-Related Factors

Maternal age is an important factor in miscarriage risk because chromosomal abnormalities in eggs and embryos become more common with increasing age.

This does not mean that pregnancy after 35 is impossible or necessarily unsuccessful. However, age should be considered when evaluating recurrent pregnancy loss and planning future pregnancy.

6. Other Factors

Depending on the clinical history, doctors may also consider:

  • Genetic factors
  • Certain anatomical conditions
  • Lifestyle factors
  • Chronic medical conditions
  • Previous pregnancy complications

Not every proposed cause of recurrent miscarriage has strong evidence. Current guidelines recommend targeted evaluation rather than routinely performing every available test.


Recurrent Pregnancy Loss Symptoms

Recurrent Pregnancy Loss Symptoms

Recurrent pregnancy loss itself does not usually have a specific set of symptoms between pregnancies. The main concern is repeated pregnancy loss.

During an individual miscarriage, symptoms may include:

  • Vaginal bleeding or spotting
  • Lower abdominal or pelvic cramping
  • Back pain
  • Passing tissue or clots
  • Decreasing pregnancy symptoms

However, these symptoms do not always mean that a miscarriage is occurring. Bleeding and abdominal pain during pregnancy can have several causes.

Seek urgent medical care if you experience heavy bleeding, severe abdominal or pelvic pain, dizziness, fainting, fever or other concerning symptoms during pregnancy.


When Should You See a Doctor for Recurrent Miscarriage?

If you have experienced two or more pregnancy losses, it is reasonable to discuss recurrent pregnancy loss evaluation with a qualified obstetrician-gynaecologist or fertility specialist. Current ASRM guidance recognises RPL after two spontaneous pregnancy losses.

You should especially seek specialist advice if:

  • You have had two or more miscarriages.
  • You have experienced a second-trimester pregnancy loss.
  • You have irregular menstrual cycles.
  • You have a known uterine abnormality.
  • You have a history suggesting autoimmune or metabolic disease.
  • You or your partner has a known genetic condition.
  • You have been trying to conceive again after repeated pregnancy loss.

Tests for Recurrent Pregnancy Loss

There is no single test that can identify every cause of recurrent pregnancy loss.

Your doctor may recommend targeted investigations based on your pregnancy history, age, previous test results and other health factors.

Common Tests

Depending on the individual situation, evaluation may include:

Genetic Testing

Chromosome testing of pregnancy-loss tissue can help determine whether a chromosomal abnormality contributed to the miscarriage.

In selected cases, parental genetic testing may also be considered.

Uterine Evaluation

Tests used to assess the uterus may include:

The appropriate test depends on the suspected condition.

Antiphospholipid Antibody Testing

Testing for antiphospholipid syndrome may be recommended when clinically appropriate.

Thyroid and Metabolic Assessment

Your doctor may recommend blood tests to assess thyroid function, diabetes or other metabolic conditions depending on your medical history.

Evaluation of Other Health Factors

A detailed medical, reproductive and family history can help determine whether additional investigations are required.


Can Recurrent Pregnancy Loss Be Prevented?

There is no guaranteed way to prevent every miscarriage because many early pregnancy losses are caused by chromosomal abnormalities that occur during embryo development.

However, addressing treatable medical conditions and maintaining good preconception health may support a healthy pregnancy.

Steps That May Support a Healthy Pregnancy

Maintain a Healthy Lifestyle

Aim for a balanced diet, regular physical activity and a healthy weight appropriate for your individual circumstances.

Avoid Smoking and Tobacco

Smoking is associated with adverse reproductive and pregnancy outcomes. Avoid tobacco and exposure to tobacco smoke when planning pregnancy.

Avoid Alcohol During Pregnancy

Alcohol should be avoided during pregnancy.

Review Medications Before Pregnancy

Speak with your doctor before starting, stopping or changing any medication while trying to conceive or during pregnancy.

Manage Existing Health Conditions

Conditions such as diabetes and thyroid disease should be appropriately evaluated and managed before and during pregnancy.

Take Recommended Prenatal Supplements

Your doctor may recommend folic acid and other prenatal supplements based on your individual needs.

Attend Preconception Care

A preconception consultation can help identify medical or reproductive factors that may need attention before another pregnancy.


Recurrent Pregnancy Loss Treatment

Recurrent Pregnancy Loss Treatment

Treatment for Recurrent Miscarriage depends on the underlying cause.

There is no single treatment that works for every couple.

After evaluation, treatment may involve:

  • Management of thyroid or metabolic conditions
  • Treatment of confirmed antiphospholipid syndrome
  • Treatment of certain uterine abnormalities
  • Genetic counselling
  • Fertility treatment where appropriate
  • Psychological and emotional support

Current guidelines emphasise evidence-based, targeted treatment and caution against the routine use of tests or therapies that have not demonstrated clear benefit.


Treatment for Uterine Abnormalities

If a uterine abnormality is identified and is considered relevant to the pregnancy losses, treatment may sometimes be recommended.

Depending on the condition, treatment can include procedures such as hysteroscopic surgery.

For example, a uterine septum may be treated surgically in selected patients after appropriate evaluation and counselling.

The decision to operate should be individualised rather than based solely on an ultrasound finding.


Treatment for Antiphospholipid Syndrome

Women with confirmed obstetric antiphospholipid syndrome may benefit from specific treatment during pregnancy.

Depending on the clinical situation, a specialist may prescribe low-dose aspirin and heparin or another appropriate anticoagulant.

These medications are not appropriate for everyone with recurrent miscarriage or for people without a confirmed indication. They can have important side effects and should only be used under medical supervision.


Can IVF Help With Recurrent Pregnancy Loss?

IVF is not automatically required for Recurrent Miscarriage

Many couples with recurrent pregnancy loss can achieve a successful pregnancy without IVF, depending on the cause, age and other fertility factors.

However, IVF may be considered when there is another indication for assisted reproductive treatment or in selected couples where genetic factors are relevant.

IVF allows eggs to be fertilised in the laboratory and embryos to be transferred to the uterus.

IVF and Genetic Testing

In selected cases, preimplantation genetic testing (PGT) may be discussed when there is a known genetic or chromosomal indication.

However, PGT is not a universal treatment for recurrent pregnancy loss. The benefits, limitations, cost and possibility of obtaining a suitable embryo should be discussed with a fertility specialist.

Current ASRM guidance notes that evidence concerning PGT-A in recurrent pregnancy loss is still nuanced, and treatment should be individualised rather than offered routinely to every patient with RPL.


Chances of a Successful Pregnancy

Experiencing recurrent miscarriage does not mean that a future healthy pregnancy is impossible.

The outcome depends on several factors, including:

  • Maternal age
  • Number and timing of previous pregnancy losses
  • Chromosomal findings
  • Underlying medical conditions
  • Uterine factors
  • Whether a treatable cause is identified

Importantly, many cases remain unexplained even after evaluation. The latest ASRM guidance reports that 50%–80% of patients with unexplained recurrent pregnancy loss may go on to have a successful pregnancy, depending on individual circumstances.

Your individual prognosis should be discussed with your fertility specialist rather than estimated from a general percentage.


Emotional Support After Recurrent Miscarriage

Recurrent Miscarriage can be emotionally challenging for both partners.

Feelings of sadness, anxiety, grief, frustration or fear during a subsequent pregnancy are understandable.

Psychological support and counselling are an important part of recurrent pregnancy loss care. Current ASRM guidance specifically recommends emotional support for patients and couples experiencing RPL.

Seeking professional support does not mean that your concerns are being dismissed. Emotional wellbeing is an important part of reproductive healthcare.


Recurrent Pregnancy Loss Treatment in Srinagar

If you are looking for recurrent pregnancy loss treatment in Srinagar, an evaluation by a fertility specialist can help identify possible causes and determine whether further investigations or treatment are appropriate.

At Imprimis IVF & Fertility Centre, Srinagar, couples can seek fertility evaluation and discuss recurrent miscarriage, infertility and available fertility treatment options.

The centre provides fertility-related services including infertility evaluation, IUI and IVF treatment.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

If you have experienced repeated miscarriages, consult a qualified fertility specialist before starting medicines or fertility treatment on your own.


Frequently Asked Questions

What is recurrent pregnancy loss?

Recurrent pregnancy loss is generally defined as two or more spontaneous pregnancy losses. Current ASRM guidance does not require the losses to be consecutive.

Is recurrent abortion the same as recurrent miscarriage?

The terms may be used to describe repeated pregnancy loss, but recurrent pregnancy loss (RPL) is the preferred modern clinical terminology for patient education.

How many miscarriages are considered recurrent pregnancy loss?

Current ASRM guidance defines recurrent pregnancy loss as two or more spontaneous pregnancy losses.

What is the most common cause of recurrent miscarriage?

Chromosomal abnormalities are a major cause of early pregnancy loss. However, recurrent pregnancy loss can have several possible causes, and some cases remain unexplained.

Can PCOS cause recurrent miscarriage?

PCOS may be associated with certain reproductive and metabolic risks, but recurrent pregnancy loss should not automatically be attributed to PCOS. A proper medical evaluation is needed to identify possible contributing factors.

Can thyroid problems cause recurrent miscarriage?

Thyroid disorders can affect reproductive and pregnancy health. Appropriate thyroid assessment may be part of the evaluation of recurrent pregnancy loss when clinically indicated.

Can recurrent pregnancy loss be treated?

Yes, in some cases an underlying cause can be identified and treated. However, there is no single treatment for all cases of recurrent pregnancy loss.

Is IVF necessary after recurrent miscarriage?

No. IVF is not automatically required after recurrent miscarriage. It may be considered when there is another indication for IVF or in selected situations involving genetic or fertility factors.

Can IVF prevent miscarriage?

IVF cannot guarantee that miscarriage will be prevented. In selected cases, IVF with appropriate genetic testing may be discussed, but it is not a universal treatment.

Should I take aspirin or heparin after repeated miscarriages?

Do not start aspirin or heparin without medical advice. These medications may be appropriate for selected patients, particularly those with confirmed antiphospholipid syndrome, but they are not routinely recommended for everyone.

Can I have a healthy pregnancy after recurrent miscarriage?

Yes. Many people with recurrent pregnancy loss subsequently have a successful pregnancy. Your individual chances depend on factors such as age, medical history, previous pregnancy losses and whether an underlying cause is identified.


Take the Next Step After Recurrent Pregnancy Loss

Experiencing repeated pregnancy loss can be difficult, but it does not mean that a successful pregnancy is impossible.

The right approach is to identify possible causes, treat conditions that can be addressed and develop an individualised pregnancy or fertility plan.

If you have experienced two or more pregnancy losses, consider speaking with a qualified fertility specialist or obstetrician-gynaecologist for appropriate evaluation.

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 979775611

Medical Reviewer: Imprimis IVF & Fertility Centre Team

Last Updated: September 19, 2026

Female Infertility: Causes, Symptoms, Tests & Treatment

Female infertility is a common reproductive health concern that can make it difficult to conceive or maintain a pregnancy. It may be related to problems with ovulation, the ovaries, fallopian tubes, uterus, hormones or other reproductive factors.

Infertility does not always have a single identifiable cause. Sometimes both partners contribute, while in other cases no clear cause is found.

If you are trying to conceive, understanding the causes of female infertility, female infertility symptoms, fertility tests and treatment options can help you understand when professional evaluation may be appropriate.

What Is Female Infertility?

Female infertility refers to difficulty achieving pregnancy because of factors affecting the female reproductive system.

Infertility is generally defined as not achieving pregnancy after 12 months of regular, unprotected sexual intercourse. For women aged 35 or older, fertility evaluation is generally recommended after 6 months of trying, while women over 40 may benefit from more immediate evaluation. Earlier assessment may also be appropriate when there are known fertility risk factors.

Female infertility can be associated with problems involving:

  • Ovulation
  • Ovarian function
  • Fallopian tubes
  • Uterus
  • Endometrium
  • Reproductive hormones
  • Ovarian reserve
  • Endometriosis
  • Genetic or structural conditions

The WHO notes that infertility may result from disorders affecting the ovaries, uterus, fallopian tubes and endocrine system.

Primary and Secondary Infertility

Female infertility can occur as primary infertility or secondary infertility.

Primary Infertility

Primary infertility refers to difficulty achieving a pregnancy when there has been no previous pregnancy.

Secondary Infertility

Secondary infertility refers to difficulty becoming pregnant after having achieved at least one previous pregnancy.

Both types may require evaluation to identify possible reproductive, hormonal, anatomical or other contributing factors.

What Causes Female Infertility?

There are many possible causes of female infertility. Some affect ovulation, while others involve the ovaries, fallopian tubes, uterus or reproductive hormones.

Common causes include:

  • PCOS and ovulation disorders
  • Endometriosis
  • Blocked or damaged fallopian tubes
  • Uterine fibroids
  • Uterine polyps or structural abnormalities
  • Diminished ovarian reserve
  • Primary ovarian insufficiency
  • Hormonal disorders
  • Pelvic infections
  • Previous pelvic surgery
  • Age-related decline in fertility
  • Certain medical treatments
  • Unexplained infertility

PCOS and Female Infertility

Polycystic ovary syndrome (PCOS) is a common hormonal and metabolic condition that can affect reproductive health.

PCOS may cause irregular or absent periods, abnormal ovulation, excess androgen levels, acne and excess facial or body hair. Because ovulation may occur irregularly or not occur, PCOS can make conception more difficult. WHO describes PCOS as one of the leading causes of infertility associated with abnormal ovulation.

Read more about PCOS and fertility.

Endometriosis

Endometriosis occurs when tissue similar to the lining of the uterus grows outside the uterus.

It can be associated with pelvic pain, painful periods, pain during sexual intercourse and difficulty conceiving. Endometriosis may affect fertility through inflammation, adhesions and changes involving the reproductive organs.

Read more about endometriosis.

Blocked or Damaged Fallopian Tubes

The fallopian tubes provide the pathway where sperm and egg normally meet.

Blocked or damaged tubes can interfere with fertilisation and may prevent the embryo from travelling normally toward the uterus.

Possible causes include:

  • Previous pelvic infections
  • Sexually transmitted infections
  • Pelvic inflammatory disease
  • Previous pelvic surgery
  • Endometriosis
  • Certain abdominal or pelvic conditions

Tubal disease is an important part of infertility evaluation, and tests such as HSG or sonohysterography may be used to assess tubal patency.

Learn more about blocked fallopian tubes.

Uterine Fibroids

Uterine fibroids are non-cancerous growths that develop in or around the uterus.

Many women with fibroids can conceive normally, but depending on their size and location, some fibroids may affect fertility or pregnancy.

Read more about uterine fibroids.

Ovarian Cysts

Ovarian cysts are fluid-filled structures that can develop in or on the ovaries.

Many ovarian cysts are temporary and do not affect fertility. However, certain conditions associated with ovarian cysts, including endometriosis or PCOS, may affect reproductive function.

Read more about ovarian cysts.

Diminished Ovarian Reserve

Ovarian reserve refers broadly to the remaining supply of eggs in the ovaries.

Ovarian reserve generally declines with age. Tests such as AMH, antral follicle count, and FSH/estradiol may be used as part of a fertility evaluation when clinically appropriate.

Importantly, ovarian reserve testing should be interpreted alongside age, medical history and other fertility findings. A low ovarian-reserve test does not by itself mean that natural pregnancy is impossible.

Primary Ovarian Insufficiency

Primary ovarian insufficiency (POI) occurs when normal ovarian function is lost before the age of 40.

It can affect ovulation and fertility and requires medical evaluation.

Read more about primary ovarian insufficiency.

Hormonal Disorders

Hormonal changes can interfere with ovulation and menstrual cycles.

Depending on the symptoms and medical history, a doctor may investigate hormones such as:

  • FSH
  • LH
  • Estradiol
  • TSH
  • Prolactin
  • Androgens

Not every hormone test is required for every woman. Testing should be based on the clinical situation.

Read more about the role of hormones in fertility.

Age and Female Fertility

Age is an important factor affecting female fertility.

Female fertility generally declines with increasing age because both the number and quality of available eggs decrease. The decline becomes more clinically significant during the later reproductive years.

For women aged 35 and older who have been trying to conceive for six months, fertility evaluation is generally recommended. Women over 40 may benefit from more immediate evaluation.

Unexplained Infertility

Sometimes fertility testing does not identify a clear reason for difficulty conceiving. This is known as unexplained infertility.

A normal initial evaluation does not mean that the fertility problem is imaginary or that pregnancy cannot occur. Your fertility specialist can discuss treatment options based on age, duration of infertility, previous pregnancies and other clinical factors.

Risk Factors for Female Infertility

Several factors may affect female reproductive health and fertility, including:

  • Increasing age
  • PCOS
  • Endometriosis
  • Previous pelvic infection
  • Previous pelvic surgery
  • Smoking
  • Excessive alcohol consumption
  • Significant underweight or obesity
  • Certain medications
  • Chemotherapy or radiation treatment
  • Some genetic or medical conditions
  • Certain environmental exposures

Not every woman with a risk factor will experience infertility.

What Are the Symptoms of Female Infertility?

Infertility itself may not cause noticeable symptoms. Difficulty becoming pregnant is often the main sign.

However, certain symptoms may indicate an underlying reproductive condition that deserves medical evaluation.

These may include:

  • Irregular or absent periods
  • Very heavy menstrual bleeding
  • Severe period pain
  • Pelvic pain
  • Pain during sexual intercourse
  • Symptoms of PCOS
  • Excess facial or body hair
  • Persistent acne associated with hormonal changes
  • Symptoms of thyroid or hormonal disorders
  • Previous pelvic infections
  • Repeated pregnancy loss

These symptoms do not automatically mean that a woman is infertile. They may indicate an underlying condition that should be evaluated.

For example, severe menstrual pain can be associated with endometriosis, which may affect fertility.

When Should You See a Fertility Specialist?

Consider a fertility evaluation if:

  • You are under 35 and have tried to conceive for 12 months without pregnancy.
  • You are 35 or older and have tried for 6 months without pregnancy.
  • You are over 40 and are planning pregnancy.
  • You have irregular or absent periods.
  • You have known or suspected endometriosis.
  • You have a history of blocked fallopian tubes.
  • You have undergone pelvic surgery.
  • You have a history of chemotherapy or radiation.
  • You have a known condition that may affect fertility.
  • Your partner has a known fertility problem.

Evaluation may be recommended earlier when there is a known condition associated with infertility.

How Is Female Infertility Diagnosed?

A female infertility evaluation usually begins with a detailed medical and reproductive history.

Your fertility specialist may ask about:

  • Menstrual cycle pattern
  • Previous pregnancies
  • Duration of infertility
  • Previous miscarriages
  • Pelvic pain
  • Previous surgeries
  • Previous infections
  • Medical conditions
  • Medications
  • Family history
  • Previous fertility treatments

The evaluation generally looks at three important areas:

  1. Ovulation
  2. Ovarian function and reserve
  3. The uterus and fallopian tubes

Male-partner evaluation should also be considered because infertility can involve male factors, female factors or both.

Female Infertility Tests

Depending on your symptoms and medical history, fertility tests may include:

1. Pelvic Examination

A physical and pelvic examination may help identify certain reproductive or anatomical problems.

2. Blood Tests

Blood tests may be used to evaluate hormones and other factors relevant to ovulation and reproductive health.

3. AMH Test

Anti-Müllerian hormone (AMH) may be used as one measure of ovarian reserve.

AMH should not be interpreted as a standalone fertility test. It is used alongside age, ultrasound findings and other clinical information.

4. Antral Follicle Count

An antral follicle count (AFC) is performed using transvaginal ultrasound and can help assess ovarian response and reserve.

5. Transvaginal Ultrasound

A transvaginal ultrasound can evaluate the uterus and ovaries and may identify conditions such as fibroids, ovarian cysts or other structural abnormalities.

6. HSG Test

Hysterosalpingography (HSG) is an imaging test used to assess the uterine cavity and whether the fallopian tubes are open.

Read more about the HSG test for infertility.

7. Sonohysterography

Sonohysterography uses ultrasound with fluid introduced into the uterus to assess the uterine cavity and, in some techniques, tubal patency.

8. Hysteroscopy

Hysteroscopy allows a doctor to directly examine the inside of the uterus and may be recommended when a uterine cavity problem is suspected.

9. Laparoscopy

Laparoscopy is a minimally invasive surgical procedure that may be considered in selected cases, particularly when conditions such as endometriosis or pelvic pathology are suspected.

It is not routinely required for every infertility evaluation.

Female Infertility Treatment

The appropriate female infertility treatment depends on the underlying cause, age, ovarian reserve, duration of infertility, previous pregnancy history, partner’s fertility status and other medical factors.

Treatment options may include:

Lifestyle and Preconception Care

Depending on an individual’s circumstances, improving overall health, maintaining a healthy weight, avoiding smoking and recreational drug use, and managing medical conditions may support reproductive health.

Ovulation-Induction Medicines

Women with ovulation disorders may be treated with medicines designed to help induce or regulate ovulation.

PCOS-related infertility is one situation in which ovulation-induction treatment may be considered.

Treatment for Endometriosis

Treatment for endometriosis depends on symptoms, disease severity, fertility goals and individual circumstances.

Surgery may be considered in selected cases, while assisted reproductive treatment may also be discussed.

Treatment for Tubal Problems

Treatment depends on the location and severity of tubal damage.

In selected cases, tubal surgery may be considered. For other patients, IVF may be an appropriate treatment option.

Treatment for Uterine Conditions

Fibroids, polyps, adhesions and other uterine abnormalities may require medical or surgical treatment depending on their size, location and impact on fertility.

IUI

Intrauterine insemination (IUI) involves placing prepared sperm into the uterus around the time of ovulation.

IUI may be considered for selected fertility problems depending on the couple’s diagnosis.

Learn more about IUI treatment in Srinagar.

IVF

In vitro fertilisation (IVF) involves retrieving eggs from the ovaries, fertilising them in a laboratory and transferring a resulting embryo into the uterus.

IVF may be considered for several fertility conditions, including some cases of tubal disease, endometriosis, diminished ovarian reserve and unexplained infertility.

Learn more about IVF treatment in Srinagar.

ICSI

Intracytoplasmic sperm injection (ICSI) involves injecting a single sperm directly into an egg during the laboratory fertilisation process.

ICSI is particularly relevant when male-factor infertility or previous fertilisation problems are present.

Read more about ICSI treatment in Srinagar.

Can Female Infertility Be Treated?

In many cases, fertility problems can be treated or managed once the underlying cause is identified.

However, treatment is highly individual. A treatment that is appropriate for one woman may not be appropriate for another.

Your fertility specialist may consider:

  • Age
  • Ovarian reserve
  • Ovulation
  • Fallopian tube status
  • Uterine health
  • Endometriosis
  • Previous pregnancies
  • Male-partner fertility
  • Duration of infertility
  • Previous treatment
  • Overall health

A comprehensive evaluation helps determine the most appropriate treatment pathway.

Frequently Asked Questions About Female Infertility

What is the most common cause of female infertility?

Ovulation disorders are an important cause of female infertility. PCOS is a leading cause of anovulatory infertility, but infertility can also result from tubal, uterine, endometriosis-related, hormonal, ovarian and other factors.

What are the first signs of female infertility?

There may be no obvious symptoms. Difficulty conceiving is often the main indication. Irregular periods, absent periods, severe pelvic pain or other reproductive symptoms may indicate an underlying condition that affects fertility.

Can PCOS cause infertility?

Yes. PCOS can interfere with regular ovulation and is a leading cause of infertility associated with ovulatory dysfunction.

Can endometriosis cause infertility?

Yes. Endometriosis can be associated with difficulty conceiving and may affect the reproductive organs through inflammation and other mechanisms.

What tests are done for female infertility?

Depending on the individual situation, testing may include ultrasound, AMH, antral follicle count, hormone testing, HSG, sonohysterography, hysteroscopy and other investigations.

Is AMH a fertility test?

AMH is primarily a marker used to assess ovarian reserve. It does not independently determine whether a woman can or cannot become pregnant. ASRM recommends interpreting ovarian-reserve testing in the context of the complete clinical picture.

When should I get an infertility test?

Women under 35 generally should consider evaluation after 12 months of trying without pregnancy. Women aged 35 or older should generally seek evaluation after 6 months, while women over 40 may benefit from more immediate evaluation. Earlier evaluation may be appropriate when there are known risk factors.

Can blocked fallopian tubes be treated?

Treatment depends on the location and severity of the blockage. Depending on the diagnosis, surgery or IVF may be considered.

Can female infertility be treated without IVF?

Yes. IVF is not required in every case. Depending on the cause, treatment may include lifestyle measures, ovulation-induction medicines, treatment of underlying conditions, surgery or IUI.

Female Infertility Treatment in Srinagar

If you are having difficulty conceiving, an appropriate fertility evaluation can help identify possible causes and guide treatment.

Imprimis IVF & Fertility Centre, Srinagar provides fertility evaluation and assisted reproductive treatment for couples seeking fertility care.

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: 19th September 2026

Clinic Information

Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014
Services: Fertility evaluation, infertility treatment, IVF, IUI, ICSI and other assisted reproductive services
Phone: 9650777084 / 9797756111

For directions, appointment information and current clinic details, patients should use the clinic’s official contact channels.

Final Thoughts

Female infertility can have many different causes, and identifying the underlying factor is an important first step toward appropriate treatment.

Conditions such as PCOS, endometriosis, blocked fallopian tubes, uterine abnormalities, hormonal disorders and reduced ovarian reserve may affect fertility. Age is also an important factor in female reproductive potential.

If you have been trying to conceive without success, particularly if you are 35 or older or have a known fertility-related condition, consider discussing your situation with a qualified fertility specialist.

Medical Disclaimer: This page is intended for general educational purposes and does not replace an individual medical consultation, diagnosis or treatment plan. Fertility tests and treatment should be selected based on your medical history and a qualified healthcare professional’s evaluation.

Male Infertility: Causes, Symptoms, Tests & Treatment

Male infertility is more common than many people realise. When a couple has difficulty conceiving, fertility problems can involve the male partner, the female partner, or both partners. Therefore, evaluating male fertility is an important part of an infertility assessment.

Male fertility is closely related to sperm count, sperm motility and sperm morphology. Changes in any of these semen parameters can make it more difficult to achieve a pregnancy.

If you and your partner have been trying to conceive without success, understanding the causes, symptoms, diagnosis and treatment of male infertility can help you take the next step.

What Is Male Infertility?

Male infertility refers to difficulty achieving a pregnancy because of factors affecting the male reproductive system. A couple is generally evaluated for infertility when pregnancy has not occurred after 12 months of regular, unprotected sexual intercourse.

Male infertility may be related to problems with sperm production, sperm quality, sperm transport, ejaculation, hormones, genetics or the reproductive organs.

In some men, there are no obvious symptoms. A fertility evaluation may therefore be the first time an underlying problem is identified.

How Common Is Male Infertility?

Infertility affects couples across different age groups and populations, and male factors contribute to a substantial proportion of infertility cases.

Importantly, infertility should not automatically be considered a woman’s problem. Both partners should be evaluated when a couple is experiencing difficulty conceiving.

Male fertility can be affected by several factors, including age, medical conditions, lifestyle habits, hormonal disorders, infections, genetic conditions and problems affecting the testicles or reproductive tract.

What Causes Male Infertility?


The causes of male infertility can be broadly related to sperm production, sperm quality, hormonal function, reproductive anatomy, ejaculation and lifestyle factors.

Some of the most common male infertility causes include:

1. Low Sperm Count

Low sperm count, also called oligozoospermia, means the concentration of sperm in semen is below the laboratory’s reference range.

A low sperm count may reduce the chances of sperm reaching and fertilising an egg naturally. The severity and underlying cause are important when deciding on treatment.

Read more about low sperm count treatment in Srinagar.

2. Poor Sperm Motility

Sperm motility refers to the ability of sperm to move effectively.

Sperm need to move appropriately to travel through the female reproductive tract and reach the egg. Reduced sperm motility is known as asthenozoospermia and may make natural conception more difficult.

3. Abnormal Sperm Morphology

Sperm morphology describes the size and shape of sperm cells.

Abnormalities can involve the sperm head, midpiece or tail. A semen analysis evaluates sperm morphology along with other semen parameters.

Learn more about sperm morphology.

4. Hormonal Imbalance

Hormones play an important role in sperm production and male reproductive function.

Problems involving hormones produced by the hypothalamus, pituitary gland, thyroid or testes may affect sperm production and fertility. Hormone testing may be recommended when a doctor suspects an endocrine cause.

Read more about the role of hormones in fertility.

5. Varicocele

A varicocele is an enlargement of veins within the scrotum. It is relatively common and can sometimes be associated with impaired sperm production or semen quality.

Because sperm production is sensitive to temperature, changes in blood flow and testicular temperature may affect sperm function in some men.

6. Genetic Conditions

Certain genetic conditions can affect sperm production or the development of the male reproductive system.

Examples include Klinefelter syndrome, Kallmann syndrome, Kartagener syndrome and some genetic forms of cystic fibrosis-related infertility.

Genetic testing may be recommended in selected men, particularly when sperm counts are very low or sperm are absent from the semen.

7. Infections

Some infections, including sexually transmitted infections and infections affecting the reproductive tract, can interfere with sperm production or cause scarring and blockage of the reproductive tract.

Appropriate diagnosis and treatment are important when an infection is suspected.

8. Previous Surgery

Previous surgery involving the testicles, scrotum, prostate, bladder, abdomen or reproductive tract may sometimes affect sperm production, sperm transport or ejaculation.

A detailed medical and surgical history can help identify these factors.

9. Smoking and Alcohol

Lifestyle factors can influence male reproductive health.

Smoking and tobacco exposure may adversely affect sperm quality. Heavy alcohol consumption may also affect reproductive hormones and semen quality.

Men trying to improve their fertility should discuss alcohol, tobacco and other lifestyle factors with their healthcare professional.

10. Testicular Injury or Trauma

Previous injury or trauma to the testicles may affect sperm production or testicular function.

A history of significant testicular injury should be discussed during a fertility evaluation.

11. Retrograde Ejaculation

Normally, semen leaves the body through the penis during ejaculation. In retrograde ejaculation, semen enters the bladder instead.

This can result in little or no semen being ejaculated and may affect the ability to conceive naturally.

12. Testicular Tumours and Other Testicular Conditions

Some testicular tumours and other conditions affecting the testicles can interfere with normal sperm production.

Previous treatment for testicular cancer, including surgery, chemotherapy or radiation, can also affect fertility.

13. Medications, Drugs and Anabolic Steroids

Certain medications and recreational drugs can affect male reproductive function.

Of particular importance are anabolic steroids and testosterone supplementation, which can suppress the body’s natural sperm production.

Men using testosterone or other hormonal medicines should discuss fertility plans with their doctor before making changes to treatment.

14. Obesity and Excess Weight

Maintaining a healthy weight, eating a balanced diet and staying physically active can support overall reproductive health.

15. Excessive Physical or Training Load

Regular physical activity is generally beneficial. However, extreme training, inadequate nutrition and overtraining may affect hormonal balance and reproductive function in some individuals.

16. Chronic Stress and Poor Sleep

Long-term stress and inadequate sleep can affect overall health and may influence hormonal and reproductive function.

Managing stress, maintaining adequate sleep and following a healthy lifestyle can form part of a broader approach to improving fertility.

Male Infertility Symptoms

One of the challenges with male infertility is that many men have no obvious symptoms.

In other cases, symptoms may provide clues to an underlying condition.

Possible signs and symptoms include:

  • Difficulty achieving or maintaining an erection
  • Reduced sexual desire
  • Problems with ejaculation
  • Little or no semen during ejaculation
  • Pain, swelling or a lump in the testicle or scrotum
  • Recurrent genital or urinary infections
  • Reduced facial or body hair
  • Enlarged breast tissue
  • A history of testicular problems or surgery
  • Difficulty conceiving despite regular unprotected intercourse

Experiencing one of these symptoms does not necessarily mean that a man is infertile. A proper medical evaluation is needed to identify the cause.

How Is Male Infertility Diagnosed?

The diagnosis of male infertility usually begins with a detailed medical and reproductive history followed by appropriate tests.

A fertility specialist may ask about:

  • Previous pregnancies
  • Duration of infertility
  • Sexual and ejaculation history
  • Previous surgeries
  • Testicular injuries
  • Medications and supplements
  • Lifestyle factors
  • Previous infections
  • Family history
  • Previous fertility treatments

The results help determine which additional investigations may be appropriate.

Male Infertility Tests

Semen Analysis

Semen analysis is one of the most important initial tests for evaluating male fertility.

It assesses factors such as:

  • Sperm concentration
  • Total sperm number
  • Sperm motility
  • Sperm morphology
  • Semen volume
  • Other semen characteristics

A single semen analysis may not provide the complete picture because semen parameters can vary between samples. Your doctor may therefore recommend repeat testing.

You can also explore infertility tests in Srinagar.

Hormone Testing

Blood tests may be used to evaluate reproductive hormones such as testosterone, FSH and LH, depending on the clinical situation.

Hormonal testing can help identify conditions affecting sperm production.

Scrotal Ultrasound and Doppler

A scrotal ultrasound or Doppler study may help evaluate the testicles, epididymis, blood flow and conditions such as varicocele.

Transrectal Ultrasound

A transrectal ultrasound, or TRUS, may be recommended in selected cases when a doctor suspects a blockage involving the ejaculatory ducts or other structures.

Genetic Testing

Genetic tests may be recommended for certain men with severe sperm-production problems, particularly very low sperm counts or azoospermia.

Testicular Biopsy

In selected cases, a testicular biopsy may help determine whether sperm production is occurring within the testicular tissue.

Can Male Infertility Be Treated?

Yes. Male infertility treatment depends on the underlying cause.

Some men may benefit from lifestyle changes or medicines, while others may require surgery or assisted reproductive techniques such as IVF and ICSI.

Treatment should be based on a proper diagnosis rather than simply treating the semen report.

Male Infertility Treatment Options

Lifestyle Changes

Depending on the cause, a doctor may recommend:

  • Stopping tobacco use
  • Limiting excessive alcohol consumption
  • Maintaining a healthy weight
  • Following a balanced diet
  • Regular moderate physical activity
  • Managing stress
  • Getting adequate sleep
  • Avoiding unnecessary exposure to excessive heat
  • Reviewing medicines that may affect fertility with a doctor

Medicines and Hormonal Treatment

When hormonal abnormalities or specific medical conditions are identified, appropriate medicines may help improve reproductive function.

Hormonal treatment should only be taken under medical supervision.

Varicocele Treatment

When a clinically significant varicocele is associated with infertility, a specialist may consider varicocele repair in selected patients.

Vasovasostomy

A vasovasostomy is a surgical procedure used to reconnect the vas deferens, commonly after a previous vasectomy.

Vasoepididymostomy

A vasoepididymostomy connects the vas deferens to the epididymis and may be considered when there is an obstruction that prevents sperm from entering the semen.

Transurethral Resection of the Ejaculatory Duct

In selected cases involving ejaculatory duct obstruction, a transurethral procedure may be considered to improve sperm passage.

IVF for Male Infertility

In vitro fertilisation (IVF) may be considered when male-factor infertility is significant or when other fertility treatments have not been successful.

During IVF, eggs are retrieved from the ovaries and fertilisation takes place in a laboratory. The resulting embryo can then be transferred into the uterus.

Learn more about IVF treatment in Srinagar.

ICSI for Male Infertility

Intracytoplasmic sperm injection (ICSI) is an advanced fertilisation technique commonly used when sperm-related factors make conventional fertilisation difficult.

During ICSI, a single selected sperm is injected directly into a mature egg in the laboratory.

ICSI may be considered in situations such as:

  • Very low sperm count
  • Poor sperm motility
  • Severe sperm morphology abnormalities
  • Previous fertilisation failure
  • Surgically retrieved sperm
  • Certain cases of severe male-factor infertility

Read more about ICSI treatment in Srinagar.

Sperm Retrieval Procedures for Male Infertility

Some men produce sperm inside the testicles but have little or no sperm in the ejaculated semen. In such cases, sperm retrieval may be considered for use with IVF-ICSI.

Common sperm retrieval procedures include:

TESA

Testicular Sperm Aspiration (TESA) uses a needle to obtain sperm-containing tissue from the testicle.

PESA

Percutaneous Epididymal Sperm Aspiration (PESA) retrieves sperm from the epididymis using a needle.

TESE

Testicular Sperm Extraction (TESE) involves obtaining a small amount of testicular tissue to look for sperm.

Learn more about TESE and its success rate.

MESA

Microsurgical Epididymal Sperm Aspiration (MESA) uses microsurgical techniques to retrieve sperm from the epididymis.

MicroTESE

Microdissection TESE (microTESE) uses an operating microscope to identify areas of the testicle that may contain sperm.

The most appropriate sperm retrieval technique depends on the individual’s diagnosis and whether sperm production is present.

Donor Sperm Treatment

When sperm cannot be obtained or when other treatment options are not appropriate, donor sperm treatment may be considered in accordance with applicable medical and legal requirements.

Your fertility specialist can explain the available options, eligibility requirements and treatment process.

When Should a Man Get a Fertility Test?

A male fertility evaluation may be appropriate when:

  • The couple has been trying to conceive for 12 months without pregnancy
  • There is a known history of low sperm count
  • There is a history of testicular injury or surgery
  • There are ejaculation or erectile problems
  • There is a history of reproductive or urinary infection
  • The man has used testosterone or anabolic steroids
  • There is a known hormonal or genetic condition
  • The female partner’s age or fertility history makes earlier evaluation advisable

Both partners may need evaluation because infertility can involve male factors, female factors, or a combination of both.

Can Male Infertility Be Prevented?

Not every cause of male infertility can be prevented, particularly genetic or congenital conditions. However, maintaining overall health may help protect reproductive health.

Helpful measures may include:

  • Avoiding tobacco and recreational drugs
  • Limiting excessive alcohol consumption
  • Maintaining a healthy body weight
  • Exercising regularly without excessive training
  • Managing chronic medical conditions
  • Avoiding unnecessary testosterone or anabolic steroid use
  • Seeking treatment for reproductive or urinary infections
  • Protecting the testicles from significant injury
  • Discussing fertility preservation before treatments that may affect sperm production

Frequently Asked Questions About Male Infertility

What is the main cause of male infertility?

There is no single cause. Male infertility may result from low sperm count, poor sperm motility, abnormal sperm morphology, hormonal problems, varicocele, genetic conditions, reproductive tract obstruction, infections, medications, lifestyle factors or problems with sperm production.

What are the signs of male infertility?

Many men have no noticeable symptoms. When symptoms occur, they may include ejaculation problems, erectile dysfunction, reduced libido, testicular pain or swelling, or changes in semen volume.

Which test is used for male infertility?

A semen analysis is usually one of the first investigations used to assess male fertility. Additional tests, such as hormone testing, ultrasound, Doppler studies, or genetic testing, may be recommended depending on the findings.

Can low sperm count be treated?

Treatment depends on the cause and severity. Depending on the diagnosis, options may include lifestyle changes, medicines, treatment of an underlying condition, surgery, sperm retrieval or assisted reproductive techniques such as IVF-ICSI.

Can a man with zero sperm count have a baby?

In some cases, yes. Men with azoospermia may still produce sperm in the testicles. Depending on the cause, sperm retrieval techniques such as TESE or microTESE may be considered, often together with ICSI.

Is IVF required for every case of male infertility?

No. Treatment depends on the underlying cause. Some men may improve with lifestyle changes, medicines or surgery. Assisted reproductive techniques may be considered when other approaches are not suitable or have not worked.

Is ICSI better than IVF for male infertility?

IVF and ICSI are different fertilisation approaches. ICSI may be particularly useful when there is significant male-factor infertility or when sperm-related problems make conventional fertilisation difficult. The appropriate technique should be decided based on the couple’s clinical circumstances.

Take the Next Step for Male Infertility

Male infertility can have several possible causes, and a semen report alone does not always explain the complete picture. A proper evaluation can help identify whether the issue involves sperm production, sperm quality, hormones, anatomy, ejaculation or another factor.

If you or your partner are having difficulty conceiving, consider consulting a fertility specialist for an individual assessment. At Imprimis IVF & Fertility Centre, fertility evaluation and treatment options are discussed based on your medical history, test results, and reproductive goals.

Explore male fertility and infertility care or consult a fertility specialist to understand the next appropriate step.

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: September 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: Second Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu and Kashmir – 190014
Phone: 7678556881, 9650777084

IVF Success Rates: Success Chances & Key Factors Explained

With advances in reproductive medicine, in vitro fertilization (IVF) has become an important fertility treatment option for couples experiencing infertility. However, IVF success rates can vary considerably from one person to another.

One of the most important factors associated with IVF outcomes is female age, particularly because egg number and egg quality generally decline with age. However, age is only one part of the picture. Ovarian reserve, sperm quality, embryo development, uterine health, infertility diagnosis, previous treatment history, and the type of IVF treatment can also influence outcomes.

Therefore, if you are researching the IVF success rate by age, it is important to understand what the available statistics actually mean and why your individual chances may be different.

At Imprimis IVF & Fertility Centre, Srinagar, our fertility specialists evaluate each couple individually and develop a treatment plan based on their medical history and fertility assessment.

IVF Success Rate by Age: Why Does Age Matter?

Age is an important factor in IVF because female fertility changes over time. In general, younger women tend to have a higher probability of producing eggs and embryos with reproductive potential.

As age increases, ovarian reserve and egg quality generally decline. In addition, the proportion of embryos with chromosomal abnormalities tends to increase with maternal age.

However, this does not mean that IVF cannot work after 35 or 40. Instead, the expected probability of success may change, and treatment planning may become more individualized.

For example, current ART reporting systems present success rates by age group because age is an important factor in treatment outcomes. However, these population-level figures should not be interpreted as an individual’s personal probability of having a baby.

IVF Success Rates by Age Group

IVF Success Rates by Age Group

When discussing IVF success rates by age, fertility clinics and research studies may use different measures and age categories.

Common age groups include:

  • Under 35
  • 35–37
  • 38–40
  • 41–42
  • Over 42

The exact success rate can also differ depending on whether the calculation is based on:

  • IVF cycle started
  • Egg retrieval
  • Embryo transfer
  • Clinical pregnancy
  • Live birth
  • Cumulative treatment involving multiple embryo transfers

Therefore, two IVF success rates may look different even when they come from reliable sources because they are measuring different outcomes.

IVF Success Rate Under 35

Women under 35 generally have higher IVF success rates with their own eggs compared with older age groups. However, the exact probability depends on factors such as ovarian reserve, embryo quality, sperm quality, infertility diagnosis, and treatment protocol.

For example, CDC national ART data for 2022 reported a higher live-birth rate per intended retrieval among patients under 35 than among older age groups. However, these figures represent a large population and should not be used as an individual prediction.

If you are under 35 and considering IVF treatment in Srinagar, your fertility specialist can assess your ovarian reserve and other factors to provide a more individualized understanding of your treatment prospects.

IVF Success Rate Between 35 and 37

Between 35 and 37, IVF success rates may begin to decline compared with younger age groups.

This change is primarily associated with age-related changes in egg quality. Nevertheless, many women in this age group successfully conceive through IVF.

Your fertility assessment may include ovarian reserve testing, ultrasound evaluation, hormone testing, and assessment of other infertility factors.

IVF Success Rate Between 38 and 40

Between 38 and 40, the effect of age on IVF outcomes becomes more significant.

Egg quantity and quality generally decline with age, and the likelihood of chromosomal abnormalities in embryos increases. Consequently, fewer embryos may have the potential to result in a successful pregnancy.

However, IVF outcomes can still vary considerably between individuals.

IVF Success Rate After 40

After 40, IVF success rates with a woman’s own eggs generally decline more substantially.

The decline is largely associated with changes in egg quality and an increasing proportion of embryos affected by chromosomal abnormalities.

For women over 40, a fertility specialist may discuss options such as IVF using their own eggs, donor egg IVF, embryo testing in appropriate circumstances, or other treatment approaches depending on their individual fertility assessment.

Current ART data also demonstrate substantial differences in outcomes across age groups, reinforcing the need to interpret age-specific statistics carefully rather than using them as a guarantee for an individual patient.

IVF Success Rate by Number and Quality of Embryos


The number and quality of embryos can influence IVF outcomes. However, transferring more embryos does not automatically mean a higher chance of having a healthy baby.

Instead, fertility specialists consider embryo quality, patient age, previous treatment history, embryo testing where appropriate, and the risks associated with multiple pregnancy.

Single Embryo Transfer vs Multiple Embryo Transfer

A single embryo transfer (SET) transfers one embryo into the uterus.

Multiple embryo transfer involves transferring more than one embryo. Although this may increase the chance of implantation in some circumstances, it can also increase the risk of multiple pregnancy.

Multiple pregnancies are associated with higher risks for both the mother and babies. Therefore, many fertility treatment strategies emphasize transferring an appropriate number of embryos rather than simply transferring more embryos.

CDC national ART data for 2022 showed that 85.9% of embryo transfers were single embryo transfers in the United States.

Your fertility specialist can determine the most appropriate embryo-transfer strategy based on your individual circumstances.

Frozen Embryo Transfer Success Rate

Frozen Embryo Transfer (FET) involves transferring a previously frozen embryo into the uterus during a suitable cycle.

FET is now an established part of IVF treatment. However, its success rate cannot be captured by a single universal percentage.

The outcome can depend on:

  • Female age
  • Age when the eggs were coll
  • ected
  • Embryo quality
  • Embryo stage
  • Endometrial preparation
  • Uterine health
  • Whether the embryo was genetically tested
  • Previous treatment history

Therefore, a frozen embryo transfer success rate should always be interpreted in the context of the patient and embryo characteristics.

Why Does IVF Success Rate Decrease With Age?


There are several biological reasons why IVF outcomes may decline with increasing female age.

1. Declining Ovarian Reserve

Ovarian reserve refers broadly to the remaining supply of eggs in the ovaries.

As a woman ages, the number of available eggs generally decreases. However, ovarian reserve tests such as AMH and AFC provide information about egg quantity or expected ovarian response; they do not independently determine whether an individual will achieve a pregnancy through IVF.

Therefore, AMH should be interpreted together with age, ultrasound findings, medical history, and other fertility factors.

2. Changes in Egg Quality

Age is associated with changes in egg quality.

As egg quality declines, the likelihood of chromosomal abnormalities in embryos increases. Consequently, fewer embryos may have the potential to implant and develop into an ongoing pregnancy.

This is one of the major reasons why IVF success rates by age are an important consideration when planning fertility treatment.

3. Embryo Chromosomal Abnormalities

An embryo can have an abnormal number of chromosomes, a condition known as aneuploidy.

The likelihood of aneuploid embryos generally increases with maternal age. An embryo with significant chromosomal abnormalities may fail to implant or may result in miscarriage.

However, embryo appearance under a microscope does not always reveal chromosomal status.

Other Factors That Affect IVF Success Rate

Although age is important, it is not the only factor that affects IVF outcomes.

Ovarian Response and Ovarian Reserve

During IVF, fertility medicines stimulate the ovaries to develop multiple follicles.

Women with diminished ovarian reserve may produce fewer eggs during stimulation. However, ovarian response varies among individuals, and a lower egg yield does not necessarily mean IVF cannot succeed.

Sperm Quality and Male Fertility

Sperm quality can also influence fertilisation and embryo development.

Important sperm parameters include:

  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Sperm DNA integrity in selected cases

Male infertility can therefore play an important role in IVF planning.

Embryo Quality

Embryo quality is another important factor.

Embryologists assess embryos using established laboratory criteria. However, embryo morphology alone cannot guarantee implantation or live birth.

Uterine and Endometrial Factors

The uterus and endometrium also play an important role in embryo implantation.

Conditions affecting the uterine cavity, endometrium, or reproductive anatomy may need evaluation before embryo transfer.

Previous IVF History

Previous IVF cycles can provide useful information for future treatment planning.

For example, previous ovarian response, fertilisation results, embryo development, implantation outcomes, and pregnancy history may help your fertility specialist modify a subsequent treatment plan.

Lifestyle and General Health

Lifestyle and general health can also influence reproductive health.

Maintaining a healthy lifestyle, avoiding smoking, limiting alcohol, maintaining an appropriate weight, and following your doctor’s recommendations may support overall fertility care.

However, lifestyle changes cannot guarantee IVF success.

How Can You Improve Your Chances of IVF Success?

No fertility centre can guarantee a 100% IVF success rate.

However, several steps can help you prepare for treatment and address factors that may affect your outcome.

Choose an Experienced IVF Centre

IVF is a complex form of assisted reproductive technology (ART) involving fertility specialists, embryologists, laboratory procedures, medications, monitoring, and embryo transfer.

Therefore, choose a fertility centre where the medical team can clearly explain your diagnosis, treatment options, expected outcomes, and potential risks.

Follow Your IVF Medication Schedule

IVF medicines are prescribed according to an individualized treatment protocol.

Therefore, take your medicines exactly as prescribed and follow your fertility specialist’s instructions regarding timing and dosage.

If you miss a dose or are unsure about medication instructions, contact your fertility team rather than changing the medication yourself.

Maintain a Healthy Lifestyle

A balanced diet, regular physical activity appropriate for your health, adequate sleep, and avoiding smoking can support overall health during fertility treatment.

In addition, follow any specific dietary or lifestyle recommendations provided by your fertility specialist.

Follow Post-Transfer Instructions

After embryo transfer, follow your fertility team’s instructions regarding medicines, physical activity, and follow-up.

Strict bed rest is generally not required simply because an embryo has been transferred. Instead, follow the specific recommendations provided by your treating doctor.

Manage Expectations and Seek Support

IVF can be emotionally demanding.

Therefore, couples may benefit from appropriate emotional support, counseling, and open communication with their fertility team.

Most importantly, remember that IVF outcomes cannot be guaranteed, even when embryos and treatment parameters appear favorable.

Donor Egg IVF Success Rate

For some women, particularly those with significantly reduced ovarian reserve or age-related decline in egg quality, a fertility specialist may discuss donor egg IVF.

Donor egg treatment uses donor eggs to create embryos for transfer.

Importantly, donor egg IVF outcomes are influenced by factors related to the donor eggs as well as the recipient’s health and treatment circumstances.

Current ART reporting separates donor-egg cycles from cycles using a patient’s own eggs because the outcomes are not directly comparable.

Therefore, women considering donor egg IVF should discuss their individual treatment options and expected outcomes with a fertility specialist.

IVF Success Rate With PGT-A or Preimplantation Genetic Testing

IVF Success Rate With PGT-A or Preimplantation Genetic Testing

Preimplantation Genetic Testing for Aneuploidy (PGT-A) involves testing cells from an embryo to identify certain chromosome-number abnormalities before embryo transfer.

It is important to understand that PGT-A does not guarantee IVF success and is not appropriate for every patient.

Evidence on whether PGT-A improves cumulative live-birth outcomes for all IVF patients is mixed. The American Society for Reproductive Medicine notes that available evidence does not support assuming a universal benefit for every patient.

A fertility specialist may consider factors such as:

  • Female age
  • Embryo availability
  • Previous IVF history
  • Recurrent pregnancy loss
  • Genetic considerations
  • Number and quality of blastocysts
  • Individual treatment goals

Therefore, PGT-A should be considered on an individual basis rather than as a routine way to guarantee higher IVF success.

IVF Success Rate by Age and AMH

Anti-Müllerian Hormone (AMH) is commonly used as one marker of ovarian reserve.

AMH can help fertility specialists estimate how the ovaries may respond to stimulation. However, AMH should not be treated as a direct predictor of whether an individual woman will become pregnant through IVF.

In other words, a low AMH does not automatically mean IVF will fail, while a normal AMH does not guarantee pregnancy.

Age remains an important factor because ovarian reserve and egg quality are related but different concepts.

Therefore, your fertility specialist may consider:

  • Age
  • AMH
  • Antral follicle count
  • Previous ovarian response
  • Menstrual history
  • Other hormone tests
  • Medical history
  • Previous IVF outcomes

Together, these factors provide a more complete picture than AMH alone.

IVF Success Rate by Age: Understanding the Numbers

When researching IVF success rates by age, always check what the percentage actually represents.

For example, a study or clinic may report success:

  • Per IVF cycle
  • Per egg retrieval
  • Per embryo transfer
  • Per clinical pregnancy
  • Per live birth
  • Per patient
  • As a cumulative chance after multiple transfers

These measurements are not interchangeable.

For instance, CDC ART reporting distinguishes between intended retrievals, actual retrievals, transfers, clinical pregnancy, and live-birth outcomes.

Therefore, rather than asking only, “What is the IVF success rate at my age?”, ask your fertility specialist:

  1. Is the percentage based on pregnancy or live birth?
  2. Is it calculated per cycle or per embryo transfer?
  3. Does it include patients using their own eggs?
  4. What is the age group?
  5. Does it include fresh and frozen transfers?
  6. Does it include patients with previous IVF attempts?
  7. How do my individual medical factors affect my expected outcome?

This gives you a much clearer understanding of what the numbers mean.

IVF Success Rate in Srinagar

If you are searching for the IVF success rate in Srinagar, it is important to compare like-for-like information.

Clinic success rates can vary because clinics may treat different patient populations and use different treatment protocols. Therefore, a single percentage should not be used to predict the outcome of an individual couple.

At Imprimis IVF & Fertility Centre, Srinagar, your fertility specialist can review your age, ovarian reserve, sperm parameters, infertility diagnosis, previous treatment history, and other relevant factors before discussing your treatment plan.

Frequently Asked Questions About IVF Success Rate by Age

What is the IVF success rate by age?

IVF success rates generally decline as female age increases, particularly when using the woman’s own eggs. However, the exact rate varies according to the patient population, treatment method, and definition of success.

Is IVF more successful before age 35?

In general, younger age is associated with higher IVF success rates when using a woman’s own eggs. However, age alone cannot predict an individual’s treatment outcome.

What is the IVF success rate after 40?

IVF success rates with a woman’s own eggs generally decline after 40. However, individual outcomes vary considerably, so a fertility assessment is necessary to understand personal treatment prospects.

Does AMH determine IVF success?

No. AMH is primarily a marker of ovarian reserve and can help predict ovarian response to stimulation. It does not independently determine whether IVF will result in pregnancy or live birth.

Does transferring two embryos increase IVF success?

Transferring more than one embryo does not automatically mean a better overall outcome. It can increase the risk of multiple pregnancy. Therefore, the number of embryos to be transferred should be determined based on individual clinical circumstances.

Can IVF guarantee pregnancy?

No. IVF can help many couples achieve pregnancy, but no fertility treatment can guarantee pregnancy or live birth.

Does PGT-A guarantee a successful IVF pregnancy?

No. PGT-A can provide information about chromosome number in tested embryos, but it does not guarantee implantation, pregnancy, or live birth. Its potential benefits should be discussed with a fertility specialist.

Can women over 40 have successful IVF?

Yes. Women over 40 can achieve pregnancy through IVF. However, success rates with their own eggs generally decline with age. Depending on the individual situation, a fertility specialist may discuss additional treatment options, including donor egg IVF.

Conclusion: Understanding IVF Success Rates by Age

Researching IVF success rates by age can help you understand how age may affect fertility treatment. However, online percentages should not be treated as a prediction of your individual outcome.

Age is important, but it is only one part of the IVF success equation. Ovarian reserve, egg quality, sperm quality, embryo development, uterine health, infertility diagnosis, previous treatment history, and the type of IVF procedure can also influence the outcome.

Therefore, if you are considering IVF treatment in Srinagar, speak with a qualified fertility specialist for an individualized assessment.

At Imprimis IVF & Fertility Centre, Srinagar, our fertility team can help you understand your fertility evaluation, treatment options, expected IVF outcomes, and the factors that may influence your chances of success.

Book an IVF consultation in Srinagar to discuss your individual fertility treatment plan.

Medical Reviewer

Imprimis IVF & Fertility Centre Team

Last Updated

September 2026

Clinic Information

Imprimis IVF & Fertility Centre – Srinagar
Second Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu and Kashmir – 190014
Phone: 7678556881, 9650777084