Searching for the best IVF centre near me in India? Imprimis IVF Centre is a trusted name in advanced fertility care, helping couples achieve their dream of parenthood with personalized and result-driven treatments. With state-of-the-art laboratories, experienced fertility specialists, and cutting-edge technology, we ensure high success rates in IVF, ICSI, IUI, and other assisted reproductive techniques.

At Imprimis IVF, we understand that every fertility journey is unique. That’s why we offer customized treatment plans based on individual medical conditions, including male infertility, female infertility, PCOS, low AMH, and unexplained infertility. Our team provides complete guidance from diagnosis to treatment and post-care support, ensuring a smooth and stress-free experience.

If you are looking for an affordable IVF centre near you, Imprimis IVF provides transparent pricing and cost-effective IVF packages without compromising quality. We combine advanced fertility technology with compassionate care to deliver the best outcomes for our patients across India.

Our centres are equipped with modern infrastructure and follow international standards to maximize IVF success rates. Whether you are exploring IVF for the first time or have faced previous failures, our expert team is here to guide you at every step.

Choose Imprimis IVF Centre when searching for a top IVF clinic near me in India and take the first step towards building your family. Book your consultation today and start your journey with one of India’s leading fertility centres.

Hysteroscopy: Purpose, Procedure, Cost & Treatment

Introduction to Hysteroscopy

What is Hysteroscopy?

Hysteroscopy is a procedure in which a hysteroscope (a flexible tube) is inserted through the vagina into the uterus. The hysteroscope has a light and camera at its tip, which allows doctors to see inside the uterus using transvaginal ultrasound or CT scans. The doctor uses this information to make sure there are no abnormalities that could affect fertility or pregnancy.

Indications for Hysteroscopy

The indications for hysteroscopy include abnormal cervical bleeding (menorrhagia), abnormal uterine size (polyhydramnios), fibroids, endometriosis, pelvic inflammatory disease, ectopic pregnancy, and pelvic pain secondary to pelvic inflammatory disease, and fibroids.

1. Endometriosis: to check for endometriosis, which is a condition wherein tissue resembling the uterus lining grows outside of it (also known as ectopic pregnancy), in other parts of your body like your ovaries, fallopian tubes, or elsewhere. It can cause infertility and pain during menstrual periods.

2. Painful Cycles: To assess for uterine fibroids, which are growths in or around the uterus that can cause pain during menses, heavy periods, or pelvic pain (dysmenorrhea). Uterine fibroids are noncancerous tumours that grow inside the uterus and may interfere with normal childbirth if left untreated.

Types of Hysteroscopy?

Types of Hysteroscopy


There are three types of hysteroscopy:

  • Diagnostic Hysteroscopy
    Used to examine the inside of the uterus and identify problems like fibroids, polyps, or abnormal bleeding.
  • Operative Hysteroscopy
    Performed to treat uterine conditions such as removing polyps, fibroids, or scar tissue.
  • Office Hysteroscopy
    A quick, minimally invasive procedure done in a clinic without anaesthesia for basic diagnosis.

Benefits of Hysteroscopy?

Benefits of Hysteroscopy


●       Accurate Diagnosis: Hysteroscopy allows IVF doctors to directly visualize the uterus’s interior and look for any anomalies, like fibroids, polyps, adhesions, or uterine septum. It can help with accurate diagnosis and treatment planning.

●       Minimally Invasive: With hysteroscopy, a minimally invasive procedure, you can leave the hospital the same day and return home. Compared to open surgery, it typically involves less discomfort, scarring, and recovery time.

●       Potential Treatment: In addition to diagnosis, hysteroscopy can treat various conditions. For example, doctors can use specialized instruments to remove fibroids, polyps, or adhesions or to correct a uterine septum. It could improve fertility outcomes for women.

●        Improved Fertility Outcomes: Hysteroscopy can improve fertility outcomes for women by identifying and treating any conditions that could interfere with embryo implantation or pregnancy. For example, removing a uterine septum or correcting an abnormality can increase the chances of a successful pregnancy.

Hysteroscopy Procedure

A hysteroscope, a tiny, lighted tube with a camera, is inserted through the cervix and vagina into the uterus during hysteroscopy, a minimally invasive procedure. The procedure may be performed in a doctor’s office or outpatient surgical centre and typically takes less than an hour to complete. Here is a breakdown of the hysteroscopy procedure:

1. Pre-procedure

Your physician will likely conduct a physical examination before the hysteroscopy and may request additional tests, like an ultrasound or blood work, to assess your condition. Additionally, you might be told to abstain from food and liquids for a certain amount of time before the procedure.

You will be required to change into a gown on the day of the procedure and lie on an exam table with your toes in stirrups. You may be provided with a sedative or anaesthesia to help you feel more at ease and unwind during the procedure.

2. Intra-procedure

Your doctor will perform a hysteroscopy, during which your cervix and vagina will be used to insert the hysteroscope into your uterus. Thanks to the camera on the hysteroscope, your doctor can see the interior of your uterus and spot any anomalies, like fibroids, polyps, or adhesions.

Depending on the procedure’s intended purpose, the physician may also use specialized tools to eliminate or treat any discrepancies found during the hysteroscopy. Since the procedure is outpatient, you can usually leave for home the same day.

3. Post-procedure

After the hysteroscopy, you will be watched in a recovery area until the anaesthesia wears off. After the procedure, you might experience brief mild cramping, spotting, or discharge.

Your doctor will likely give you detailed post-procedure care instructions, which may include refraining from sexual activity, using tampons, and engaging in strenuous workouts for a few days after the surgery. To ensure a quick recovery, you should also abide by any additional detailed instructions your IVF doctor may have given you.

Most women can undergo the procedure safely and effectively with proper pre-procedure preparation, intra-procedure monitoring, and post-procedure care.

 Conditions Treated with Hysteroscopy
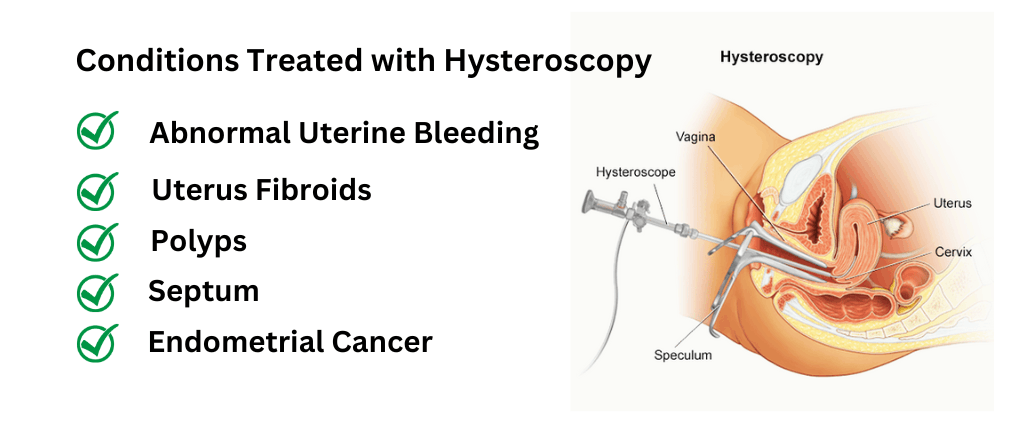
Conditions Treated with Hysteroscopy

1. Abnormal Uterine Bleeding

Abnormal uterine bleeding refers to bleeding that is not part of a woman’s normal menstrual cycle. Numerous things, such as hormonal imbalances, fibroids, polyps, or cancer, can contribute to its development. The underlying cause of abnormal uterine bleeding can be determined and treated using hysteroscopy.

2. Uterus Fibroids

Noncancerous growths called uterine fibroids form in the uterus. They may result in symptoms such as pelvic pain, heavy or protracted menstrual bleeding, and others. The removal of tiny uterine fibroids can be accomplished through hysteroscopy.

3. Polyps

Growths that appear in the uterine lining are known as uterine polyps. They may result in abnormal uterine bleeding, pelvic pain, and other symptoms. Polyps in the uterus can be removed using hysteroscopy.

4. Adhesions

Asherman’s syndrome and uterine adhesions are scar tissue inside the uterus. Previous surgeries, infections, or other factors can cause them. Adhesions can cause infertility, recurrent miscarriages, and other problems. Hysteroscopy can be used to remove adhesions and restore normal uterine function.

5. Septum

A uterine septum is a wall of tissue that divides the uterus into two separate cavities. It can cause infertility, recurrent miscarriages, and other problems. Hysteroscopy can be used to remove the septum and restore normal uterine function.

6. Endometrial Cancer

One type of cancer that appears in the uterine lining is endometrial cancer. Endometrial tissue can be examined using hysteroscopy to detect endometrial cancer. If cancer is detected, hysteroscopy can remove the cancerous tissue.

7. Infertility Investigations

Hysteroscopy can be part of an infertility investigation to identify any structural abnormalities in the uterus contributing to infertility. For example, hysteroscopy can identify and remove polyps or fibroids that may prevent a fertilized egg from implanting in the uterus.

Hysteroscopy Cost

The cost of a hysteroscopy procedure can vary depending on several factors, the place, the kind of facility, and the length of the procedure, for example. However, the cost of hysteroscopy in Srinagar is around 25 000 – 30 000 INR. It includes the cumulative costs of pre-procedure, inter-procedure, and post-procedure expenses. Generally, the hysteroscopy procedure, where only diagnosis is involved, is much cheaper than the procedure where a surgical procedure is followed. 

Post-Treatment Care and Recovery

After a hysteroscopy, you may experience mild cramping, spotting, or discharge. For a few days following the procedure, your doctor might advise against using tampons, engaging in strenuous physical activity, or having sexual relations. To ensure a quick recovery, you should also abide by any additional detailed instructions your doctor may have given you.

Risks and Complications

There are some risks, as there are with any medical procedure. These may include:

  • Infection
  • Heavy bleeding
  • Perforation of the uterus
  • Reaction to anaesthesia
  • Fluid overload

It is essential to comprehend the procedure’s risks and advantages, as with any medical procedure, and any queries or worries should be brought up with your doctor before the procedure. Reviewing these risks with your physician before starting the procedure and getting help if you develop any strange symptoms later on is crucial.

Conclusion

Hysteroscopy is a safe and effective procedure used to diagnose and treat various conditions of the uterus. Most women can recover quickly and resume normal activities with proper post-treatment care and monitoring. The risks and benefits of the procedure should be understood, as with any medical procedure, and any queries or worries should be brought up with your doctor before the procedure. Hysteroscopy is a flexible procedure that can be used to identify and manage several uterine conditions. If you have any signs of abnormal uterine bleeding, fibroids, polyps, or infertility, speak with your doctor.

Why Imprimis IVF for Hysteroscopy?

Imprimis IVF is a fertility clinic that provides advanced methods and technological advances to improve the chances of a healthy pregnancy. According to Imprimis IVF, hysteroscopy is a diagnostic and therapeutic tool offered to women struggling with infertility or other reproductive issues. It is used to look inside the uterus and find any issues that might prevent embryo implantation and potentially treat them. In vitro fertilization (IVF) and additional reproductive techniques are more successful thanks to Imprimis IVF’s cutting-edge techniques and technology. Imprimis IVF aims to provide a comprehensive approach to fertility treatment and raise their patients’ chances of having a healthy pregnancy.
What is Fertile Window and the Right Time for Sex

What is fertile window – A fertile window is when couples can expect to conceive a child, which happens between days 8 and 12 of a woman’s menstrual cycle. This window is critical because it affects how many days in your cycle your partner can fall within to maximize his chances of conceiving. If he doesn’t fall within this window, he could be infertile.

Menstrual Cycle and Ovulation

A. Overview of the Menstrual Cycle and Hormone Regulation

Hormones cause the menstrual cycle. The body produces hormones as chemicals to regulate various bodily processes. They help control growth, metabolism, and other processes. The levels of these hormones fluctuate, which results in the menstrual cycle.

The initial day of your period (menstruation) marks the start of your menstrual cycle, which ends on the last day (the beginning of your subsequent period). It takes about 28 days for a complete cycle. During this time, you have bleeding (menstruation) caused by an ovum (egg) leaving your ovary on its own or being released by your body due to hormonal stimulation.

The menstrual cycle is the series of hormonal changes in a woman’s body each month. 

The Cycle of Menstruation is made up of Three Phases, Namely:
  1. Proliferative phase (days 1-14). In this phase, the lining of the uterus grows, and blood flow increases to sustain this growth.
  2. Cortical phase (days 15-28). This is the primary phase of menstruation when blood clots are shed from the inner lining of the uterus.
  3.  Menses (days 29-35). When this phase is over, menstruation has ended, and ovulation has occurred.

B. Understanding Ovulation and its duration

Ovulation occurs in females and males at different times of the month, depending on their specific hormonal profiles. In women, ovulation happens approximately 14 days before menstruation begins (the first day of bleeding). In men, it happens 12 hours before ejaculation (the point at which sperm are released from the body).

How much time does it take sperm to get to an egg?

This varies between women; however, most experts estimate that it takes 5-6 days for sperm to reach a mature egg.

Determining the Fertile Window

The time when a woman is most likely to get pregnant is known as the fertile window. It is a period that can vary from woman to woman, but some common factors influence the length of this window.

A. Factors Influencing the Length of the Fertile Window

  1. Age: As women age, it becomes more difficult for them to become pregnant due to their declining hormone levels and decreased egg supply
  2. Day of Ovulation: This can be difficult to determine since each woman is different and has her unique cycle. Some women have irregular cycles, while others have regular cycles. A woman should regularly track her basal body temperature (BBT) throughout her cycle to determine when she ovulates based on the rise in temperature following ovulation.
  3. Menstrual Cycle Length: A longer menstrual cycle means that it takes longer for a woman’s hormones to return to normal after she has menstruated. This makes it more challenging for her to conceive because she may not ovulate again until several days after her last period.
  4. Fertility Awareness Method: This method allows women who do not have regular cycles to track their fertility by observing changes in their cervical mucus or other signs that indicate ovulation

B. Methods to Track and Predict Ovulation

You can use various techniques to monitor and predict ovulation to help you decide when it is appropriate to have sex with your partner. These methods include basal body temperature charting and ovulation predictor kits (OPKs).

Basal body temperature charting requires women to monitor their basal body temperatures daily throughout their cycle. A high basal temperature usually indicates ovulation, while a low reading indicates that egg release has occurred and sperm cannot fertilize an egg. Ovulation predictor kits work similarly, giving women an accurate reading daily at home by placing a small strip under their tongue for three days before they start menstruating again. 

Sperm Survival and Timing Intercourse

A. Lifespan of Sperm and Factors Affecting Survival

Sperm cells live for about five days in the female reproductive tract (i.e., ovaries, the fallopian tubes, and the uterus). According to a 1995 study by A.J. Wilcox, the best days for sexual activity on a regular 28-day cycle are days 10, 12, and 16. The intercourse ought to take place on days -4, -2, 0, and +2 based on the anticipated ovulation if the cycle is not a cycle lasting 28 days. The time needed for sperm to decay with the increasing post-ejaculatory abstinence period. 

B. Optimal Timing of Intercourse Concerning Ovulation

In humans, human chorionic gonadotropin (hCG) peaks on days 10-12 post-ovulation. It reaches its peak concentration around the 10th and 11th weeks of pregnancy. Then, from the 12th week of gestation onward, this level falls and remains basal until the end of the pregnancy. This decline in hCG levels is thought to represent an optimal period for intercourse based on controlled studies showing that fertile couples have higher conception rates than infertile couples when they engage in intercourse during this window.

Lifestyle Factors Affecting Fertility

A. Impact of Nutrition, Exercise, and Stress on Fertility

  • Fertility is impacted by the amount of food we eat. Consuming a lot of antioxidants- and vitamin-rich fruits and vegetables can help improve women’s fertility. It also helps keep the body well-nourished, producing more eggs than usual.
  • Exercise also helps with fertility by keeping your blood flowing and helping your body produce more eggs than usual. Additionally, it enhances your quality of sleep, which could prevent you from ovulating too early in the cycle, preventing a pregnancy from happening.
  • Stress may negatively impact fertility by affecting hormone levels in both men and women. Stress can harm the hormones that regulate ovulation and menstruation – leading to irregular periods or missed periods.
There are numerous other ways stress can affect the capacity to get pregnant:

Lack of Sleep: Lack of sleep can lead to lower levels of hormones in the body, which makes it harder for an egg to mature and for an embryo to develop properly. Additionally, it makes it easier to sleep at night, which might stop you from ovulating early enough in the cycle and preventing a pregnancy.

Poor Diet: Poor diet has been associated with decreased libido, which may make it difficult for men trying to conceive to get aroused enough during sex sessions (so they don’t ejaculate before they would like). 

Medical Interventions and Assistance

A. When to Seek Medical Advice for Fertility Concerns

If you have difficulty conceiving a baby, you should always talk to your doctor. You can get the best guidance and therapeutic options for infertility problems from a fertility specialist. You may also want to consult an obstetrician or gynaecologist, who can perform prenatal care and help deliver your baby.

You should speak with your doctor immediately if you have any worries about your fertility. If left untreated, these conditions can severely affect a woman’s health.

B. Overview of Fertility Tests and Assisted Reproductive Technologies (ARTs)

Fertility tests and ARTs are used together to help you get pregnant. Fertility tests can assess a woman’s reaction to fertility medications, detect issues with the tubes that carry sperm from the testicles to the egg or help diagnose an issue with the ovary or uterus. ARTs are procedures that either increase or restore fertility.

Conclusion

A. Recap of the importance of the fertile window

The fertile window is the period from ovulation to menstruation. During ovulation, a female’s ovary releases an egg into the fallopian tube, where it is carried by sperm to be fertilized. Once inside the uterus, the fertilized egg attaches and develops into a baby.

B. Final tips for optimizing chances of conception

The most important thing you can do to increase your chances of getting pregnant is to get your fertile window periods (also known as your fertile window) regularly each month. If you try to get pregnant right away after missing your fertile window, there’s a good chance that to conceive; you’ll have to wait until your next cycle, which could be months later! This is because sperm live in semen for about five days, so if you miss one or more days in your cycle, chances are your body won’t release many eggs, and you’ll miss out on that fertile window again.

Why Imprimis IVF for ARTs and Fertility Consultations?

A fertility test is a medical procedure that helps determine the health of the female reproductive system. The most common type of fertility test is a blood test to evaluate the level of hormones, such as estrogen and progesterone, in your body. Other tests look at other factors that affect fertility, such as ovulation and the development of eggs.

A variety of assisted reproductive technologies (ARTs) also exist to help couples have children who are genetically related to them. 

Imprimis IVF is a leading fertility clinic known for its innovative approach to ARTs and fertility consultations. They prioritize personalized treatment plans, holistic care, and achieving high success rates. Their patient-centric philosophy creates a supportive and compassionate environment, while their commitment to research and advancements ensures access to the latest techniques. Imprimis IVF is a trusted choice for individuals and couples seeking advanced fertility solutions.

Enlarged Uterus: Causes, Symptoms, and Treatment

Introduction to Enlarged Uterus

Enlarged Uterus – The uterus is a hollow organ in the pelvis and comprises two parts: the endometrium, which thickens during pregnancy, and the myometrium, which supports the uterus internally. Three layers comprise the uterus: the innermost layer is called the glandular or functional layer; this portion of the uterine wall secretes mucus and blood vessels that feed the endometrium.

The middle layer is called the serous or storage layer; this portion of the uterine wall stores blood in case of anemia. Finally, there is an outermost layer called muscular or adventitial; this portion of the uterine wall helps support and shape the uterus. A woman’s reproductive organs comprise her cervix, vagina, fallopian tubes, and ovaries (the ovary).

The term “enlarged uterus” describes a condition in which the size of the endometrium (uterine lining) increases beyond normal limits. The syndrome may start after menopause or present at birth and last for the rest of one’s life. Significant uterus syndrome is sometimes called leiomyomata.

The most common cause of significant uterus syndrome is an inherited disorder called uterine leiomyoma (unlike fibroids, leiomyomas are not cancerous). Leiomyomas are usually benign tumors composed of smooth muscle cells which frequently line the uterus’ interior. They can grow and increase over time, resulting in a larger uterus with an enlarged endometrium.

The most common cause of infertility is an enlarged uterus (endometriosis). An enlarged uterus can occur due to pelvic inflammatory disease (PID), endometriosis, or adenomyosis (a condition in which endometrial tissue grows outside of the uterus). 

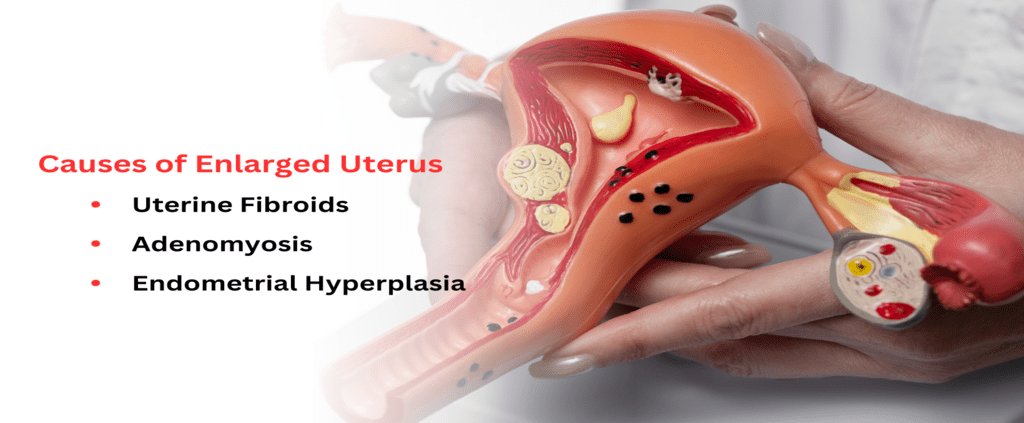
Causes of Enlarged Uterus

Causes of Enlarged Uterus

The common causes of an enlarged uterus may be medical illnesses in the background, like polycystic ovarian syndrome (PCOS), endometriosis, or pelvic inflammatory disease (PID). However, other factors, such as excessive weight gain or breastfeeding, can play a role occasionally.

1. Uterine Fibroids

Fibroids are benign tumors that usually occur in the uterus, although they can sometimes be found elsewhere in the body. The fibroid may be a single tumor, or it may consist of several smaller tumors. Fibroids can cause pain at the time of menstruation, as well as abnormal bleeding and other problems. If a woman thinks she has fibroids, she should see her doctor to get checked out.

2. Adenomyosis

Adenomyosis is when the muscle layer around your uterus becomes thick and lumpy instead of smooth and elastic like normal muscle tissue. This can cause problems with your periods and make them irregular or heavy, possibly leading to anemia or blood clots that may cause a stroke or a heart attack.

If you have adenomyosis, you may also experience painful cramps or bleeding between periods or irregular intervals during your cycle. Your doctor will check for adenomyosis based on the symptoms you report, your medical History, and any physical exam findings he observes during an exam of your cervix (the lower part of your uterus).

3. Endometrial Hyperplasia

Endometrial hyperplasia can develop if a woman has multiple risk factors for endometrial cancer, such as:

  1. Women after 35 years of age.
  2. Previous History of breast cancer
  3. History of blood clots in your veins (deep-vein thrombosis)
  4. Family history of endometrial cancer
  5. A family history of uterine polyps

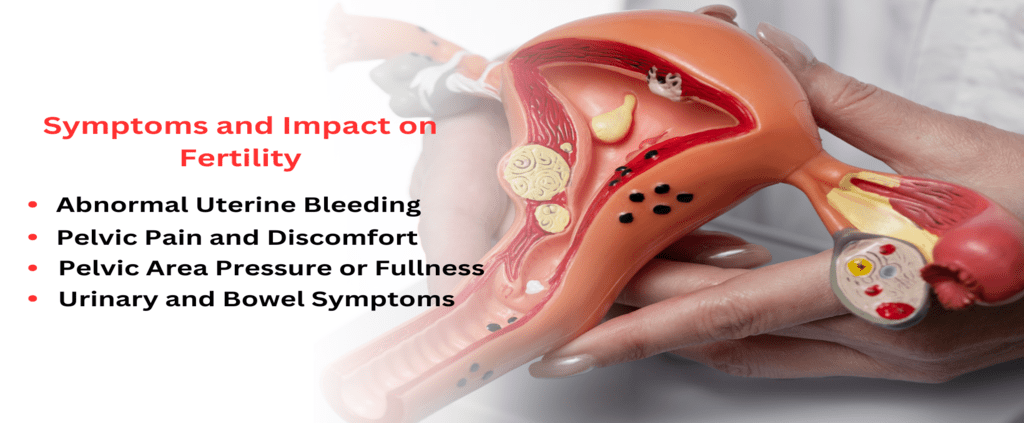
Symptoms and Impact on Fertility

Symptoms of Enlarged Uterus

1. Abnormal Uterine Bleeding

Abnormal uterine bleeding can be a sign of an enlarged uterus. This is also known as menorrhagia. It occurs because the blood flow to the uterus is restricted due to an enlarged uterus. In most cases, it happens due to pregnancy and childbirth. An enlarged uterus may be to blame for lower back or abdomen pain and bleeding between periods.

2. Pelvic Pain and Discomfort

If your uterus has grown too large for its good, it may press against other organs in your pelvis (it comprises two bones: ilium and pubic bone). This pressure can cause pelvic pain, back pain, and lower abdominal discomfort. Another symptom is constipation due to pressure on the rectum from the enlarged uterus pressing against it during childbirth or periods (for example, during menopause).

3. Pelvic Area Pressure or Fullness

Pelvic pain and discomfort are common complaints of women with enlarged uteri. This can be due to pressure or fullness in the pelvis and may also result in spasms or cramping that can be uncomfortable for both you and your doctor to deal with. 

4. Urinary and Bowel Symptoms

Urinary and bowel symptoms such as urgency, frequency, incontinence (leakage) of urine or stool, constipation, painful urination; sexual dysfunction including vaginal dryness or pain during intercourse

Diagnosing an Enlarged Uterus

1. Medical History and Examination

The medical history and physical examination should focus on ruling out pregnancy, fibroids, and cancer. Medical History includes:

  • History of recent illnesses, injuries, or surgeries that may have affected the uterus.
  • Any current or past health conditions may affect fertility or pregnancy, such as diabetes and high blood pressure.
  • The woman’s age, race, and medical History should be considered when diagnosing a possible enlarged uterus since the condition is more common in older women than in young women.

2. Imaging Tests

The diagnosis is usually benign if an ultrasound shows an enlarged uterus with a thin wall. However, if there is no evidence of pregnancy (e.g., vaginal bleeding or missed period), the diagnosis may be more likely to be uterine fibroids or endometriosis. In this case, a laparoscopy may be performed to confirm the diagnosis and remove any fibroids if they are found during surgery. An MRI may also help assess the embryo’s viability so that it can be frozen for future use if needed.

3. Biopsy or Sampling

A biopsy sample can be obtained with laparoscopy; however, there are risks involved in obtaining this type of tissue (invasive surgery).

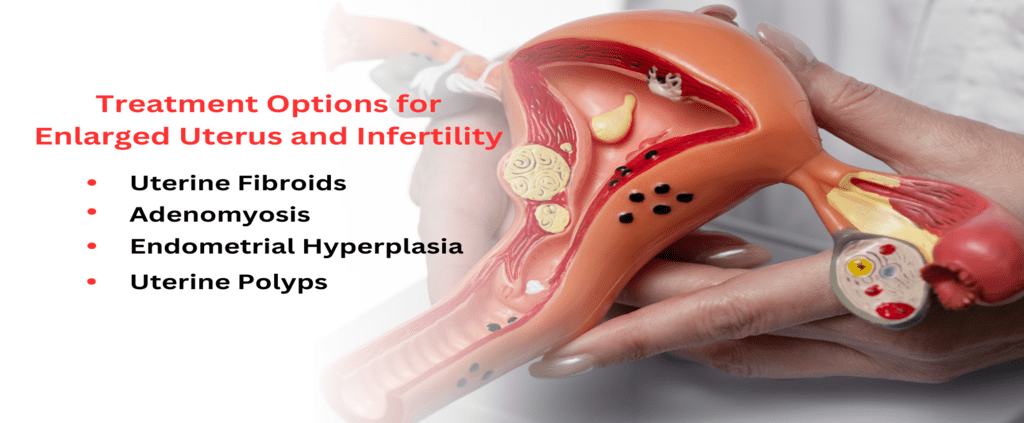
Treatment Options for Enlarged Uterus and Infertility

Treatment of Enlarged Uterus

1. Uterine Fibroids

Uterine fibroids are benign tumors that grow in the fibrous lining of the uterus. Numerous symptoms, such as painful or irregular periods, heavy menstrual flow, pain during sex, or bowel motions, might be brought on by them. If fibroids push on the Fallopian tubes and prevent them from carrying eggs from the ovary to the uterus, this can also result in infertility.

2. Adenomyosis

Adenomyosis is when the lining of the uterus becomes thicker than usual and grows into adjacent tissues. The condition may cause infertility, abdominal pain, and urinary symptoms such as an increased need to urinate and blood in the urine.

3. Endometrial Hyperplasia

Endometrial hyperplasia is a disorder when the lining of the uterus experiences an increase in cells, thickening and expanding abnormally. Women with endometrial hyperplasia may have irregular periods or heavy bleeding. 

4. Uterine Polyps

Uterine polyps are growths on the villi or fingerlike projections that line the end of the fallopian tubes — structures that carry eggs from ovaries to the uterus — or other body areas such as the cervix (neck of the womb). Polyps can cause cervical cancer if they become large enough to block the cervical opening (birth canal).

Fertility Treatment Planning and Considerations

An enlarged uterus is a common medical condition, which is more common in women of childbearing age. The uterus is the organ that holds and nourishes the developing fetus during pregnancy.

Although the exact etiology of this ailment is unknown, it could be brought on by hormone imbalances, pregnancy, tumors, growth hormones, or other factors. It usually affects women after the age of 35 and is more common in those with children.

1. Individualized Approach

For mild cases, there are no special considerations for fertility treatment. However, IVF Treatment may be considered if there is no chance of conceiving naturally. If there is a possibility of having problems conceiving later on, egg donation may be an option.

2. Collaboration with Fertility Specialists

In the case of a large size of uterus, Fertility specialists recommend surgical treatment for the removal of extra tissue or organ from the body or removing part of an organ from the body with minimized damage to surrounding tissues. The procedure has been successfully performed using laparoscopy(minimally invasive surgical technique), which provides several advantages like minimized pain during surgery, no open abdomen surgery required, and less risk of infection compared to open abdomen surgery like laparotomy.

Conclusion

It would be best to see a doctor to find the underlying cause of your enlarged uterus. Making an appointment with your gynecologist is an intelligent approach to accomplish this. Calling their office and making an appointment over the phone is an option if you cannot visit them in person.

A regular doctor will check your health history and ask questions about your menstrual cycle, fertility, family history, and other relevant information. They will also conduct a physical exam and ask you questions about your health. This way, they can look at all possible causes of your enlarged uterus and find suitable treatment options.

Why Choose Imprimis IVF for Enlarged Uterus Treatment

Imprimis IVF is ideal for enlarged uterus treatment due to its specialized expertise, advanced technology, comprehensive approach, diverse treatment options, and supportive care. Their team of experienced fertility specialists focuses exclusively on reproductive medicine, ensuring personalized and effective treatment for an enlarged uterus. Equipped with state-of-the-art facilities, Imprimis IVF provides accurate diagnosis and utilizes cutting-edge technology for optimal treatment outcomes. 

Their holistic approach considers various factors contributing to the condition, addressing underlying causes and developing individualized treatment plans. Imprimis IVF ensures that patients receive the most appropriate and effective care with a wide range of treatment options available, including medications, minimally invasive procedures, and fertility preservation techniques.

What is AMH Test – Purpose, Levels, and Treatment

What is AMH Test – AMH is a female hormone produced by the ovaries. An anti-mullerian hormone is so named because it binds to receptors on cells that line the inside of the fallopian tubes. These receptors are part of a complex system that assists sperm in approaching and fertilizing an egg.

Your doctor may additionally order an AMH test to identify an ovarian mass. An AMH test is a simple blood test; if you take it after your period begins and before ovulation (the release of an egg from one ovary), you may see results in one week or less. An AMH test determines anti-mullerian hormone levels related to an individual’s egg count. It is related to your egg count but does not predict your fertility.

Importance of AMH Levels

AMH levels are essential for determining your ovarian reserve but don’t directly correlate with age. AMH levels increase as you age. After menopause, a woman’s AMH level increases as she ages. The higher the AMH level, the more eggs and ovarian reserve.

AMH levels also vary between women.

Some women have more eggs than others, which means they can produce more eggs in their ovaries. It is called having a high ovarian reserve. Others may have fewer eggs or a lower ovarian reserve, which means they may not be able to produce as many eggs in their ovaries and could experience infertility issues if they decide to get pregnant.

Purpose of the AMH Test

AMH is a hormone that’s produced by the ovaries. It helps maintain an egg’s structure and signals the brain to release hormones that make it possible for a woman to conceive.

The test aims to determine whether or not you are at risk for developing cervical cancer. A positive result means that you might have an increased risk of developing cervical cancer and should undergo regular screening tests for this disease.

The AMH test also helps in assessing ovarian reserve. Suppose you have low or no measurable levels of AMH. In this particular situation, you might be at risk for diminished ovarian reserve or premature menopause — two conditions affecting your fertility options and quality Of life.

Predicting Response to Fertility Treatments:

 The test is commonly performed on postmenopausal women to check for signs of estrogen deficiency or osteoporosis, but it can also be used to assess ovarian reserve and fertility status. In some cases, women may request an AMH test if they have irregular periods or have had their uterus removed due to cancer treatment.

AMH Levels

A higher number means more eggs in your ovaries, which means more egg follicles to help produce healthy eggs. A lower number means you may produce fewer eggs than before and may soon lose those eggs.

A woman’s AMH levels are usually between 1.0 ng/mL to 3.0 ng/mL. (nanograms per millilitre). It is the level at which ovulation is most likely to occur, usually within this range.

Low AMH levels, under 1.0 ng/mL, may indicate that the pituitary gland functions normally. The presence of abnormally low levels of certain hormones in the body might suggest an underlying problem within the hypothalamus or the anterior pituitary gland, which plays a crucial role in hormone production and regulation.

Causes of low AMH:

Ovarian cancer or other conditions that affect the ovaries (liver disease, kidney disease, thyroid problems) may cause low levels of AMH. It can also signify early menopause in women who have not gone through menopause. Your doctor can request an AMH test to confirm the diagnosis if she suspects you are going through perimenopause or early menopause. However, this is not a common indication for testing at this time because most women do not go through menopause until after age 50.

Implications for Fertility:

Because low levels of AMH are associated with advanced reproductive age, they may indicate a woman has less menstrual bleeding and will have fewer eggs than younger women. Conception challenges may additionally be experienced by these women, making it harder for them to achieve pregnancy. In addition, some doctors recommend that women with low levels of AMH get fertility treatment if they have trouble conceiving or carrying a pregnancy past six months. 

High AMH levels can be caused by several factors, including:

High AMH Levels Factors

Hormone Imbalance:

If you’re not getting enough progesterone or estrogen, your body will produce more AMH to compensate for the lack of hormones. It may be caused by a condition like Polycystic ovary syndrome (PCOS) and hypothyroidism (an underactive thyroid gland), which can also contribute to these symptoms in women.

Ageing: 

Our bodies naturally produce less AMH and more follicle-stimulating hormone (FSH) as we age. It can lead to higher estrogen levels and lower progesterone levels, which can cause high AMH levels.

Genetic:

If you have a family history of high blood pressure, heart disease, or type 2 diabetes, you could also inherit high levels of AMH from your parents — conditions often linked to high blood pressure or heart diseases risk factors like smoking and obesity.”

Interpretation of AMH Test Results

Some of the considerations that are to be kept in mind while interpreting the AMH Test results are:

Age-related Considerations

A woman’s age does not influence the results of the AMH test. As early as the age of 20, individuals can undergo this test and receive accurate results as late as 44, with most women having a typical result between ages 25 and 35. The AMH level for a woman between 20–25 years old is 4.23 ng/mL.

Relationship to Fertility Potential

The AMH test has been used to predict fertility potential in older women who wish to conceive. A woman’s AMH level is believed to decline with age, which may be related to decreased production of eggs or sperm, decreased ovulation rate, or both.

Other Factors Affecting Interpretation

Women who have undergone cancer treatment or had multiple pregnancies may have slightly lower levels of AMH than those without these conditions. However, these factors do not affect the interpretation of the result and should be considered if they are high enough to cause concern about fertility potential.

Treatment Options

High AMH Levels Treatment

 There are various treatment options available based on different AMH levels.

  • Treatment for Low AMH Levels

In the case of low levels of AMH, various treatment options are available to women with diminished ovarian reserve. Some of these treatments include:

  • Assisted Reproductive Techniques (ART)

ART treatment is designed to help a woman who cannot become pregnant on her own through natural means become pregnant by using assisted reproductive technology such as in vitro fertilization (IVF) or intracytoplasmic sperm injection (ICSI). Assisted reproductive techniques can help a woman conceive if her eggs are not viable enough for IVF or ICSI. For women with low amounts of AMH and a compromised ability to make eggs, this may occasionally also be a possibility.

  • Ovarian Stimulation

This treatment uses hormones to stimulate the release of one or more eggs from your ovaries during a menstrual cycle. The amount of stimulation depends on the woman’s age and her response to previous stimulation treatments, which can vary widely from woman to woman. Because this method involves injecting hormones directly into your bloodstream, there is always a risk that you might develop side effects such as nausea, vomiting, or headaches while receiving medications through your IV line.

  • Egg or Embryo Freezing

In some cases, women may have low levels of AMH due to low levels of progesterone production caused by premature ovarian failure or menopause. Conditions that may require medical treatment before freezing embryos can occur.

Treatment for High AMH Levels

  • Management of Polycystic Ovary Syndrome (PCOS)

Among the many treatment options for women with high AMH levels, ovary-intact women with PCOS often benefit from medication. PCOS are at increased risk of developing endometrial cancer and should be monitored regularly. In addition, ovarian stimulation is an option for women undergoing IVF or other fertility treatments.

  • Treatment for Ovarian Hyperstimulation Syndrome (OHSS)

Ovarian hyperstimulation syndrome (OHSS) can occur when a woman ovulates multiple times more than usual during ovulation induction. This syndrome can be life-threatening if left untreated, so doctors may recommend that patients take medications to reduce the high levels of AMH in their bodies.

At any point in your menstrual cycle, you have the flexibility to undergo the AMH test. A straightforward blood test that provides valuable insights into your reproductive health. It means you or a health care provider can perform it.

In addition to being an excellent diagnostic tool, the AMH test has many other benefits. It can:

  1.  Identify if your ovaries are making too much estrogen. This imbalance of sex hormones can ensue, causing a disruption in their normal levels and functions within the body.
  2.  Identify if there are any issues with egg development or fertilization;
  3.  Evaluate treatment options for PCOS, OHSS, or other conditions related to abnormal ovulation.

Why Choose Imprimis IVF for AMH Testing?

What is AMH Test

 Imprimis IVF may be a suitable choice for your AMH test due to the following reasons:

 Specialization: Imprimis IVF specializes in reproductive medicine and fertility treatments, ensuring expertise in conducting AMH tests.

  1. Advanced Facilities: They have state-of-the-art laboratory facilities and advanced diagnostic technology for accurate and reliable testing.
  2. Comprehensive Services: Imprimis IVF offers a range of fertility treatments beyond AMH testing, providing integrated care.
  3. Positive Reputation: The clinic has a strong reputation for delivering high-quality care and achieving successful outcomes.
  4. Patient-centered Approach: Imprimis IVF focuses on compassionate and personalized care throughout your fertility journey.
  5. Affordability: They offer cost-effective options and may partner with insurance providers to help manage expenses.

Conclusion

It’s essential to take note of both your age and your AMH levels when trying to conceive. You can use an AMH blood test for the same reasons as the anti-mullerian hormone (AMH) test. It’s a few days long but a relatively quick and easy procedure. If you’re concerned about your fertility and want to do everything possible, including affordable testing. Check with your fertility clinic or IVF experts to learn more about an AMH blood test.

Blocked Fallopian Tubes: Causes, Symptoms, and Treatment

Blocked fallopian tubes are one of the reasons for female infertility. Its medical name is Tubal occlusion. Although several risk factors can increase your chances of getting the disease, there are usually no symptoms.

The fallopian tubes are muscular tubes with a fine hair-like structure inside. These “hairs” help in both directions: They help the sperm to travel up into the uterus. Fimbriae, which look like fingers, adjoin each fallopian tube. When the ovary releases an egg, the fimbria captures and guides it.

Since most eggs are fertilized in the fallopian tubes, they are essential for fertilization. If any injured part is there, for example, by surgery or infection, scar tissue may form.

Describe Hydrosalpinx.

The Greek originates the hydrosalpinx, which means water and tube. A woman’s fallopian tubes are blocked by hydrosalpinx, which is caused by fluid buildup and enlargement at the end of the tube. The end of the tube fibroid closest to the ovary is where it usually occurs, although it can also occur at the end of the tube that connects to the uterus.

One type of infertility caused by tubal factors is blocked fallopian tubes. Fallopian tube cells secrete fluid when blocked, causing the tubes to widen. Preventing an ovulated egg from being fertilized by sperm from the ovary to the fallopian tube prevents fertilization and thus prevents pregnancy. Most likely, hydrosalpinx prevents a fertilized egg from travelling to the uterus for implantation and pregnancy, even if an ovulated egg has come into contact with sperm.

Additionally, it can lead to a dangerous ectopic pregnancy, in which the embryo implants in the fallopian tubes and becomes seriously fatal. Bilateral hydrosalpinx is the condition of having hydrosalpinx in both fallopian tubes simultaneously.

Hydrosalpinx is detrimental to fertility treatments. According to a study, the success rate of assisted reproductive technologies, such as IVF, is reduced by 50% in women with hydrosalpinx fluid compared to women without it. So doctors recommend that patients who use IVF have the hydrosalpinx surgically removed before starting treatment.

If a woman becomes pregnant (naturally or through fertility therapy), the presence of hydrosalpinx impacts the pregnancy outcome. Scientists don’t fully understand why this happens. Still, they believe that hydrosalpinx poisons the egg and embryo and damages the endometrium in such a way as to disgorge the implantation and development of the developing embryo.

Symptoms of Blocked Fallopian Tubes :

Symptoms of Blocked Fallopian Tubes

Unlike anovulation, which can be indicated by irregular periods, blocked fallopian tubes rarely cause symptoms. The first symptom of blocked fallopian tubes is infertility. In addition to regular fertility tests, if you haven’t gotten pregnant after a year of trying, your doctor may order a special X-ray to check the tubal occlusion.

Pain in the lower abdomen and abnormal vaginal discharge are possible signs of a specific type of fallopian tube blockage called hydrosalpinx, although not all women have these signs. Fertilization and pregnancy are prevented because the fluid blocks the sperm and egg.

Blocked fallopian tubes can have many causes, some of which have unusual symptoms. For example, painful periods and painful sexual activity can be caused by endometriosis and pelvic inflammatory disease (PID).

Symptoms of pelvic infection include the following:
  • general pelvic pain and discomfort during sex
  • nausea and vomiting
  • fever over 101
  • Pelvic pain with severe pain in the lower abdomen or foul-smelling vaginal discharge

Causes of Blocked Fallopian Tubes :

Causes of blocked Fallopian Tubes

PID is the leading cause of the fallopian tube barrier. However, not all pelvic infections are associated with STDs, pelvic inflammatory disease results from an STD. Additionally, a PID or pelvic infection history increases the risk of tubal obstruction even without PID.

Additional factors that can block the fallopian tubes include:
  • Currently infected or previously infected with gonorrhoea or chlamydia as an STD
  • History of uterine infection resulting in miscarriage or stillbirth
  • History of appendix rupture.
  • history of abdominal surgery
  • ectopic pregnancy in the past
  • previous fallopian tube surgery, including tubal ligation
  • endometriosis

Diagnosis of Fallopian Tubes:

A hysterosalpingogram, or HSG, is a specialized X-ray commonly used to identify blocked tubes. One of the basic fertility tests required of all couples who have problems getting pregnant is the HSG. A small tube injects dye into the cervix during the test. After applying the dye, an X-ray of the pelvic area is taken. If all goes well, the dye should pass through the uterus and fallopian tubes before spreading around the ovaries and into the pelvic cavity. Your fallopian tubes can become blocked if the dye cannot pass through the tubes.

It is essential to know that 15% of women experience a “false positive,” in which the dye fails to enter the tube after passing through the uterus. The site of the blockage appears to be the junction of the uterus and fallopian tubes. If this happens, the doctor may order a new test to confirm or repeat the test one more time. Hysteroscopy, exploratory laparoscopic surgery, and ultrasound are examples of additional tests that may be ordered. It is also possible to request a blood test to detect antibodies against chlamydia.

Effects on Fertility:

The ovaries, uterus, and fallopian tubes comprise the female reproductive system. Getting pregnant can be more difficult if any of these three points are affected by a medical condition. The fallopian tubes connect each of the two ovaries to the uterus. An egg releases one egg every month from the ovary, which stores and releases them randomly.

For example, the left ovary can release an egg in one month, while the right ovary releases an egg for three consecutive months. An egg can be fertilized even if one of the fallopian tubes is blocked. It is less likely to happen if both are blocked.

Treatment of Blocked Fallopian Tubes : 

Treatment of Blocked Fallopian Tubes

If you are healthy and one of your tubes is open, you may be able to get pregnant without too much help. Your doctor may prescribe fertility drugs to increase your chances of ovulating on the side of the still-open tube. But if both tubes are blocked, there is no other option.

It is essential to understand that although this medication is provided to aid conception, a blocked fallopian tube cannot be unblocked. Exercise, just like a clogged tube, cannot be unblocked. Surgery is the only option to help clear blocked tubes, but it is only sometimes effective. Below are those you need to know about tubal ligation, IVF, and blocked tubal surgery.

Laparoscopic Surgery

In some circumstances, laparoscopic surgery can remove scar tissue or open blocked channels. Unfortunately, this action plan is only sometimes effective. The chances of success are affected by your age (the younger, the better), the location and severity of the blockage, and its underlying cause. Getting pregnant after surgery is good if there are only a few adhesions.

After surgery to relieve the tubal blockage, the chances of ectopic pregnancy increase. If you become pregnant, your doctor should monitor you closely and be available to advise you on what would be best for you.

However, surgery is not the best solution every time. Vital scars, moderate to severe endometriosis, or moderate to severe male infertility can benefit from IVF. 10 Your doctor can discuss your case with you to determine whether it would be better to have surgery to fix it or go straight to IVF treatment.

In Vitro Fertilization

Before the development of in vitro fertilization (IVF), women with blocked tubes had no choice but to become pregnant if reconstructive surgery did not work or was not an option. IVF makes pregnancy possible.

Fertility drugs are taken to stimulate ovulation during IVF. Sperm from the male spouse or sperm donor is combined with the egg in a laboratory. Ideally, some eggs will fertilize, and others will produce healthy embryos. The uterus receives one or two selected workable embryos.

Blockages in the fallopian tubes are irrelevant. However, studies show that irritated tubes can significantly reduce the chances of IVF success. If you have hydrosalpinx, your doctor may recommend surgical tube removal. IVF may be attempted once you have recovered from your procedure.

Tubal Ligation Reversal

Reversing a tubal ligation is a permanent method of birth control, also known as “tying your tubes.” Various tubal ligations can be performed. A surgeon can cut the tubes, bandage them, sear them, or place special coils inside them, among other options.

The good news is that although this form of birth control is meant to be permanent, many women can take it off. Compared to women who undergo tubal surgery to remove blockages caused by the disease, surgical repair of tubal ligation has a higher chance of success. A microsurgical repair can be up to 50% cheaper per delivery than IVF.

Conclusion

In the above article, we have talked about blocked fallopian tubes. Blocked fallopian tubes are a possible reason for female infertility. The woman’s fallopian tubes are blocked by hydrosalpinx. There are many symptoms like fever, vomiting, pain, etc. We have shared all the details of fallopian tubes in the above article. If you want to know more about blocked fallopian tubes, this article is for you.

If you want a suggestion for treatment for blocked fallopian tubes, you can rely on Imprimis IVF & Fertility Centre. Check out this hospital for Female Infertility Treatment. It is the best Best IVF Centre in Srinagar for blocked fallopian tubes. Here you will get the cooperative staff for treatment. The treatment is affordable and delivers the best quality hospitality services in Srinagar.

PCOD – Causes, Symptoms, and Treatment?

Polycystic ovary disorder (PCOD) is a hormonal disorder that causes irregular menstrual cycles in women. If an ultrasound of a woman’s lower abdomen shows a row of abnormally large, pearl-shaped eggs may be visible. Genetics is one of the many possible causes of PCOD. However, the disease became progressively more common in 1721. Antonio Vallisneri, an Italian physician, was the first to identify it. The disease’s original name was Stein-Leventhal syndrome. Get the PCOD treatment done by Imprimis IVF at a very affordable price in Srinagar.

What is PCOD Treatment?

PCOD, a polycystic ovary syndrome, is a hormonal and metabolic disorder. It happens when a woman’s body does not complete the monthly ovulation process. PCOD patients have fewer than eight menstrual cycles per year. Cysts on the ovarian lining are immature eggs trapped in the ovarian walls because they are not mature enough to leave the body. It causes an imbalance in the body’s hormonal levels, which increases androgen levels. These hormones cause unwanted body hair, weight gain, hair loss, and other medical issues.

Most women’s health problems currently affect 2-40% of women worldwide between 12 and 45 years old. The problem is difficult to solve due to its awareness and prevalence, and no one knows exactly why a woman gets PCOD.

Types of PCOD:

As noted above, PCOD is a relatively new subject of study, so there is still a lot of uncertainty surrounding it. In general, there are two forms of PCOD:

Insulin-Resistant PCOD

Type 1 PCOD, or insulin resistance, is usually accompanied by all the classic symptoms of PCOD, including obesity, facial hair growth, hair loss, and acne, all caused by high amounts of male hormones in the blood. The inability of the body to absorb sugar from the blood, as a result of which fat is stored, is a sign of this type of PCOD. Type 2 diabetes and heart disease can develop in people with PCOD type 1. The doctor advised them to start a diet and lose a few pounds. However, these patients may have difficulty losing weight. In addition to weight loss, patients may take medicines to control blood sugar.

Non-insulin-resistant PCOD

Non-insulin-resistant or type 2 PCOD is a condition in which the patient has no symptoms of insulin resistance but still has PCOD. Other factors, such as adrenal stress, thyroid, vitamin D deficiency, iodine deficiency, and others, can also contribute to non-insulin PCOD. For the body to heal naturally, PCOD type 2 treatment focuses more on rest and rhythmic activities.

PCOD Symptoms:

PCOD Symptoms

Symptoms of PCOD include:

  • Excessive or scanty menstrual flow.
  • Spotting during menstruation.
  • Irregular/late/early periods.
  • Short or long periods.
  • Abdominal pain.
  • Abnormal white discharge.

Causes of PCOD:

PCOD Causes

The exact cause of PCOD in women is unknown, but here are some of the important risk factors:

Excess insulin generation

A body with excess insulin can produce more androgens. This male hormone is too low in women and interferes with ovulation.

Excess androgen synthesis

The ovaries produce abnormally high levels of androgen hormones, which can cause acne and hirsutism (excessive growth of body and facial hair).

Minor Swelling

According to a new study, women with PCOD have low levels of inflammation that lead to increased androgen production, which can cause heart or vascular problems.

Heritage

Women with PCOD show a specific genetic correlation.

PCOD Treatment:

PCOD Treatment

Since PCOD is a chronic condition, many ways exist to treat its symptoms. Most women choose to combine several different strategies. Several Female Infertility Treatment methods are listed here:

Allopathy uses a variety of medications and diets. Women may need to use monthly birth control pills to promote regular periods. A woman may receive ovulation-inducing drugs to cure infertility or to help her get pregnant.

Patients can also follow a diet in addition to these to help with weight loss. To achieve the same results, the doctor may also recommend vigorous activities. When a woman loses even 3% of her body weight, her fertility improves.

Lifestyle Changes for PCOD Treatment:

PCOD affects the hormonal balance of most women. The following actions will help women reduce androgen levels in their bodies:

Maintain a healthy weight.

Losing weight or keeping it off improves overall cholesterol levels in the body, reduces the risk of diabetes, high blood pressure, and heart disease, maintains proper insulin and testosterone levels, and regulates the ovulation phase of the menstrual cycle. Consult a dietitian about a weight loss plan to achieve a healthy BMI.

Limit carbohydrate intake

If you have PCOD, follow a low-carbohydrate diet or a diet high in complex carbohydrates to stabilise your insulin levels. Avoid sugar and starches, and eat fish, meat, eggs, vegetables, and natural fats.

Participate in frequent activities and exercises.

Regular exercise and staying active will help control your weight and blood sugar if you have PCOD.

Can PCOD lead to other chronic diseases?

Yes, PCOD can lead to other chronic diseases. Losing weight can indeed help reverse PCOD. However, PCOD makes weight loss a challenge in itself. Here are some common chronic conditions caused by PCOD:

Diabetes

No one can explain why type 1 PCOD causes type 2 diabetes, but it does, as has already been shown. However, PCOD also causes gestational diabetes, so it doesn’t just cause type II diabetes. We all know that diabetes is a chronic, lifelong disease that contributes to 50% of deaths worldwide. It was India’s top killer in 2016-17. It is also true that most cases of PCOD go untreated in Indian society. Thus, the number of cases of diabetes in women has increased.

Blood Pressure

There is a close relationship between blood pressure and diabetes. No one is sure about the relationship between blood pressure and diabetes. However, the existence of one is a dead sign that the other exists.

Liver Disorders

As we all know, PCOD affects the liver, making it weak and prone to infections. A recent study has highlighted and supported this reality. Hormonal imbalance in the body directly affects the state of the liver. Moreover, it causes obesity, which leads to the development of NAFLD.

Anxiety and Depression

Female sex hormones influence a woman’s psyche. It means mood swings result from any disruption in the delicate balance of hormones. In addition, social isolation and a negative self-image are consequences of obesity. All these, combined with prolonged periods of persistent stress, can cause women to develop anxiety or depression. One study found that postpartum depression is more common in women with PCOD.

Infertility

PCOD is the main contributing factor to female infertility. While PCOD reversal medications can help treat this infertility, some women can only get pregnant after IVF or surgery.

Conclusion

PCOD is a common problem in women. It causes irregular periods and other issues. But it can be prevented by some lifestyle changes and treatments. In the above article, we have talked about PCOD in detail. If you want to know more about PCOD Treatment, this article is for you. If you want medical help in Srinagar, Best IVF Treatment Centre in Srinagar, Imprimis IVF, is always available. You will get the best services and PCOD treatment here.

Imprimis IVF Centre Branches: –

Best IVF Centre in Srinagar

Best IVF Centre in Jammu

IVF Centre in Leh Ladakh

Best IVF Centre in Bhubaneswar

Things to Consider Before IVF Treatment: A Complete Guide

Starting IVF treatment is an important decision, and knowing what to expect can make the process easier to understand and prepare for. Before beginning an IVF cycle, it is important to understand your fertility diagnosis, recommended treatment plan, medications, investigations, potential costs, expected outcomes and possible risks.

Infertility can affect either or both partners. Female factors may include ovulation disorders such as PCOS, endometriosis, reduced ovarian reserve, tubal problems and age-related fertility decline. Male factors, including low sperm count, poor sperm motility or abnormal sperm morphology, can also contribute to infertility.

Before starting IVF, your fertility specialist will assess your individual circumstances and recommend treatment based on your medical history, fertility investigations and reproductive goals.

Things to Consider Before IVF Treatment

If you are planning IVF, consider the following important factors before starting your treatment.

1. Understand Why IVF Has Been Recommended

IVF is not the first treatment for every person experiencing infertility.

Depending on the diagnosis, age, duration of infertility and previous treatment, your fertility specialist may recommend options such as ovulation induction, IUI or IVF.

IVF may be considered for conditions such as:

  • Blocked or damaged fallopian tubes
  • Certain forms of male-factor infertility
  • Reduced ovarian reserve
  • Endometriosis
  • Some cases of unexplained infertility
  • Certain ovulation-related infertility cases
  • Fertility preservation
  • Genetic or reproductive circumstances where IVF with additional testing may be appropriate
  • Previous unsuccessful fertility treatments

The right treatment depends on the individual couple rather than a single diagnosis.

For related information, read about [PCOS and fertility] and [endometriosis and infertility].

2. Have a Complete Fertility Assessment

Before IVF, your doctor will usually review both partners rather than focusing only on the female partner.

Depending on your circumstances, evaluation may include:

For the Female Partner

Your fertility specialist may assess:

  • Menstrual and ovulation history
  • Ovarian reserve
  • Ultrasound findings
  • Uterine anatomy
  • Previous pregnancies and fertility treatments
  • Medical and surgical history
  • Relevant blood tests

Tests may include ovarian reserve assessment, ultrasound and other investigations when clinically indicated.

For the Male Partner

Male fertility should also be assessed.

A semen analysis may evaluate:

  • Sperm concentration
  • Sperm motility
  • Sperm morphology

Further evaluation may be recommended when semen parameters are abnormal or when there is a relevant medical history.

This is important because infertility can involve male, female or combined factors.

Read more about [male infertility].

3. Discuss Your IVF Treatment Plan With Your Doctor

Every IVF cycle is different.

Before starting treatment, ask your fertility specialist:

  1. Why is IVF recommended for us?
  2. What fertility factors have been identified?
  3. What medications will I need?
  4. How long is the expected treatment cycle?
  5. How will my ovaries and hormone response be monitored?
  6. What happens if the response to stimulation is lower or higher than expected?
  7. How will embryos be selected for transfer?
  8. Will embryo freezing be considered?
  9. Should we consider a fresh or frozen embryo transfer?
  10. What additional procedures, if any, may be appropriate?

Having these questions answered can help you understand your treatment rather than relying on general information found online.

4. Understand That IVF Does Not Guarantee Pregnancy

One of the most important things to know before IVF is that IVF cannot guarantee pregnancy or a live birth.

IVF outcomes can vary according to factors such as:

  • Age
  • Ovarian reserve
  • Egg and embryo factors
  • Sperm quality
  • Uterine factors
  • Cause and duration of infertility
  • Previous fertility treatment
  • Embryo development
  • Treatment protocol

Therefore, avoid clinics or websites that promise a guaranteed IVF pregnancy.

Instead, ask your fertility specialist how success rates are measured and which factors are relevant to your individual situation.

Read our detailed guide to [IVF success rate].

5. Understand the IVF Treatment Process

Knowing the basic stages can help you prepare.

Depending on your treatment plan, an IVF cycle may involve:

  1. Initial fertility assessment
  2. Ovarian stimulation
  3. Ultrasound and hormone monitoring
  4. Trigger medication when appropriate
  5. Egg retrieval
  6. Fertilisation in the laboratory
  7. Embryo culture and development
  8. Embryo transfer or embryo freezing
  9. Pregnancy testing at the appropriate time

Not every patient will follow exactly the same protocol.

Your fertility specialist will adjust medications and monitoring according to your ovarian response and medical circumstances.

For a step-by-step explanation, read [the stages of IVF treatment].

6. Know the Possible Role of ICSI

Intracytoplasmic sperm injection, commonly called ICSI, is a laboratory fertilisation technique in which a single sperm is injected directly into an egg.

ICSI may be particularly useful in selected cases of male-factor infertility or previous fertilisation failure.

However, ICSI is not automatically required for every IVF patient.

Your fertility specialist and embryology team can explain whether ICSI is appropriate for your specific circumstances.

Read more about [ICSI treatment in Srinagar].

7. Ask About Embryo Transfer and Embryo Freezing

Before your IVF cycle, discuss what may happen to embryos created during treatment.

Depending on embryo development and your treatment plan, embryos may be:

  • Transferred during the current cycle
  • Frozen for possible future use
  • Used in a later frozen embryo transfer cycle

The number of embryos transferred should be discussed carefully with your fertility specialist because transferring multiple embryos can increase the risk of multiple pregnancy.

Ask your clinic:

  • How many embryos are recommended for transfer?
  • What happens to suitable embryos that are not transferred?
  • What are the benefits and limitations of embryo freezing?
  • Is frozen embryo transfer appropriate in my situation?

8. Review Your General Health Before IVF

Preparing for IVF involves more than fertility tests.

Before treatment, tell your doctor about:

  • Existing medical conditions
  • Previous surgeries
  • Previous pregnancies
  • Current medications
  • Supplements
  • Allergies
  • Smoking or tobacco use
  • Alcohol consumption
  • Previous fertility treatment

Your doctor may recommend additional tests or medical optimisation before starting treatment.

If you have diabetes, thyroid disease, PCOS, hypertension, anaemia or another medical condition, appropriate management may be important before pregnancy.

9. Prepare for IVF Medications and Injections

IVF commonly involves hormonal medications and injections.

Your clinic should explain:

  • Which medication you are taking
  • Why it has been prescribed
  • When and how to take it
  • Possible side effects
  • What to do if you miss a dose
  • When to contact the clinic

Do not change the dose or stop IVF medication without discussing it with your fertility team.

Keeping a simple medication schedule can help you stay organised during treatment.

10. Understand IVF Cost Before Starting Treatment

The cost of IVF treatment can vary considerably.

It may depend on:

  • Treatment protocol
  • Fertility medications
  • Blood tests and ultrasound monitoring
  • Egg retrieval
  • Laboratory procedures
  • ICSI, when indicated
  • Embryo culture
  • Embryo freezing and storage
  • Frozen embryo transfer
  • Additional investigations or procedures

Rather than asking only for the advertised “IVF package,” ask the clinic what is included and which services may cost extra.

11. Choose an IVF Clinic Carefully

Choosing an IVF clinic is an important part of your treatment preparation.

When comparing fertility clinics, consider:

Fertility Specialists

Ask about the qualifications and experience of the doctors who will manage your treatment.

Embryology Laboratory

The IVF laboratory plays an important role in assisted reproductive treatment. Ask about laboratory facilities, embryo culture, witnessing systems and embryo storage procedures.

Treatment Transparency

The clinic should clearly explain:

  • Treatment options
  • Expected costs
  • Medications
  • Additional procedures
  • Potential risks
  • Follow-up care

Individualised Treatment

Your treatment plan should be based on your diagnosis and circumstances rather than a one-size-fits-all package.

Patient Support

Consider whether the clinic provides clear communication and appropriate support throughout the IVF process.

12. Ask These Questions Before Choosing an IVF Centre

Before making a decision, consider asking:

  • What is the recommended treatment for my diagnosis?
  • Who will manage my IVF cycle?
  • What tests do I need before treatment?
  • What medications will I need?
  • What is included in the IVF package?
  • What additional costs should I expect?
  • How are embryos monitored in the laboratory?
  • How many embryos are generally transferred?
  • What happens to suitable embryos that are not transferred?
  • What are the potential risks of treatment?
  • What follow-up care is provided after embryo transfer?

These questions can help you make an informed decision about your fertility care.

13. Maintain a Healthy Lifestyle Before IVF

A healthy lifestyle can support general health while preparing for pregnancy.

Consider:

  • Eating a balanced diet
  • Maintaining a healthy weight where appropriate
  • Staying physically active as advised
  • Avoiding smoking and tobacco
  • Avoiding recreational drugs
  • Avoiding alcohol when pregnancy is possible
  • Taking prenatal supplements such as folic acid when recommended
  • Getting adequate sleep
  • Managing stress in healthy ways

Lifestyle changes cannot guarantee IVF success, but they can contribute to overall health and pregnancy preparation.

14. Pay Attention to Your Mental and Emotional Wellbeing

IVF can be emotionally demanding.

You may experience excitement, uncertainty, anxiety, disappointment or stress during different stages of treatment.

You do not need to feel positive all the time for IVF to work.

Consider seeking support from:

  • Your partner
  • Family or trusted friends
  • A counsellor
  • A fertility support group
  • Your fertility clinic’s support team

Managing emotional wellbeing is part of taking care of yourself during treatment.

15. Understand the Possibility of More Than One IVF Cycle

Some patients become pregnant after their first IVF cycle, while others may require additional treatment.

An unsuccessful cycle does not automatically mean that future treatment will not work.

If an IVF cycle is unsuccessful, your fertility specialist may review:

  • Ovarian response
  • Number of eggs retrieved
  • Fertilisation
  • Embryo development
  • Endometrial and uterine factors
  • Sperm-related factors
  • Previous treatment history

The next step should be based on the findings from your individual cycle rather than following a fixed formula.

16. Understand Multiple Pregnancy Risks

One important question to ask before IVF is how many embryos should be transferred.

Transferring more than one embryo can increase the chance of multiple pregnancy, which can carry additional maternal and pregnancy risks.

Your fertility specialist will discuss an embryo-transfer strategy based on your age, embryo factors, medical history, and applicable clinical guidance.

17. Understand That IVF Is Not the Same for Everyone

There is no single IVF protocol that works for every patient.

For example, a woman with PCOS may require a different stimulation strategy from someone with reduced ovarian reserve.

Similarly, a couple with severe male-factor infertility may have different laboratory considerations from a couple with unexplained infertility.

This is why a personalised fertility assessment is important before starting treatment.

What Should You Take to Your First IVF Consultation?

Preparing a few important details can make your consultation more useful.

Bring or note:

  • Previous fertility reports
  • Semen analysis reports
  • Ultrasound reports
  • Previous IVF/IUI records
  • Previous pregnancy records
  • List of current medications
  • Medical and surgical history
  • Menstrual-cycle information
  • Questions about cost and treatment
  • Any previous genetic or hormonal test results

Your doctor can then better understand your fertility history and discuss possible treatment options.

IVF Treatment in Srinagar

If you are looking for IVF treatment in Srinagar, choosing a fertility centre should involve more than comparing advertisements or headline success-rate claims.

At Imprimis IVF & Fertility Centre, Srinagar, patients can discuss infertility evaluation, IVF, IUI, ICSI and other fertility treatment options with the fertility team.

Frequently Asked Questions About Preparing for IVF

What should I do before starting IVF?

Before IVF, complete the recommended fertility evaluation, review your medical history and medications with your doctor, follow healthy lifestyle habits and understand your treatment plan and expected costs.

What tests are needed before IVF?

Tests vary between patients. Your fertility specialist may recommend ovarian reserve assessment, ultrasound, semen analysis and other blood or fertility investigations depending on your medical history.

How should I prepare my body for IVF?

Focus on balanced nutrition, appropriate physical activity, adequate sleep, avoiding tobacco and recreational drugs, limiting alcohol and taking recommended prenatal supplements such as folic acid.

Does IVF guarantee pregnancy?

No. IVF can result in pregnancy, but no fertility treatment can guarantee a successful pregnancy or live birth.

What questions should I ask an IVF doctor?

Ask why IVF is recommended, what treatment protocol is planned, what medications you will use, what costs are included, how embryos will be managed, what risks may apply and what alternatives are available.

How much does IVF cost in Srinagar?

The cost varies depending on the treatment protocol, medications, laboratory procedures, ICSI, embryo freezing, frozen embryo transfer, and other individual requirements. Ask the clinic for a current, itemised estimate.

Is ICSI required for every IVF cycle?

No. ICSI may be recommended in selected situations, particularly certain male-factor infertility cases or previous fertilisation failure. It is not automatically necessary for every IVF cycle.

Final Takeaway

Preparing for IVF involves more than starting fertility injections.

Before beginning treatment, understand why IVF has been recommended, complete the appropriate fertility evaluation, review your health and medications, understand the treatment process, discuss embryo transfer, ask about costs and choose a fertility clinic carefully.

Most importantly, remember that IVF outcomes are individual. A personalised treatment plan from a qualified fertility specialist is more useful than relying on general promises or claims of guaranteed success.

Medical Review & Clinic Information

Medical Reviewer: Imprimis IVF Team
Last Updated: September 19, 2026
Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014

Medical Disclaimer: This article is for general educational purposes and does not replace personalised medical advice, diagnosis or treatment. IVF treatment and investigations vary from patient to patient. Consult a qualified fertility specialist for advice based on your individual medical history.

IVF Diet Chart: Foods to Eat and Avoid During IVF Treatment

IVF Diet Chart: Starting IVF treatment can bring many questions, including one of the most common: What should I eat during IVF?

An IVF diet chart cannot guarantee a successful IVF cycle, and there is no single food that can make an embryo implant or increase IVF success on its own. However, eating a balanced, nutritious diet can support overall health, provide essential nutrients, and help you maintain a healthy lifestyle before and during fertility treatment.

Research on specific dietary patterns and IVF outcomes remains mixed. Some studies have reported associations between healthier dietary patterns and IVF outcomes, while others have not found a consistent benefit. Therefore, diet should be viewed as part of overall preconception and fertility care rather than a replacement for medical treatment.

What Is an IVF Diet Chart?

An IVF diet chart is a practical eating plan designed to help you maintain good nutrition during fertility treatment.

Instead of focusing on a “miracle IVF food,” the goal should be to include a variety of:

  • Vegetables and leafy greens
  • Fresh fruits
  • Whole grains
  • Beans, lentils and other legumes
  • Nuts and seeds
  • Healthy sources of protein
  • Healthy fats
  • Dairy or suitable alternatives
  • Adequate fluids

A healthy dietary pattern can support general health, while fertility treatment addresses the specific medical causes of infertility. The World Health Organisation also recommends healthy lifestyle measures, including a healthy diet and physical activity, for people planning or attempting pregnancy.

Does Diet Increase IVF Success Rate?

This is one of the most searched questions about IVF nutrition.

The short answer is: no specific IVF diet has been proven to guarantee IVF success.

Studies investigating Mediterranean-style diets, fertility diets and individual nutrients have produced inconsistent findings in people undergoing assisted reproductive treatment. Therefore, it is not appropriate to promise that a particular food, drink or diet will improve implantation, egg quality or live birth rates.

However, maintaining a nutritious diet can help support overall health during IVF and pregnancy planning.

Your IVF outcome depends on several factors, including:

  • Age
  • Ovarian reserve
  • Egg and embryo factors
  • Sperm quality
  • Uterine and tubal factors
  • Underlying medical conditions
  • Previous fertility treatment
  • Embryo genetics in selected cases
  • The specific IVF treatment plan

For more information, read our guide to [IVF Success Rate].

IVF Diet Chart: Foods to Eat During IVF Treatment

IVF Diet Chart


There is no mandatory list of “fertility foods.” Instead, aim for a varied and minimally processed diet.

1. Protein-Rich Foods

Protein is an important part of a balanced diet and is needed for tissue growth and repair.

Good choices include:

  • Eggs, when fully cooked
  • Milk and yoghurt
  • Paneer in moderate portions
  • Dal and lentils
  • Chickpeas and kidney beans
  • Soy and tofu
  • Nuts and seeds
  • Chicken and other lean meats
  • Well-cooked fish

There is no universal requirement that every woman undergoing IVF consume exactly 60 grams of protein per day. Protein requirements vary according to body size, activity level, pregnancy status, and medical needs.

2. Green Leafy Vegetables

Include vegetables such as:

  • Spinach
  • Methi
  • Broccoli
  • Cabbage
  • Beans
  • Peas
  • Capsicum
  • Carrots
  • Other seasonal vegetables

Leafy greens also provide folate, fibre and several vitamins and minerals.

3. Whole Grains and High-Fibre Foods

Choose whole or minimally processed carbohydrates more often, such as:

  • Oats
  • Whole-wheat roti
  • Brown rice
  • Millets
  • Quinoa
  • Barley
  • Whole-grain bread

Legumes such as chickpeas, rajma, peas and lentils can also provide fibre and plant-based protein.

4. Fruits

Fresh fruits can be part of a healthy IVF diet.

Options include:

  • Apples
  • Oranges
  • Guava
  • Berries
  • Pomegranate
  • Bananas
  • Papaya
  • Pears
  • Seasonal fruits

There is no strong evidence that one particular fruit, including pineapple, guarantees implantation or improves IVF success. Choose fruits for overall nutrition rather than as a fertility treatment.

5. Healthy Fats

Include moderate amounts of unsaturated fats from foods such as:

  • Nuts
  • Seeds
  • Avocado
  • Olive oil
  • Groundnut oil
  • Mustard oil
  • Fatty fish that is low in mercury

Healthy fats can form part of a balanced dietary pattern, but they should not be viewed as an IVF success booster.

6. Folic Acid and Folate-Rich Foods

Folic acid is particularly important before conception because it helps reduce the risk of neural tube defects.

Women planning pregnancy are generally advised to take 400 micrograms (mcg) of folic acid daily, unless their healthcare professional recommends a different dose.

Food sources of folate include:

  • Green leafy vegetables
  • Beans
  • Lentils
  • Peas
  • Citrus fruits
  • Fortified grains

Your fertility specialist may recommend a prenatal vitamin based on your individual nutritional requirements.

7. Iron-Rich Foods

Iron is essential for making haemoglobin and supporting normal blood function.

Food sources include:

  • Lentils
  • Beans
  • Spinach and other leafy greens
  • Sesame seeds
  • Pumpkin seeds
  • Meat and poultry
  • Iron-fortified cereals

The required amount of iron varies by life stage and pregnancy status. Do not take high-dose iron supplements unless advised by your doctor or after an assessment of your iron status.

8. Calcium and Vitamin D

Calcium and vitamin D are important for overall health and are particularly important during pregnancy.

Dietary sources can include:

  • Milk
  • Curd/yoghurt
  • Fortified dairy alternatives
  • Paneer
  • Eggs
  • Certain fish

Vitamin D deficiency is relatively common, but taking high-dose vitamin D without testing or medical advice is not recommended.

9. Low-Mercury Fish

You do not need to avoid all seafood during IVF.

Cooked, low-mercury fish can be part of a healthy diet. However, certain fish contain higher levels of mercury and should be avoided or limited, particularly during pregnancy. ACOG advises avoiding fish such as shark, swordfish, king mackerel, marlin and bigeye tuna during pregnancy.

Choose fish according to current pregnancy food-safety recommendations and local guidance.

Hydration During IVF

Adequate hydration is important for general health.

Drink water regularly throughout the day, and increase your intake as needed due to heat, exercise, or other circumstances.

However, there is no established evidence that drinking a specific number of glasses of water thickens the uterine lining or directly improves embryo implantation.

If you have a medical condition that requires fluid restriction, follow your doctor’s instructions.

IVF Diet Chart: What to Avoid or Limit

Foods to avoid during IVF Treatment

1. Alcohol

It is safest to avoid alcohol when undergoing IVF and when pregnancy is possible.

Alcohol can have adverse effects during pregnancy, and there is no established safe level of alcohol consumption during pregnancy.

2. Smoking and Tobacco

Avoid smoking and exposure to secondhand smoke.

Tobacco use is associated with poorer reproductive outcomes, and evidence indicates that smoking can negatively affect assisted reproductive treatment outcomes.

3. Excessive Caffeine

You do not necessarily need to eliminate caffeine entirely, but keeping intake below 200 mg per day is a commonly recommended safety limit during pregnancy. Remember that caffeine is also found in tea, chocolate, cola and energy drinks—not only coffee.

If you are unsure about the caffeine content of your usual drinks, ask your fertility specialist or dietitian.

4. Raw or Undercooked Eggs

Avoid raw or undercooked eggs due to the risk of foodborne illness.

Be particularly careful with foods prepared using raw eggs, such as some homemade mayonnaise, mousse and certain desserts.

5. Unpasteurized Milk and Dairy Products

Choose pasteurised milk and dairy products.

Unpasteurized products can carry bacteria that may cause serious foodborne infections during pregnancy.

6. Raw or Undercooked Meat and Seafood

Cook meat, poultry, eggs and seafood thoroughly.

Avoid raw fish and shellfish because they can increase the risk of foodborne illness.

7. High-Mercury Fish

Avoid fish known to contain high levels of mercury, particularly once pregnancy is established.

Your fertility team can provide guidance on safe seafood choices.

8. Highly Processed Foods and Excess Added Sugar

You do not need to eliminate all packaged foods from your diet.

However, try to limit frequent consumption of:

  • Sugary beverages
  • Sweets
  • Cakes and pastries
  • Highly processed snacks
  • Deep-fried foods
  • Processed meats
  • Foods high in added sugar and saturated fat

A balanced diet is more sustainable than extreme food restrictions.

Simple 1-Day IVF Diet Chart

The following is a general example, not a personalised medical diet.

Time Example
Morning Water + prescribed prenatal/folic acid supplement
Breakfast Vegetable oats/poha/upma + fully cooked egg or yoghurt
Mid-morning One seasonal fruit + a small handful of nuts
Lunch Roti/brown rice + dal + vegetables + curd
Evening Roasted chana/makhana or fruit + unsweetened tea
Dinner Roti/millet + cooked vegetables + dal/paneer/chicken/fish
Bedtime Milk or suitable alternative, if tolerated

Your calorie and nutrient requirements may be different. Patients with PCOS, diabetes, thyroid disorders, anaemia, obesity, underweight, food allergies or other medical conditions may need an individualised plan.

Is Five Meals a Day Necessary During IVF?

No.

There is no universal requirement to eat five meals every day during IVF.

Some people prefer smaller, frequent meals because they experience nausea, bloating or reduced appetite during treatment. Others are comfortable with three main meals and one or two snacks.

The important point is to maintain adequate nutrition and follow the dietary advice given by your healthcare team.

Can I Eat Pineapple During IVF?

Yes, pineapple can be part of a normal, balanced diet if you tolerate it.

However, there is no strong evidence that pineapple or its core can improve embryo implantation or increase IVF success.

The same principle applies to other foods sometimes promoted online as “implantation foods.” They can be nutritious, but they should not be presented as fertility treatments.

What Should I Eat After Embryo Transfer?

After embryo transfer, you generally do not need a special “implantation diet.”

Focus on:

  • Balanced meals
  • Adequate protein
  • Vegetables and fruits
  • Whole grains
  • Healthy fats
  • Adequate fluids
  • Folic acid/prenatal supplements as prescribed
  • Safe food preparation

Avoid alcohol, smoking and unsafe foods such as raw or undercooked animal products and high-mercury fish.

Continue your prescribed IVF medications exactly as instructed.

For more information, see [Embryo Transfer] and [IVF Treatment in Srinagar].

Can Diet Improve Egg Quality During IVF?

Diet provides the nutrients required for normal bodily functions, but no specific food or diet has been proven to “repair” or guarantee better egg quality.

Egg quality is influenced by several factors, including age and ovarian biology. A healthy lifestyle can support overall reproductive health, but it should not be promoted as a guaranteed way to improve egg quality.

If you have concerns about ovarian reserve or egg quality, discuss them with your fertility specialist.

Do I Need Supplements During IVF?

Not everyone undergoing IVF needs the same supplements.

Your fertility specialist may recommend supplements based on your medical history, blood tests, dietary intake and pregnancy-planning needs.

Commonly discussed nutrients include:

  • Folic acid
  • Iron
  • Vitamin D
  • Vitamin B12
  • Calcium

Do not start high-dose vitamins, minerals or herbal fertility supplements without medical advice.

IVF Diet and Lifestyle: Other Important Tips

Diet is only one part of preparing for IVF.

Take IVF Medicines on Time

Follow your fertility specialist’s instructions for hormonal injections, tablets and other medications.

Do not change the dose or stop medication without consulting your treatment team.

Stay Physically Active as Advised

Regular physical activity can support overall well-being. However, your activity level may need to be modified during ovarian stimulation or after specific procedures.

Always follow your fertility team’s instructions.

Avoid Smoking and Recreational Drugs

Smoking, tobacco and recreational drug use can negatively affect reproductive health. Tobacco cessation is particularly important when planning pregnancy.

Prioritise Sleep and Emotional Wellbeing

IVF can be physically and emotionally demanding.

Good sleep, emotional support, counselling when needed and realistic expectations can help you manage the treatment journey.

You do not need to maintain “constant positivity” for IVF to be successful. Treatment outcomes are not determined by whether a patient feels positive or anxious.

Is Strict Bed Rest Required After Embryo Transfer?

Routine strict bed rest is generally not required after embryo transfer.

Your fertility clinic may provide specific instructions about activity based on your procedure and medical circumstances. Follow those instructions rather than remaining in bed unnecessarily.

If you experience significant pain, heavy bleeding, breathing difficulty, severe abdominal swelling or other concerning symptoms after treatment, contact your fertility clinic promptly.

Can an IVF Diet Guarantee IVF Success?

No.

There is no diet, food, supplement or lifestyle change that can guarantee pregnancy or live birth through IVF.

IVF outcomes depend on multiple medical and biological factors. A healthy diet can support your overall health, but it should complement—not replace—evidence-based fertility treatment.

The WHO’s current infertility guidance supports evidence-based, patient-centred fertility care alongside healthy lifestyle measures.

Frequently Asked Questions About IVF Diet

What is the best diet during IVF treatment?

A balanced diet containing vegetables, fruits, whole grains, legumes, healthy protein sources and unsaturated fats is a practical approach. Your individual diet should be adjusted for your medical and nutritional needs.

Which foods should I avoid during IVF?

Avoid alcohol and smoking. Also avoid or limit foods with food-safety risks, including raw or undercooked eggs, meat and seafood, unpasteurized products and high-mercury fish.

Can I drink tea or coffee during IVF?

Moderate caffeine intake may be acceptable, but during pregnancy and when pregnancy is possible, keeping caffeine below 200 mg per day is commonly advised.

Can I eat fish during IVF?

Yes. Seafood does not need to be completely eliminated. Choose properly cooked, low-mercury fish and avoid high-mercury varieties according to pregnancy food-safety recommendations.

Is pineapple good for IVF implantation?

Pineapple can be part of a healthy diet, but there is no strong evidence that eating pineapple increases embryo implantation or IVF success.

Should I take folic acid during IVF?

Women planning pregnancy are generally advised to take 400 mcg of folic acid daily, unless their doctor recommends another dose.

Do I need five meals a day during IVF?

No. There is no universal requirement to eat five meals daily. Choose a meal pattern that meets your nutritional needs and feels comfortable for you.

Can an IVF diet improve my chances of pregnancy?

A nutritious diet supports general health, but no specific IVF diet has been proven to guarantee pregnancy or live birth. IVF success depends on many individual factors.

Final Takeaway: IVF Diet Chart

Following a healthy IVF diet chart can help you maintain good nutrition throughout fertility treatment, but there is no miracle food that guarantees implantation or IVF success.

Focus on a varied diet with vegetables, fruits, whole grains, legumes, lean proteins, nuts, seeds, and appropriate sources of healthy fats. Take folic acid and other supplements only as recommended by your healthcare professional.

Most importantly, avoid smoking and recreational drugs, avoid alcohol, keep caffeine moderate, and follow pregnancy food-safety precautions.

Your fertility specialist can help you create an IVF nutrition plan based on your medical history, treatment protocol and nutritional requirements.

If you are planning IVF treatment in Srinagar, you can consult the fertility team at Imprimis IVF & Fertility Centre, Srinagar for an individualised fertility assessment and treatment plan.

Medical Review & Clinic Information

Medical Reviewer: Imprimis IVF Team
Last Updated: September 19, 2026
Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014

Medical Disclaimer: This article is intended for educational purposes and should not replace personalised medical advice, diagnosis or treatment. Dietary requirements during IVF can vary considerably. Consult your fertility specialist or qualified dietitian before making significant dietary or supplement changes.

IVF vs IUI: Which Fertility Treatment Is Right for You?

When you’re trying to conceive and fertility treatment has become part of your journey, one question often comes up: IVF vs IUI—which is better?

The answer is not the same for every couple.

Intrauterine insemination (IUI) and in vitro fertilisation (IVF) are different fertility treatments used for different clinical situations. IUI is generally less invasive and less expensive, while IVF is a more advanced treatment in which eggs are retrieved and fertilised in a laboratory before an embryo is transferred to the uterus.

The choice between IUI and IVF depends on several factors, including:

  • Age of the female partner
  • Duration of infertility
  • Cause of infertility
  • Ovulation status
  • Fallopian tube condition
  • Sperm count and motility
  • Ovarian reserve
  • Previous fertility treatments
  • Other medical conditions
  • Patient preferences and treatment goals

There is therefore no universal answer to “IVF vs IUI, which is better?” A fertility specialist can recommend an appropriate treatment after evaluating both partners.

IVF vs IUI: Quick Comparison

Factor IUI IVF
Full form Intrauterine Insemination In Vitro Fertilisation
Where fertilisation occurs Inside the reproductive tract In a laboratory
Egg retrieval No Yes
Embryo created in laboratory No Yes
Procedure complexity Less invasive More involved
Typical treatment cost Lower Higher
Treatment duration Usually shorter Usually longer
Useful for Selected infertility cases A wider range of infertility conditions
Multiple pregnancy risk Can increase with ovarian stimulation Can be reduced with single embryo transfer
Treatment choice Depends on diagnosis Depends on diagnosis

The table is a general comparison. Your fertility specialist may recommend a different approach depending on your individual medical circumstances.


What Is IUI?

IUI (Intrauterine Insemination) is a fertility treatment in which specially prepared sperm are placed directly inside the uterus around the time of ovulation.

The aim is to place a higher concentration of motile sperm closer to the fallopian tubes, where fertilisation can occur naturally.

IUI may be performed during a natural ovulatory cycle or together with medicines that stimulate ovulation, depending on the patient’s fertility diagnosis.

How Does IUI Work?

A typical IUI cycle may involve:

  1. Monitoring the menstrual cycle and ovulation.
  2. Using fertility medicines when clinically appropriate.
  3. Monitoring follicular development through ultrasound.
  4. Preparing a semen sample in the laboratory.
  5. Placing the prepared sperm into the uterus using a thin catheter.
  6. Monitoring for pregnancy after the procedure.

The actual insemination procedure is usually brief and does not generally require anaesthesia.

IUI does not involve egg retrieval or laboratory fertilisation.


What Is IVF?

IVF (In Vitro Fertilisation) is an assisted reproductive technology in which eggs are retrieved from the ovaries and fertilised with sperm in a laboratory.

After fertilisation, embryos are cultured, and one or more embryos may be transferred into the uterus.

A typical IVF cycle may involve:

  1. Ovarian stimulation
  2. Ultrasound and hormone monitoring
  3. Trigger medication when appropriate
  4. Egg retrieval
  5. Fertilisation with sperm
  6. Embryo culture
  7. Embryo transfer or freezing
  8. Pregnancy testing

Depending on the treatment plan, additional procedures such as ICSI, embryo freezing or genetic testing may be considered.


IVF vs IUI: What Is the Main Difference?

The biggest difference between IUI and IVF is where fertilisation occurs.

With IUI, sperm are placed inside the uterus and fertilisation must occur naturally within the reproductive tract.

With IVF, eggs are retrieved and fertilised in a laboratory. The resulting embryo is then transferred into the uterus.

This makes IVF a more involved treatment, but it also allows fertility specialists to address a broader range of fertility problems.


When Is IUI Recommended?

IUI may be considered for selected patients with:

Unexplained Infertility

IUI with ovarian stimulation is commonly used as an initial treatment approach for many couples with unexplained infertility.

Current guidance supports treatment pathways that may progress from less invasive approaches such as stimulated IUI to IVF when appropriate. (asrm.org)

Mild Male-Factor Infertility

IUI may be considered when sperm parameters are suitable for insemination after evaluation and processing.

The decision should not be based on a single semen analysis result.

Ovulation Problems

Women with ovulation disorders may sometimes undergo ovulation induction followed by IUI, depending on the underlying condition.

Selected Cases of Cervical-Factor Infertility

IUI can bypass the cervix by placing prepared sperm directly into the uterus.

Donor Sperm Treatment

IUI may also be used with donor sperm when clinically appropriate.

The suitability of IUI depends on factors such as ovarian function, ovulation, fallopian tube status, sperm quality and age.


When Is IVF Recommended?

IVF may be considered when there is a medical reason for a more advanced fertility treatment or when simpler treatments have not been successful.

Potential situations include:

Blocked or Severely Damaged Fallopian Tubes

Because IVF bypasses the fallopian tubes during fertilisation, it may be recommended when the tubes are blocked or significantly damaged.

Severe Male-Factor Infertility

IVF, often combined with ICSI when indicated, may be considered for severe sperm abnormalities or certain situations involving very low or absent sperm in the ejaculate.

Repeatedly Unsuccessful IUI

If appropriately selected IUI cycles do not result in pregnancy, a fertility specialist may recommend moving to IVF.

The number of IUI cycles before IVF is not identical for every patient.

Reduced Ovarian Reserve or Age-Related Fertility Decline

Age and ovarian reserve are important when deciding how quickly to progress through fertility treatment.

For some patients, proceeding directly to IVF may be discussed rather than spending several cycles on less effective treatments.

Endometriosis

Depending on the severity of endometriosis, age and other fertility factors, IVF may be considered.

Genetic or Chromosomal Indications

IVF may be used when preimplantation genetic testing is being considered for an appropriate medical indication.

Other Infertility Factors

IVF may also be recommended when multiple fertility factors are present or when other treatments are unlikely to provide a reasonable opportunity for pregnancy.


IVF vs IUI for Male Infertility

Male-factor infertility can influence the choice between IUI and IVF.

A semen analysis evaluates several important parameters, including:

  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Semen volume

IUI may be suitable when there is an adequate number of motile sperm after semen processing.

When sperm abnormalities are more severe, IVF with ICSI (Intracytoplasmic Sperm Injection) may be considered.

ICSI involves injecting a single sperm directly into an egg. It is particularly relevant when there is a clear male-factor indication or a history of fertilisation failure. Current ASRM guidance cautions against using ICSI routinely for non-male-factor infertility without a specific indication. (asrm.org)


IVF vs IUI for Female Infertility

Female fertility can be affected by the ovaries, fallopian tubes, uterus, hormones and age.

IUI may be considered when:

  • At least one fallopian tube is functioning
  • Ovulation can be achieved
  • Sperm parameters are suitable
  • There is no major uterine or tubal factor requiring IVF

IVF may be considered when:

  • Both fallopian tubes are blocked
  • Ovarian reserve is reduced
  • There are significant fertility factors
  • Previous IUI treatment has failed
  • Age or other circumstances make a more direct treatment approach appropriate

A complete fertility evaluation helps determine which treatment is appropriate.


IVF vs IUI Success Rate

One of the most common searches is “IUI vs IVF success rate.”

However, quoting one fixed success percentage can be misleading.

Success depends on factors such as:

  • Age
  • Diagnosis
  • Ovarian reserve
  • Egg and embryo quality
  • Sperm quality
  • Number of treatment attempts
  • Treatment protocol
  • Previous fertility history
  • Clinic and laboratory factors

IVF generally offers a higher chance of pregnancy per treatment cycle than IUI for many infertility situations, but the comparison should be made using the same outcome measure and patient population.

A clinic should therefore not promise a specific pregnancy or live-birth rate without considering the individual patient’s circumstances.

For patients with unexplained infertility, evidence-based guidelines support stimulated IUI as a treatment option before IVF in many cases, while also recognising that factors such as age and treatment history can change the treatment pathway. (asrm.org)


IVF vs IUI Cost

Cost is another important factor when comparing IUI vs IVF.

Generally, IUI costs less per treatment cycle because it does not involve egg retrieval, laboratory fertilisation or embryo culture.

IVF usually costs more because it involves ovarian stimulation, monitoring, egg retrieval, laboratory fertilisation, embryo culture and embryo transfer.

However, the total cost can vary significantly depending on:

  • Medicines and injections
  • Diagnostic tests
  • Number of treatment cycles
  • ICSI
  • Embryo freezing
  • Frozen embryo transfer
  • Genetic testing
  • Donor eggs or sperm
  • Other clinically indicated procedures

Therefore, rather than relying on a single online price, ask the fertility clinic for a personalised treatment estimate and clarify what is included.

For information about local treatment pricing, see our IVF treatment cost in Srinagar and IUI treatment in Srinagar pages.


IUI vs IVF: Which Is More Painful?

Both IUI and IVF can involve some discomfort, but the experience varies from person to person.

IUI

IUI is generally a short procedure. Some women experience mild cramping or temporary discomfort when the catheter is inserted.

IVF

IVF involves more steps and usually includes injectable ovarian stimulation and an egg-retrieval procedure.

Egg retrieval is generally performed with appropriate pain relief or sedation, in accordance with the clinic’s protocol.

Therefore, it is not accurate to describe IVF simply as “painful” or IUI as completely “painless.” Individual experiences vary.


IUI vs IVF: Treatment Duration

IUI usually involves fewer treatment steps than IVF.

An IUI cycle may involve:

  • Cycle monitoring
  • Ovulation induction when required
  • Trigger medication when appropriate
  • Sperm preparation
  • Insemination
  • Pregnancy testing

IVF generally involves more appointments and procedures, including ovarian stimulation, monitoring, egg retrieval, fertilisation and embryo transfer.

The total IVF timeline varies depending on the treatment protocol and whether a fresh or frozen embryo transfer is planned.


Benefits and Limitations of IUI

Potential Benefits of IUI

  • Less invasive than IVF
  • Usually lower cost per cycle
  • Does not require egg retrieval
  • Short procedure
  • May be appropriate for selected infertility diagnoses

Limitations of IUI

  • Not suitable for every infertility condition
  • Requires suitable sperm parameters
  • Usually requires at least one functioning fallopian tube
  • Success can be lower per cycle than IVF
  • Several cycles may be needed
  • Ovarian stimulation can increase the risk of multiple pregnancy

Benefits and Limitations of IVF

Potential Benefits of IVF

  • Can bypass blocked fallopian tubes
  • Useful for many forms of infertility
  • Allows fertilisation to occur in the laboratory
  • Embryos can be frozen for future use
  • ICSI can be used when indicated
  • Genetic testing may be considered in selected cases
  • Can provide a treatment pathway when other fertility treatments have failed

Limitations of IVF

  • More invasive than IUI
  • Usually more expensive
  • Requires ovarian stimulation and egg retrieval
  • Takes more time and monitoring
  • Does not guarantee pregnancy
  • May involve additional procedures and costs

IVF vs IUI: Which One Is Better?

There is no universal answer to “Which is better, IUI or IVF?”

The more appropriate question is:

Which treatment is more suitable for my fertility diagnosis?

IUI may be a reasonable option when the fertility factors are relatively favourable and less invasive treatment is appropriate.

IVF may be more appropriate when there are significant tubal, sperm, ovarian, age-related or other fertility factors, or when previous treatments have not worked.

For some couples, starting with IUI may be appropriate. For others, moving directly to IVF may be discussed.

The WHO’s 2025 infertility guideline also emphasises evidence-based, patient-centred fertility care and progression from simpler to more complex treatment according to the individual’s clinical situation. (who.int)


IVF vs IUI: How Does a Doctor Decide?

Before recommending IUI or IVF, your fertility specialist may assess:

Female Partner

  • Age
  • Menstrual cycle
  • Ovulation
  • Ovarian reserve
  • Fallopian tubes
  • Uterus
  • Previous pregnancies
  • Previous fertility treatment

Male Partner

  • Semen analysis
  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Previous fertility history
  • Relevant medical conditions

Couple

  • Duration of infertility
  • Cause of infertility
  • Previous treatment outcomes
  • Genetic considerations
  • Financial and practical preferences
  • Time available for treatment

This assessment helps the fertility team develop an individualised treatment plan.


Can IUI Be Converted to IVF?

Yes. Fertility treatment is often progressive.

A couple may begin with IUI when it is clinically appropriate. If pregnancy does not occur after an appropriate number of cycles, or if new information changes the diagnosis, the fertility specialist may recommend IVF.

For unexplained infertility, ASRM guidance has historically supported a limited course of stimulated IUI followed by IVF when unsuccessful, while age and individual circumstances can influence whether IVF is considered earlier. (asrm.org)


IVF vs IUI Frequently Asked Questions

Is IUI better than IVF?

Neither treatment is universally better. IUI is less invasive and generally less expensive, while IVF can be appropriate for a broader range of infertility conditions. The right treatment depends on the couple’s diagnosis and circumstances.

Is IVF more successful than IUI?

IVF generally has a higher pregnancy potential per treatment cycle than IUI in many clinical situations, but success varies significantly with age, diagnosis and other factors. Comparing percentages without considering the patient population can be misleading.

Is IUI cheaper than IVF?

Generally, yes. IUI usually has a lower per-cycle cost because it does not involve egg retrieval or laboratory embryo development. However, total treatment costs vary.

How many IUI cycles should I try before IVF?

There is no single number for every patient. The decision depends on age, diagnosis, ovarian reserve, sperm parameters and previous treatment. In selected cases of unexplained infertility, several stimulated IUI cycles may be considered before IVF. (asrm.org)

Can IUI work with low sperm count?

It may be possible in selected cases, depending on the severity of the sperm abnormality and the number of motile sperm available after processing. Severe male-factor infertility may require IVF with ICSI.

Can IUI work with blocked fallopian tubes?

IUI generally requires at least one functioning fallopian tube because fertilisation still occurs inside the reproductive tract. If both tubes are blocked, IVF may be considered.

Is IVF painful?

IVF involves more procedures than IUI, including injections and egg retrieval. Pain and discomfort vary between individuals, and clinics use appropriate pain relief or sedation for egg retrieval.

Does IVF guarantee pregnancy?

No. IVF can provide an effective fertility treatment option, but it does not guarantee pregnancy or a live birth.

Which is better for older women: IUI or IVF?

Age is an important factor in fertility treatment planning. Depending on age, ovarian reserve, diagnosis and time available for treatment, a fertility specialist may discuss IVF sooner rather than spending multiple cycles on IUI.


IVF vs IUI in Srinagar

If you are searching for IVF vs IUI in Srinagar, the first step is to understand why pregnancy has not occurred.

At Imprimis IVF & Fertility Centre, Srinagar, a fertility specialist can evaluate both partners and discuss whether IUI, IVF or another fertility treatment is appropriate.

The evaluation may include assessment of ovulation, ovarian reserve, fallopian tubes, semen parameters and other relevant fertility factors.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

Treatment recommendations should be based on an individual medical evaluation rather than an online comparison.


Final Thoughts: IVF vs IUI

IVF and IUI are not competing treatments where one is always better than the other.

IUI is a less invasive fertility treatment that may be suitable for selected couples. IVF is a more involved treatment that can address a wider range of fertility problems.

The most appropriate option depends on your:

  • Age
  • Fertility diagnosis
  • Ovarian reserve
  • Ovulation
  • Fallopian tube status
  • Sperm parameters
  • Previous treatment
  • Overall reproductive health

If you are unsure whether IUI or IVF is right for you, consult a qualified fertility specialist for an individual assessment.


Medical Reviewer & Editorial Information

Medical Reviewer: Imprimis IVF

Last Updated: September 19, 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar

Medical Disclaimer: This article is intended for general educational purposes and does not replace professional medical advice, diagnosis or treatment. Fertility treatment should be selected after an appropriate evaluation by a qualified fertility specialist. Individual treatment outcomes vary.

Medical References: World Health Organization (WHO) 2025 Guideline for the Prevention, Diagnosis and Treatment of Infertility; American Society for Reproductive Medicine (ASRM) guidance; European Society of Human Reproduction and Embryology (ESHRE) guidance.

Recurrent Pregnancy Loss: Causes, Diagnosis & Treatment

Experiencing a miscarriage can be emotionally and physically difficult. While miscarriage is relatively common, recurrent pregnancy loss (RPL) requires medical evaluation to understand whether an underlying cause may be contributing to repeated pregnancy losses.

Recurrent pregnancy loss is a distinct reproductive health condition and is different from infertility. According to the latest American Society for Reproductive Medicine (ASRM) guidance, recurrent pregnancy loss is defined as two or more spontaneous pregnancy losses, excluding confirmed molar or ectopic pregnancies. The losses do not necessarily have to occur consecutively.

Many miscarriages, particularly those occurring early in pregnancy, are related to chromosomal abnormalities in the embryo. The likelihood of chromosomal abnormalities also increases with maternal age. However, recurrent pregnancy loss can have several possible causes, and sometimes no single cause is identified even after a detailed evaluation.

If you have experienced repeated miscarriages, consulting an experienced fertility specialist or obstetrician-gynaecologist can help determine whether further testing or treatment is appropriate.

What Is Recurrent Pregnancy Loss?

Recurrent pregnancy loss (RPL) refers to repeated spontaneous pregnancy losses.

Current ASRM guidance defines RPL as the spontaneous loss of two or more pregnancies, excluding confirmed molar and ectopic pregnancies. Pregnancy losses do not have to be consecutive for evaluation to be considered.

The term recurrent miscarriage is also commonly used. Older medical literature may use the term recurrent abortion, but “recurrent pregnancy loss” is generally preferred for patient-focused medical communication.

Recurrent pregnancy loss can be associated with genetic, anatomical, hormonal, metabolic, immune-related and other factors. In some couples, no clear cause is identified.


What Causes Recurrent Pregnancy Loss?

Causes Recurrent Pregnancy Loss

There is no single cause of recurrent miscarriage. A detailed evaluation may consider several factors involving the embryo, chromosomes, uterus, hormones, metabolism, and the health of both partners.

1. Chromosomal Abnormalities

Chromosomal abnormalities are an important cause of early pregnancy loss.

Approximately 50%–60% of first-trimester miscarriages are associated with embryonic aneuploidy, and the likelihood of aneuploidy is strongly influenced by maternal age.

Most chromosomal abnormalities occur sporadically during egg or embryo development. In some cases, however, chromosome abnormalities involving one of the parents may contribute to recurrent pregnancy loss.

When possible, chromosome testing of miscarriage tissue may provide useful information during recurrent pregnancy loss evaluation. The latest ASRM guidance recommends chromosome analysis of pregnancy-loss tissue, when feasible, as an important part of evaluation.

2. Uterine Abnormalities

Problems affecting the structure of the uterus may contribute to pregnancy loss in some women.

These may include:

  • Uterine septum
  • Certain congenital uterine anomalies
  • Fibroids
  • Endometrial polyps
  • Intrauterine adhesions

Your fertility specialist may recommend imaging or other investigations based on your history and symptoms.

3. Antiphospholipid Syndrome

Antiphospholipid syndrome (APS) is an autoimmune condition associated with abnormal blood clotting and specific pregnancy complications.

APS is an established and potentially treatable cause of recurrent pregnancy loss. Testing may be recommended when a patient’s history suggests an increased risk.

Treatment for confirmed obstetric APS may include medications such as low-dose aspirin and heparin under specialist supervision. These medicines should not be started without medical advice. Current evidence does not support routinely prescribing aspirin or anticoagulants to everyone with recurrent pregnancy loss.

4. Thyroid and Metabolic Conditions

Certain medical conditions may be associated with pregnancy loss.

Depending on the individual’s history, evaluation may include conditions such as:

  • Thyroid disease
  • Diabetes
  • Other metabolic disorders

The latest ASRM guidance supports targeted assessment for conditions such as thyroid disease and diabetes when clinically appropriate.

5. Age-Related Factors

Maternal age is an important factor in miscarriage risk because chromosomal abnormalities in eggs and embryos become more common with increasing age.

This does not mean that pregnancy after 35 is impossible or necessarily unsuccessful. However, age should be considered when evaluating recurrent pregnancy loss and planning future pregnancy.

6. Other Factors

Depending on the clinical history, doctors may also consider:

  • Genetic factors
  • Certain anatomical conditions
  • Lifestyle factors
  • Chronic medical conditions
  • Previous pregnancy complications

Not every proposed cause of recurrent miscarriage has strong evidence. Current guidelines recommend targeted evaluation rather than routinely performing every available test.


Recurrent Pregnancy Loss Symptoms

Recurrent Pregnancy Loss Symptoms

Recurrent pregnancy loss itself does not usually have a specific set of symptoms between pregnancies. The main concern is repeated pregnancy loss.

During an individual miscarriage, symptoms may include:

  • Vaginal bleeding or spotting
  • Lower abdominal or pelvic cramping
  • Back pain
  • Passing tissue or clots
  • Decreasing pregnancy symptoms

However, these symptoms do not always mean that a miscarriage is occurring. Bleeding and abdominal pain during pregnancy can have several causes.

Seek urgent medical care if you experience heavy bleeding, severe abdominal or pelvic pain, dizziness, fainting, fever or other concerning symptoms during pregnancy.


When Should You See a Doctor for Recurrent Miscarriage?

If you have experienced two or more pregnancy losses, it is reasonable to discuss recurrent pregnancy loss evaluation with a qualified obstetrician-gynaecologist or fertility specialist. Current ASRM guidance recognises RPL after two spontaneous pregnancy losses.

You should especially seek specialist advice if:

  • You have had two or more miscarriages.
  • You have experienced a second-trimester pregnancy loss.
  • You have irregular menstrual cycles.
  • You have a known uterine abnormality.
  • You have a history suggesting autoimmune or metabolic disease.
  • You or your partner has a known genetic condition.
  • You have been trying to conceive again after repeated pregnancy loss.

Tests for Recurrent Pregnancy Loss

There is no single test that can identify every cause of recurrent pregnancy loss.

Your doctor may recommend targeted investigations based on your pregnancy history, age, previous test results and other health factors.

Common Tests

Depending on the individual situation, evaluation may include:

Genetic Testing

Chromosome testing of pregnancy-loss tissue can help determine whether a chromosomal abnormality contributed to the miscarriage.

In selected cases, parental genetic testing may also be considered.

Uterine Evaluation

Tests used to assess the uterus may include:

The appropriate test depends on the suspected condition.

Antiphospholipid Antibody Testing

Testing for antiphospholipid syndrome may be recommended when clinically appropriate.

Thyroid and Metabolic Assessment

Your doctor may recommend blood tests to assess thyroid function, diabetes or other metabolic conditions depending on your medical history.

Evaluation of Other Health Factors

A detailed medical, reproductive and family history can help determine whether additional investigations are required.


Can Recurrent Pregnancy Loss Be Prevented?

There is no guaranteed way to prevent every miscarriage because many early pregnancy losses are caused by chromosomal abnormalities that occur during embryo development.

However, addressing treatable medical conditions and maintaining good preconception health may support a healthy pregnancy.

Steps That May Support a Healthy Pregnancy

Maintain a Healthy Lifestyle

Aim for a balanced diet, regular physical activity and a healthy weight appropriate for your individual circumstances.

Avoid Smoking and Tobacco

Smoking is associated with adverse reproductive and pregnancy outcomes. Avoid tobacco and exposure to tobacco smoke when planning pregnancy.

Avoid Alcohol During Pregnancy

Alcohol should be avoided during pregnancy.

Review Medications Before Pregnancy

Speak with your doctor before starting, stopping or changing any medication while trying to conceive or during pregnancy.

Manage Existing Health Conditions

Conditions such as diabetes and thyroid disease should be appropriately evaluated and managed before and during pregnancy.

Take Recommended Prenatal Supplements

Your doctor may recommend folic acid and other prenatal supplements based on your individual needs.

Attend Preconception Care

A preconception consultation can help identify medical or reproductive factors that may need attention before another pregnancy.


Recurrent Pregnancy Loss Treatment

Recurrent Pregnancy Loss Treatment

Treatment for Recurrent Miscarriage depends on the underlying cause.

There is no single treatment that works for every couple.

After evaluation, treatment may involve:

  • Management of thyroid or metabolic conditions
  • Treatment of confirmed antiphospholipid syndrome
  • Treatment of certain uterine abnormalities
  • Genetic counselling
  • Fertility treatment where appropriate
  • Psychological and emotional support

Current guidelines emphasise evidence-based, targeted treatment and caution against the routine use of tests or therapies that have not demonstrated clear benefit.


Treatment for Uterine Abnormalities

If a uterine abnormality is identified and is considered relevant to the pregnancy losses, treatment may sometimes be recommended.

Depending on the condition, treatment can include procedures such as hysteroscopic surgery.

For example, a uterine septum may be treated surgically in selected patients after appropriate evaluation and counselling.

The decision to operate should be individualised rather than based solely on an ultrasound finding.


Treatment for Antiphospholipid Syndrome

Women with confirmed obstetric antiphospholipid syndrome may benefit from specific treatment during pregnancy.

Depending on the clinical situation, a specialist may prescribe low-dose aspirin and heparin or another appropriate anticoagulant.

These medications are not appropriate for everyone with recurrent miscarriage or for people without a confirmed indication. They can have important side effects and should only be used under medical supervision.


Can IVF Help With Recurrent Pregnancy Loss?

IVF is not automatically required for Recurrent Miscarriage

Many couples with recurrent pregnancy loss can achieve a successful pregnancy without IVF, depending on the cause, age and other fertility factors.

However, IVF may be considered when there is another indication for assisted reproductive treatment or in selected couples where genetic factors are relevant.

IVF allows eggs to be fertilised in the laboratory and embryos to be transferred to the uterus.

IVF and Genetic Testing

In selected cases, preimplantation genetic testing (PGT) may be discussed when there is a known genetic or chromosomal indication.

However, PGT is not a universal treatment for recurrent pregnancy loss. The benefits, limitations, cost and possibility of obtaining a suitable embryo should be discussed with a fertility specialist.

Current ASRM guidance notes that evidence concerning PGT-A in recurrent pregnancy loss is still nuanced, and treatment should be individualised rather than offered routinely to every patient with RPL.


Chances of a Successful Pregnancy

Experiencing recurrent miscarriage does not mean that a future healthy pregnancy is impossible.

The outcome depends on several factors, including:

  • Maternal age
  • Number and timing of previous pregnancy losses
  • Chromosomal findings
  • Underlying medical conditions
  • Uterine factors
  • Whether a treatable cause is identified

Importantly, many cases remain unexplained even after evaluation. The latest ASRM guidance reports that 50%–80% of patients with unexplained recurrent pregnancy loss may go on to have a successful pregnancy, depending on individual circumstances.

Your individual prognosis should be discussed with your fertility specialist rather than estimated from a general percentage.


Emotional Support After Recurrent Miscarriage

Recurrent Miscarriage can be emotionally challenging for both partners.

Feelings of sadness, anxiety, grief, frustration or fear during a subsequent pregnancy are understandable.

Psychological support and counselling are an important part of recurrent pregnancy loss care. Current ASRM guidance specifically recommends emotional support for patients and couples experiencing RPL.

Seeking professional support does not mean that your concerns are being dismissed. Emotional wellbeing is an important part of reproductive healthcare.


Recurrent Pregnancy Loss Treatment in Srinagar

If you are looking for recurrent pregnancy loss treatment in Srinagar, an evaluation by a fertility specialist can help identify possible causes and determine whether further investigations or treatment are appropriate.

At Imprimis IVF & Fertility Centre, Srinagar, couples can seek fertility evaluation and discuss recurrent miscarriage, infertility and available fertility treatment options.

The centre provides fertility-related services including infertility evaluation, IUI and IVF treatment.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

If you have experienced repeated miscarriages, consult a qualified fertility specialist before starting medicines or fertility treatment on your own.


Frequently Asked Questions

What is recurrent pregnancy loss?

Recurrent pregnancy loss is generally defined as two or more spontaneous pregnancy losses. Current ASRM guidance does not require the losses to be consecutive.

Is recurrent abortion the same as recurrent miscarriage?

The terms may be used to describe repeated pregnancy loss, but recurrent pregnancy loss (RPL) is the preferred modern clinical terminology for patient education.

How many miscarriages are considered recurrent pregnancy loss?

Current ASRM guidance defines recurrent pregnancy loss as two or more spontaneous pregnancy losses.

What is the most common cause of recurrent miscarriage?

Chromosomal abnormalities are a major cause of early pregnancy loss. However, recurrent pregnancy loss can have several possible causes, and some cases remain unexplained.

Can PCOS cause recurrent miscarriage?

PCOS may be associated with certain reproductive and metabolic risks, but recurrent pregnancy loss should not automatically be attributed to PCOS. A proper medical evaluation is needed to identify possible contributing factors.

Can thyroid problems cause recurrent miscarriage?

Thyroid disorders can affect reproductive and pregnancy health. Appropriate thyroid assessment may be part of the evaluation of recurrent pregnancy loss when clinically indicated.

Can recurrent pregnancy loss be treated?

Yes, in some cases an underlying cause can be identified and treated. However, there is no single treatment for all cases of recurrent pregnancy loss.

Is IVF necessary after recurrent miscarriage?

No. IVF is not automatically required after recurrent miscarriage. It may be considered when there is another indication for IVF or in selected situations involving genetic or fertility factors.

Can IVF prevent miscarriage?

IVF cannot guarantee that miscarriage will be prevented. In selected cases, IVF with appropriate genetic testing may be discussed, but it is not a universal treatment.

Should I take aspirin or heparin after repeated miscarriages?

Do not start aspirin or heparin without medical advice. These medications may be appropriate for selected patients, particularly those with confirmed antiphospholipid syndrome, but they are not routinely recommended for everyone.

Can I have a healthy pregnancy after recurrent miscarriage?

Yes. Many people with recurrent pregnancy loss subsequently have a successful pregnancy. Your individual chances depend on factors such as age, medical history, previous pregnancy losses and whether an underlying cause is identified.


Take the Next Step After Recurrent Pregnancy Loss

Experiencing repeated pregnancy loss can be difficult, but it does not mean that a successful pregnancy is impossible.

The right approach is to identify possible causes, treat conditions that can be addressed and develop an individualised pregnancy or fertility plan.

If you have experienced two or more pregnancy losses, consider speaking with a qualified fertility specialist or obstetrician-gynaecologist for appropriate evaluation.

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 979775611

Medical Reviewer: Imprimis IVF & Fertility Centre Team

Last Updated: September 19, 2026