IVF success stories bring hope and confidence to couples struggling with infertility across India. At Imprimis IVF Centre, we proudly share real patient journeys that highlight our expertise, advanced fertility treatments, and high IVF success rates. These inspiring stories showcase how couples have overcome challenges like PCOS, low AMH, male infertility, tubal blockage, and repeated IVF failures to achieve their dream of parenthood.

Our IVF success stories in India reflect the dedication of our experienced fertility specialists, state-of-the-art IVF labs, and personalized treatment plans. Whether it’s first-time IVF success, twin pregnancy, or conception after years of infertility, each story is a testament to our commitment to delivering positive outcomes.

Many patients searching for the best IVF centre in India look for genuine results before starting treatment. These real-life success stories help you understand the treatment process, patient experience, and success rates at Imprimis IVF. From IUI and IVF to ICSI and advanced fertility solutions, our centre offers comprehensive care tailored to individual needs.

If you are facing infertility issues, these stories will inspire you to take the next step with confidence. At Imprimis IVF Centre, we combine cutting-edge technology with compassionate care to ensure the best possible results.

Explore our IVF success stories and discover why we are considered one of the most trusted fertility centres in India. Your journey to parenthood can begin here—with hope, trust, and proven success

IVF Diet Chart: Foods to Eat and Avoid During IVF Treatment

IVF Diet Chart: Starting IVF treatment can bring many questions, including one of the most common: What should I eat during IVF?

An IVF diet chart cannot guarantee a successful IVF cycle, and there is no single food that can make an embryo implant or increase IVF success on its own. However, eating a balanced, nutritious diet can support overall health, provide essential nutrients, and help you maintain a healthy lifestyle before and during fertility treatment.

Research on specific dietary patterns and IVF outcomes remains mixed. Some studies have reported associations between healthier dietary patterns and IVF outcomes, while others have not found a consistent benefit. Therefore, diet should be viewed as part of overall preconception and fertility care rather than a replacement for medical treatment.

What Is an IVF Diet Chart?

An IVF diet chart is a practical eating plan designed to help you maintain good nutrition during fertility treatment.

Instead of focusing on a “miracle IVF food,” the goal should be to include a variety of:

  • Vegetables and leafy greens
  • Fresh fruits
  • Whole grains
  • Beans, lentils and other legumes
  • Nuts and seeds
  • Healthy sources of protein
  • Healthy fats
  • Dairy or suitable alternatives
  • Adequate fluids

A healthy dietary pattern can support general health, while fertility treatment addresses the specific medical causes of infertility. The World Health Organisation also recommends healthy lifestyle measures, including a healthy diet and physical activity, for people planning or attempting pregnancy.

Does Diet Increase IVF Success Rate?

This is one of the most searched questions about IVF nutrition.

The short answer is: no specific IVF diet has been proven to guarantee IVF success.

Studies investigating Mediterranean-style diets, fertility diets and individual nutrients have produced inconsistent findings in people undergoing assisted reproductive treatment. Therefore, it is not appropriate to promise that a particular food, drink or diet will improve implantation, egg quality or live birth rates.

However, maintaining a nutritious diet can help support overall health during IVF and pregnancy planning.

Your IVF outcome depends on several factors, including:

  • Age
  • Ovarian reserve
  • Egg and embryo factors
  • Sperm quality
  • Uterine and tubal factors
  • Underlying medical conditions
  • Previous fertility treatment
  • Embryo genetics in selected cases
  • The specific IVF treatment plan

For more information, read our guide to [IVF Success Rate].

IVF Diet Chart: Foods to Eat During IVF Treatment

IVF Diet Chart


There is no mandatory list of “fertility foods.” Instead, aim for a varied and minimally processed diet.

1. Protein-Rich Foods

Protein is an important part of a balanced diet and is needed for tissue growth and repair.

Good choices include:

  • Eggs, when fully cooked
  • Milk and yoghurt
  • Paneer in moderate portions
  • Dal and lentils
  • Chickpeas and kidney beans
  • Soy and tofu
  • Nuts and seeds
  • Chicken and other lean meats
  • Well-cooked fish

There is no universal requirement that every woman undergoing IVF consume exactly 60 grams of protein per day. Protein requirements vary according to body size, activity level, pregnancy status, and medical needs.

2. Green Leafy Vegetables

Include vegetables such as:

  • Spinach
  • Methi
  • Broccoli
  • Cabbage
  • Beans
  • Peas
  • Capsicum
  • Carrots
  • Other seasonal vegetables

Leafy greens also provide folate, fibre and several vitamins and minerals.

3. Whole Grains and High-Fibre Foods

Choose whole or minimally processed carbohydrates more often, such as:

  • Oats
  • Whole-wheat roti
  • Brown rice
  • Millets
  • Quinoa
  • Barley
  • Whole-grain bread

Legumes such as chickpeas, rajma, peas and lentils can also provide fibre and plant-based protein.

4. Fruits

Fresh fruits can be part of a healthy IVF diet.

Options include:

  • Apples
  • Oranges
  • Guava
  • Berries
  • Pomegranate
  • Bananas
  • Papaya
  • Pears
  • Seasonal fruits

There is no strong evidence that one particular fruit, including pineapple, guarantees implantation or improves IVF success. Choose fruits for overall nutrition rather than as a fertility treatment.

5. Healthy Fats

Include moderate amounts of unsaturated fats from foods such as:

  • Nuts
  • Seeds
  • Avocado
  • Olive oil
  • Groundnut oil
  • Mustard oil
  • Fatty fish that is low in mercury

Healthy fats can form part of a balanced dietary pattern, but they should not be viewed as an IVF success booster.

6. Folic Acid and Folate-Rich Foods

Folic acid is particularly important before conception because it helps reduce the risk of neural tube defects.

Women planning pregnancy are generally advised to take 400 micrograms (mcg) of folic acid daily, unless their healthcare professional recommends a different dose.

Food sources of folate include:

  • Green leafy vegetables
  • Beans
  • Lentils
  • Peas
  • Citrus fruits
  • Fortified grains

Your fertility specialist may recommend a prenatal vitamin based on your individual nutritional requirements.

7. Iron-Rich Foods

Iron is essential for making haemoglobin and supporting normal blood function.

Food sources include:

  • Lentils
  • Beans
  • Spinach and other leafy greens
  • Sesame seeds
  • Pumpkin seeds
  • Meat and poultry
  • Iron-fortified cereals

The required amount of iron varies by life stage and pregnancy status. Do not take high-dose iron supplements unless advised by your doctor or after an assessment of your iron status.

8. Calcium and Vitamin D

Calcium and vitamin D are important for overall health and are particularly important during pregnancy.

Dietary sources can include:

  • Milk
  • Curd/yoghurt
  • Fortified dairy alternatives
  • Paneer
  • Eggs
  • Certain fish

Vitamin D deficiency is relatively common, but taking high-dose vitamin D without testing or medical advice is not recommended.

9. Low-Mercury Fish

You do not need to avoid all seafood during IVF.

Cooked, low-mercury fish can be part of a healthy diet. However, certain fish contain higher levels of mercury and should be avoided or limited, particularly during pregnancy. ACOG advises avoiding fish such as shark, swordfish, king mackerel, marlin and bigeye tuna during pregnancy.

Choose fish according to current pregnancy food-safety recommendations and local guidance.

Hydration During IVF

Adequate hydration is important for general health.

Drink water regularly throughout the day, and increase your intake as needed due to heat, exercise, or other circumstances.

However, there is no established evidence that drinking a specific number of glasses of water thickens the uterine lining or directly improves embryo implantation.

If you have a medical condition that requires fluid restriction, follow your doctor’s instructions.

IVF Diet Chart: What to Avoid or Limit

Foods to avoid during IVF Treatment

1. Alcohol

It is safest to avoid alcohol when undergoing IVF and when pregnancy is possible.

Alcohol can have adverse effects during pregnancy, and there is no established safe level of alcohol consumption during pregnancy.

2. Smoking and Tobacco

Avoid smoking and exposure to secondhand smoke.

Tobacco use is associated with poorer reproductive outcomes, and evidence indicates that smoking can negatively affect assisted reproductive treatment outcomes.

3. Excessive Caffeine

You do not necessarily need to eliminate caffeine entirely, but keeping intake below 200 mg per day is a commonly recommended safety limit during pregnancy. Remember that caffeine is also found in tea, chocolate, cola and energy drinks—not only coffee.

If you are unsure about the caffeine content of your usual drinks, ask your fertility specialist or dietitian.

4. Raw or Undercooked Eggs

Avoid raw or undercooked eggs due to the risk of foodborne illness.

Be particularly careful with foods prepared using raw eggs, such as some homemade mayonnaise, mousse and certain desserts.

5. Unpasteurized Milk and Dairy Products

Choose pasteurised milk and dairy products.

Unpasteurized products can carry bacteria that may cause serious foodborne infections during pregnancy.

6. Raw or Undercooked Meat and Seafood

Cook meat, poultry, eggs and seafood thoroughly.

Avoid raw fish and shellfish because they can increase the risk of foodborne illness.

7. High-Mercury Fish

Avoid fish known to contain high levels of mercury, particularly once pregnancy is established.

Your fertility team can provide guidance on safe seafood choices.

8. Highly Processed Foods and Excess Added Sugar

You do not need to eliminate all packaged foods from your diet.

However, try to limit frequent consumption of:

  • Sugary beverages
  • Sweets
  • Cakes and pastries
  • Highly processed snacks
  • Deep-fried foods
  • Processed meats
  • Foods high in added sugar and saturated fat

A balanced diet is more sustainable than extreme food restrictions.

Simple 1-Day IVF Diet Chart

The following is a general example, not a personalised medical diet.

Time Example
Morning Water + prescribed prenatal/folic acid supplement
Breakfast Vegetable oats/poha/upma + fully cooked egg or yoghurt
Mid-morning One seasonal fruit + a small handful of nuts
Lunch Roti/brown rice + dal + vegetables + curd
Evening Roasted chana/makhana or fruit + unsweetened tea
Dinner Roti/millet + cooked vegetables + dal/paneer/chicken/fish
Bedtime Milk or suitable alternative, if tolerated

Your calorie and nutrient requirements may be different. Patients with PCOS, diabetes, thyroid disorders, anaemia, obesity, underweight, food allergies or other medical conditions may need an individualised plan.

Is Five Meals a Day Necessary During IVF?

No.

There is no universal requirement to eat five meals every day during IVF.

Some people prefer smaller, frequent meals because they experience nausea, bloating or reduced appetite during treatment. Others are comfortable with three main meals and one or two snacks.

The important point is to maintain adequate nutrition and follow the dietary advice given by your healthcare team.

Can I Eat Pineapple During IVF?

Yes, pineapple can be part of a normal, balanced diet if you tolerate it.

However, there is no strong evidence that pineapple or its core can improve embryo implantation or increase IVF success.

The same principle applies to other foods sometimes promoted online as “implantation foods.” They can be nutritious, but they should not be presented as fertility treatments.

What Should I Eat After Embryo Transfer?

After embryo transfer, you generally do not need a special “implantation diet.”

Focus on:

  • Balanced meals
  • Adequate protein
  • Vegetables and fruits
  • Whole grains
  • Healthy fats
  • Adequate fluids
  • Folic acid/prenatal supplements as prescribed
  • Safe food preparation

Avoid alcohol, smoking and unsafe foods such as raw or undercooked animal products and high-mercury fish.

Continue your prescribed IVF medications exactly as instructed.

For more information, see [Embryo Transfer] and [IVF Treatment in Srinagar].

Can Diet Improve Egg Quality During IVF?

Diet provides the nutrients required for normal bodily functions, but no specific food or diet has been proven to “repair” or guarantee better egg quality.

Egg quality is influenced by several factors, including age and ovarian biology. A healthy lifestyle can support overall reproductive health, but it should not be promoted as a guaranteed way to improve egg quality.

If you have concerns about ovarian reserve or egg quality, discuss them with your fertility specialist.

Do I Need Supplements During IVF?

Not everyone undergoing IVF needs the same supplements.

Your fertility specialist may recommend supplements based on your medical history, blood tests, dietary intake and pregnancy-planning needs.

Commonly discussed nutrients include:

  • Folic acid
  • Iron
  • Vitamin D
  • Vitamin B12
  • Calcium

Do not start high-dose vitamins, minerals or herbal fertility supplements without medical advice.

IVF Diet and Lifestyle: Other Important Tips

Diet is only one part of preparing for IVF.

Take IVF Medicines on Time

Follow your fertility specialist’s instructions for hormonal injections, tablets and other medications.

Do not change the dose or stop medication without consulting your treatment team.

Stay Physically Active as Advised

Regular physical activity can support overall well-being. However, your activity level may need to be modified during ovarian stimulation or after specific procedures.

Always follow your fertility team’s instructions.

Avoid Smoking and Recreational Drugs

Smoking, tobacco and recreational drug use can negatively affect reproductive health. Tobacco cessation is particularly important when planning pregnancy.

Prioritise Sleep and Emotional Wellbeing

IVF can be physically and emotionally demanding.

Good sleep, emotional support, counselling when needed and realistic expectations can help you manage the treatment journey.

You do not need to maintain “constant positivity” for IVF to be successful. Treatment outcomes are not determined by whether a patient feels positive or anxious.

Is Strict Bed Rest Required After Embryo Transfer?

Routine strict bed rest is generally not required after embryo transfer.

Your fertility clinic may provide specific instructions about activity based on your procedure and medical circumstances. Follow those instructions rather than remaining in bed unnecessarily.

If you experience significant pain, heavy bleeding, breathing difficulty, severe abdominal swelling or other concerning symptoms after treatment, contact your fertility clinic promptly.

Can an IVF Diet Guarantee IVF Success?

No.

There is no diet, food, supplement or lifestyle change that can guarantee pregnancy or live birth through IVF.

IVF outcomes depend on multiple medical and biological factors. A healthy diet can support your overall health, but it should complement—not replace—evidence-based fertility treatment.

The WHO’s current infertility guidance supports evidence-based, patient-centred fertility care alongside healthy lifestyle measures.

Frequently Asked Questions About IVF Diet

What is the best diet during IVF treatment?

A balanced diet containing vegetables, fruits, whole grains, legumes, healthy protein sources and unsaturated fats is a practical approach. Your individual diet should be adjusted for your medical and nutritional needs.

Which foods should I avoid during IVF?

Avoid alcohol and smoking. Also avoid or limit foods with food-safety risks, including raw or undercooked eggs, meat and seafood, unpasteurized products and high-mercury fish.

Can I drink tea or coffee during IVF?

Moderate caffeine intake may be acceptable, but during pregnancy and when pregnancy is possible, keeping caffeine below 200 mg per day is commonly advised.

Can I eat fish during IVF?

Yes. Seafood does not need to be completely eliminated. Choose properly cooked, low-mercury fish and avoid high-mercury varieties according to pregnancy food-safety recommendations.

Is pineapple good for IVF implantation?

Pineapple can be part of a healthy diet, but there is no strong evidence that eating pineapple increases embryo implantation or IVF success.

Should I take folic acid during IVF?

Women planning pregnancy are generally advised to take 400 mcg of folic acid daily, unless their doctor recommends another dose.

Do I need five meals a day during IVF?

No. There is no universal requirement to eat five meals daily. Choose a meal pattern that meets your nutritional needs and feels comfortable for you.

Can an IVF diet improve my chances of pregnancy?

A nutritious diet supports general health, but no specific IVF diet has been proven to guarantee pregnancy or live birth. IVF success depends on many individual factors.

Final Takeaway: IVF Diet Chart

Following a healthy IVF diet chart can help you maintain good nutrition throughout fertility treatment, but there is no miracle food that guarantees implantation or IVF success.

Focus on a varied diet with vegetables, fruits, whole grains, legumes, lean proteins, nuts, seeds, and appropriate sources of healthy fats. Take folic acid and other supplements only as recommended by your healthcare professional.

Most importantly, avoid smoking and recreational drugs, avoid alcohol, keep caffeine moderate, and follow pregnancy food-safety precautions.

Your fertility specialist can help you create an IVF nutrition plan based on your medical history, treatment protocol and nutritional requirements.

If you are planning IVF treatment in Srinagar, you can consult the fertility team at Imprimis IVF & Fertility Centre, Srinagar for an individualised fertility assessment and treatment plan.

Medical Review & Clinic Information

Medical Reviewer: Imprimis IVF Team
Last Updated: September 19, 2026
Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014

Medical Disclaimer: This article is intended for educational purposes and should not replace personalised medical advice, diagnosis or treatment. Dietary requirements during IVF can vary considerably. Consult your fertility specialist or qualified dietitian before making significant dietary or supplement changes.

IVF vs IUI: Which Fertility Treatment Is Right for You?

When you’re trying to conceive and fertility treatment has become part of your journey, one question often comes up: IVF vs IUI—which is better?

The answer is not the same for every couple.

Intrauterine insemination (IUI) and in vitro fertilisation (IVF) are different fertility treatments used for different clinical situations. IUI is generally less invasive and less expensive, while IVF is a more advanced treatment in which eggs are retrieved and fertilised in a laboratory before an embryo is transferred to the uterus.

The choice between IUI and IVF depends on several factors, including:

  • Age of the female partner
  • Duration of infertility
  • Cause of infertility
  • Ovulation status
  • Fallopian tube condition
  • Sperm count and motility
  • Ovarian reserve
  • Previous fertility treatments
  • Other medical conditions
  • Patient preferences and treatment goals

There is therefore no universal answer to “IVF vs IUI, which is better?” A fertility specialist can recommend an appropriate treatment after evaluating both partners.

IVF vs IUI: Quick Comparison

Factor IUI IVF
Full form Intrauterine Insemination In Vitro Fertilisation
Where fertilisation occurs Inside the reproductive tract In a laboratory
Egg retrieval No Yes
Embryo created in laboratory No Yes
Procedure complexity Less invasive More involved
Typical treatment cost Lower Higher
Treatment duration Usually shorter Usually longer
Useful for Selected infertility cases A wider range of infertility conditions
Multiple pregnancy risk Can increase with ovarian stimulation Can be reduced with single embryo transfer
Treatment choice Depends on diagnosis Depends on diagnosis

The table is a general comparison. Your fertility specialist may recommend a different approach depending on your individual medical circumstances.


What Is IUI?

IUI (Intrauterine Insemination) is a fertility treatment in which specially prepared sperm are placed directly inside the uterus around the time of ovulation.

The aim is to place a higher concentration of motile sperm closer to the fallopian tubes, where fertilisation can occur naturally.

IUI may be performed during a natural ovulatory cycle or together with medicines that stimulate ovulation, depending on the patient’s fertility diagnosis.

How Does IUI Work?

A typical IUI cycle may involve:

  1. Monitoring the menstrual cycle and ovulation.
  2. Using fertility medicines when clinically appropriate.
  3. Monitoring follicular development through ultrasound.
  4. Preparing a semen sample in the laboratory.
  5. Placing the prepared sperm into the uterus using a thin catheter.
  6. Monitoring for pregnancy after the procedure.

The actual insemination procedure is usually brief and does not generally require anaesthesia.

IUI does not involve egg retrieval or laboratory fertilisation.


What Is IVF?

IVF (In Vitro Fertilisation) is an assisted reproductive technology in which eggs are retrieved from the ovaries and fertilised with sperm in a laboratory.

After fertilisation, embryos are cultured, and one or more embryos may be transferred into the uterus.

A typical IVF cycle may involve:

  1. Ovarian stimulation
  2. Ultrasound and hormone monitoring
  3. Trigger medication when appropriate
  4. Egg retrieval
  5. Fertilisation with sperm
  6. Embryo culture
  7. Embryo transfer or freezing
  8. Pregnancy testing

Depending on the treatment plan, additional procedures such as ICSI, embryo freezing or genetic testing may be considered.


IVF vs IUI: What Is the Main Difference?

The biggest difference between IUI and IVF is where fertilisation occurs.

With IUI, sperm are placed inside the uterus and fertilisation must occur naturally within the reproductive tract.

With IVF, eggs are retrieved and fertilised in a laboratory. The resulting embryo is then transferred into the uterus.

This makes IVF a more involved treatment, but it also allows fertility specialists to address a broader range of fertility problems.


When Is IUI Recommended?

IUI may be considered for selected patients with:

Unexplained Infertility

IUI with ovarian stimulation is commonly used as an initial treatment approach for many couples with unexplained infertility.

Current guidance supports treatment pathways that may progress from less invasive approaches such as stimulated IUI to IVF when appropriate. (asrm.org)

Mild Male-Factor Infertility

IUI may be considered when sperm parameters are suitable for insemination after evaluation and processing.

The decision should not be based on a single semen analysis result.

Ovulation Problems

Women with ovulation disorders may sometimes undergo ovulation induction followed by IUI, depending on the underlying condition.

Selected Cases of Cervical-Factor Infertility

IUI can bypass the cervix by placing prepared sperm directly into the uterus.

Donor Sperm Treatment

IUI may also be used with donor sperm when clinically appropriate.

The suitability of IUI depends on factors such as ovarian function, ovulation, fallopian tube status, sperm quality and age.


When Is IVF Recommended?

IVF may be considered when there is a medical reason for a more advanced fertility treatment or when simpler treatments have not been successful.

Potential situations include:

Blocked or Severely Damaged Fallopian Tubes

Because IVF bypasses the fallopian tubes during fertilisation, it may be recommended when the tubes are blocked or significantly damaged.

Severe Male-Factor Infertility

IVF, often combined with ICSI when indicated, may be considered for severe sperm abnormalities or certain situations involving very low or absent sperm in the ejaculate.

Repeatedly Unsuccessful IUI

If appropriately selected IUI cycles do not result in pregnancy, a fertility specialist may recommend moving to IVF.

The number of IUI cycles before IVF is not identical for every patient.

Reduced Ovarian Reserve or Age-Related Fertility Decline

Age and ovarian reserve are important when deciding how quickly to progress through fertility treatment.

For some patients, proceeding directly to IVF may be discussed rather than spending several cycles on less effective treatments.

Endometriosis

Depending on the severity of endometriosis, age and other fertility factors, IVF may be considered.

Genetic or Chromosomal Indications

IVF may be used when preimplantation genetic testing is being considered for an appropriate medical indication.

Other Infertility Factors

IVF may also be recommended when multiple fertility factors are present or when other treatments are unlikely to provide a reasonable opportunity for pregnancy.


IVF vs IUI for Male Infertility

Male-factor infertility can influence the choice between IUI and IVF.

A semen analysis evaluates several important parameters, including:

  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Semen volume

IUI may be suitable when there is an adequate number of motile sperm after semen processing.

When sperm abnormalities are more severe, IVF with ICSI (Intracytoplasmic Sperm Injection) may be considered.

ICSI involves injecting a single sperm directly into an egg. It is particularly relevant when there is a clear male-factor indication or a history of fertilisation failure. Current ASRM guidance cautions against using ICSI routinely for non-male-factor infertility without a specific indication. (asrm.org)


IVF vs IUI for Female Infertility

Female fertility can be affected by the ovaries, fallopian tubes, uterus, hormones and age.

IUI may be considered when:

  • At least one fallopian tube is functioning
  • Ovulation can be achieved
  • Sperm parameters are suitable
  • There is no major uterine or tubal factor requiring IVF

IVF may be considered when:

  • Both fallopian tubes are blocked
  • Ovarian reserve is reduced
  • There are significant fertility factors
  • Previous IUI treatment has failed
  • Age or other circumstances make a more direct treatment approach appropriate

A complete fertility evaluation helps determine which treatment is appropriate.


IVF vs IUI Success Rate

One of the most common searches is “IUI vs IVF success rate.”

However, quoting one fixed success percentage can be misleading.

Success depends on factors such as:

  • Age
  • Diagnosis
  • Ovarian reserve
  • Egg and embryo quality
  • Sperm quality
  • Number of treatment attempts
  • Treatment protocol
  • Previous fertility history
  • Clinic and laboratory factors

IVF generally offers a higher chance of pregnancy per treatment cycle than IUI for many infertility situations, but the comparison should be made using the same outcome measure and patient population.

A clinic should therefore not promise a specific pregnancy or live-birth rate without considering the individual patient’s circumstances.

For patients with unexplained infertility, evidence-based guidelines support stimulated IUI as a treatment option before IVF in many cases, while also recognising that factors such as age and treatment history can change the treatment pathway. (asrm.org)


IVF vs IUI Cost

Cost is another important factor when comparing IUI vs IVF.

Generally, IUI costs less per treatment cycle because it does not involve egg retrieval, laboratory fertilisation or embryo culture.

IVF usually costs more because it involves ovarian stimulation, monitoring, egg retrieval, laboratory fertilisation, embryo culture and embryo transfer.

However, the total cost can vary significantly depending on:

  • Medicines and injections
  • Diagnostic tests
  • Number of treatment cycles
  • ICSI
  • Embryo freezing
  • Frozen embryo transfer
  • Genetic testing
  • Donor eggs or sperm
  • Other clinically indicated procedures

Therefore, rather than relying on a single online price, ask the fertility clinic for a personalised treatment estimate and clarify what is included.

For information about local treatment pricing, see our IVF treatment cost in Srinagar and IUI treatment in Srinagar pages.


IUI vs IVF: Which Is More Painful?

Both IUI and IVF can involve some discomfort, but the experience varies from person to person.

IUI

IUI is generally a short procedure. Some women experience mild cramping or temporary discomfort when the catheter is inserted.

IVF

IVF involves more steps and usually includes injectable ovarian stimulation and an egg-retrieval procedure.

Egg retrieval is generally performed with appropriate pain relief or sedation, in accordance with the clinic’s protocol.

Therefore, it is not accurate to describe IVF simply as “painful” or IUI as completely “painless.” Individual experiences vary.


IUI vs IVF: Treatment Duration

IUI usually involves fewer treatment steps than IVF.

An IUI cycle may involve:

  • Cycle monitoring
  • Ovulation induction when required
  • Trigger medication when appropriate
  • Sperm preparation
  • Insemination
  • Pregnancy testing

IVF generally involves more appointments and procedures, including ovarian stimulation, monitoring, egg retrieval, fertilisation and embryo transfer.

The total IVF timeline varies depending on the treatment protocol and whether a fresh or frozen embryo transfer is planned.


Benefits and Limitations of IUI

Potential Benefits of IUI

  • Less invasive than IVF
  • Usually lower cost per cycle
  • Does not require egg retrieval
  • Short procedure
  • May be appropriate for selected infertility diagnoses

Limitations of IUI

  • Not suitable for every infertility condition
  • Requires suitable sperm parameters
  • Usually requires at least one functioning fallopian tube
  • Success can be lower per cycle than IVF
  • Several cycles may be needed
  • Ovarian stimulation can increase the risk of multiple pregnancy

Benefits and Limitations of IVF

Potential Benefits of IVF

  • Can bypass blocked fallopian tubes
  • Useful for many forms of infertility
  • Allows fertilisation to occur in the laboratory
  • Embryos can be frozen for future use
  • ICSI can be used when indicated
  • Genetic testing may be considered in selected cases
  • Can provide a treatment pathway when other fertility treatments have failed

Limitations of IVF

  • More invasive than IUI
  • Usually more expensive
  • Requires ovarian stimulation and egg retrieval
  • Takes more time and monitoring
  • Does not guarantee pregnancy
  • May involve additional procedures and costs

IVF vs IUI: Which One Is Better?

There is no universal answer to “Which is better, IUI or IVF?”

The more appropriate question is:

Which treatment is more suitable for my fertility diagnosis?

IUI may be a reasonable option when the fertility factors are relatively favourable and less invasive treatment is appropriate.

IVF may be more appropriate when there are significant tubal, sperm, ovarian, age-related or other fertility factors, or when previous treatments have not worked.

For some couples, starting with IUI may be appropriate. For others, moving directly to IVF may be discussed.

The WHO’s 2025 infertility guideline also emphasises evidence-based, patient-centred fertility care and progression from simpler to more complex treatment according to the individual’s clinical situation. (who.int)


IVF vs IUI: How Does a Doctor Decide?

Before recommending IUI or IVF, your fertility specialist may assess:

Female Partner

  • Age
  • Menstrual cycle
  • Ovulation
  • Ovarian reserve
  • Fallopian tubes
  • Uterus
  • Previous pregnancies
  • Previous fertility treatment

Male Partner

  • Semen analysis
  • Sperm concentration
  • Sperm motility
  • Sperm morphology
  • Previous fertility history
  • Relevant medical conditions

Couple

  • Duration of infertility
  • Cause of infertility
  • Previous treatment outcomes
  • Genetic considerations
  • Financial and practical preferences
  • Time available for treatment

This assessment helps the fertility team develop an individualised treatment plan.


Can IUI Be Converted to IVF?

Yes. Fertility treatment is often progressive.

A couple may begin with IUI when it is clinically appropriate. If pregnancy does not occur after an appropriate number of cycles, or if new information changes the diagnosis, the fertility specialist may recommend IVF.

For unexplained infertility, ASRM guidance has historically supported a limited course of stimulated IUI followed by IVF when unsuccessful, while age and individual circumstances can influence whether IVF is considered earlier. (asrm.org)


IVF vs IUI Frequently Asked Questions

Is IUI better than IVF?

Neither treatment is universally better. IUI is less invasive and generally less expensive, while IVF can be appropriate for a broader range of infertility conditions. The right treatment depends on the couple’s diagnosis and circumstances.

Is IVF more successful than IUI?

IVF generally has a higher pregnancy potential per treatment cycle than IUI in many clinical situations, but success varies significantly with age, diagnosis and other factors. Comparing percentages without considering the patient population can be misleading.

Is IUI cheaper than IVF?

Generally, yes. IUI usually has a lower per-cycle cost because it does not involve egg retrieval or laboratory embryo development. However, total treatment costs vary.

How many IUI cycles should I try before IVF?

There is no single number for every patient. The decision depends on age, diagnosis, ovarian reserve, sperm parameters and previous treatment. In selected cases of unexplained infertility, several stimulated IUI cycles may be considered before IVF. (asrm.org)

Can IUI work with low sperm count?

It may be possible in selected cases, depending on the severity of the sperm abnormality and the number of motile sperm available after processing. Severe male-factor infertility may require IVF with ICSI.

Can IUI work with blocked fallopian tubes?

IUI generally requires at least one functioning fallopian tube because fertilisation still occurs inside the reproductive tract. If both tubes are blocked, IVF may be considered.

Is IVF painful?

IVF involves more procedures than IUI, including injections and egg retrieval. Pain and discomfort vary between individuals, and clinics use appropriate pain relief or sedation for egg retrieval.

Does IVF guarantee pregnancy?

No. IVF can provide an effective fertility treatment option, but it does not guarantee pregnancy or a live birth.

Which is better for older women: IUI or IVF?

Age is an important factor in fertility treatment planning. Depending on age, ovarian reserve, diagnosis and time available for treatment, a fertility specialist may discuss IVF sooner rather than spending multiple cycles on IUI.


IVF vs IUI in Srinagar

If you are searching for IVF vs IUI in Srinagar, the first step is to understand why pregnancy has not occurred.

At Imprimis IVF & Fertility Centre, Srinagar, a fertility specialist can evaluate both partners and discuss whether IUI, IVF or another fertility treatment is appropriate.

The evaluation may include assessment of ovulation, ovarian reserve, fallopian tubes, semen parameters and other relevant fertility factors.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

Treatment recommendations should be based on an individual medical evaluation rather than an online comparison.


Final Thoughts: IVF vs IUI

IVF and IUI are not competing treatments where one is always better than the other.

IUI is a less invasive fertility treatment that may be suitable for selected couples. IVF is a more involved treatment that can address a wider range of fertility problems.

The most appropriate option depends on your:

  • Age
  • Fertility diagnosis
  • Ovarian reserve
  • Ovulation
  • Fallopian tube status
  • Sperm parameters
  • Previous treatment
  • Overall reproductive health

If you are unsure whether IUI or IVF is right for you, consult a qualified fertility specialist for an individual assessment.


Medical Reviewer & Editorial Information

Medical Reviewer: Imprimis IVF

Last Updated: September 19, 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar

Medical Disclaimer: This article is intended for general educational purposes and does not replace professional medical advice, diagnosis or treatment. Fertility treatment should be selected after an appropriate evaluation by a qualified fertility specialist. Individual treatment outcomes vary.

Medical References: World Health Organization (WHO) 2025 Guideline for the Prevention, Diagnosis and Treatment of Infertility; American Society for Reproductive Medicine (ASRM) guidance; European Society of Human Reproduction and Embryology (ESHRE) guidance.

Recurrent Pregnancy Loss: Causes, Diagnosis & Treatment

Experiencing a miscarriage can be emotionally and physically difficult. While miscarriage is relatively common, recurrent pregnancy loss (RPL) requires medical evaluation to understand whether an underlying cause may be contributing to repeated pregnancy losses.

Recurrent pregnancy loss is a distinct reproductive health condition and is different from infertility. According to the latest American Society for Reproductive Medicine (ASRM) guidance, recurrent pregnancy loss is defined as two or more spontaneous pregnancy losses, excluding confirmed molar or ectopic pregnancies. The losses do not necessarily have to occur consecutively.

Many miscarriages, particularly those occurring early in pregnancy, are related to chromosomal abnormalities in the embryo. The likelihood of chromosomal abnormalities also increases with maternal age. However, recurrent pregnancy loss can have several possible causes, and sometimes no single cause is identified even after a detailed evaluation.

If you have experienced repeated miscarriages, consulting an experienced fertility specialist or obstetrician-gynaecologist can help determine whether further testing or treatment is appropriate.

What Is Recurrent Pregnancy Loss?

Recurrent pregnancy loss (RPL) refers to repeated spontaneous pregnancy losses.

Current ASRM guidance defines RPL as the spontaneous loss of two or more pregnancies, excluding confirmed molar and ectopic pregnancies. Pregnancy losses do not have to be consecutive for evaluation to be considered.

The term recurrent miscarriage is also commonly used. Older medical literature may use the term recurrent abortion, but “recurrent pregnancy loss” is generally preferred for patient-focused medical communication.

Recurrent pregnancy loss can be associated with genetic, anatomical, hormonal, metabolic, immune-related and other factors. In some couples, no clear cause is identified.


What Causes Recurrent Pregnancy Loss?

Causes Recurrent Pregnancy Loss

There is no single cause of recurrent miscarriage. A detailed evaluation may consider several factors involving the embryo, chromosomes, uterus, hormones, metabolism, and the health of both partners.

1. Chromosomal Abnormalities

Chromosomal abnormalities are an important cause of early pregnancy loss.

Approximately 50%–60% of first-trimester miscarriages are associated with embryonic aneuploidy, and the likelihood of aneuploidy is strongly influenced by maternal age.

Most chromosomal abnormalities occur sporadically during egg or embryo development. In some cases, however, chromosome abnormalities involving one of the parents may contribute to recurrent pregnancy loss.

When possible, chromosome testing of miscarriage tissue may provide useful information during recurrent pregnancy loss evaluation. The latest ASRM guidance recommends chromosome analysis of pregnancy-loss tissue, when feasible, as an important part of evaluation.

2. Uterine Abnormalities

Problems affecting the structure of the uterus may contribute to pregnancy loss in some women.

These may include:

  • Uterine septum
  • Certain congenital uterine anomalies
  • Fibroids
  • Endometrial polyps
  • Intrauterine adhesions

Your fertility specialist may recommend imaging or other investigations based on your history and symptoms.

3. Antiphospholipid Syndrome

Antiphospholipid syndrome (APS) is an autoimmune condition associated with abnormal blood clotting and specific pregnancy complications.

APS is an established and potentially treatable cause of recurrent pregnancy loss. Testing may be recommended when a patient’s history suggests an increased risk.

Treatment for confirmed obstetric APS may include medications such as low-dose aspirin and heparin under specialist supervision. These medicines should not be started without medical advice. Current evidence does not support routinely prescribing aspirin or anticoagulants to everyone with recurrent pregnancy loss.

4. Thyroid and Metabolic Conditions

Certain medical conditions may be associated with pregnancy loss.

Depending on the individual’s history, evaluation may include conditions such as:

  • Thyroid disease
  • Diabetes
  • Other metabolic disorders

The latest ASRM guidance supports targeted assessment for conditions such as thyroid disease and diabetes when clinically appropriate.

5. Age-Related Factors

Maternal age is an important factor in miscarriage risk because chromosomal abnormalities in eggs and embryos become more common with increasing age.

This does not mean that pregnancy after 35 is impossible or necessarily unsuccessful. However, age should be considered when evaluating recurrent pregnancy loss and planning future pregnancy.

6. Other Factors

Depending on the clinical history, doctors may also consider:

  • Genetic factors
  • Certain anatomical conditions
  • Lifestyle factors
  • Chronic medical conditions
  • Previous pregnancy complications

Not every proposed cause of recurrent miscarriage has strong evidence. Current guidelines recommend targeted evaluation rather than routinely performing every available test.


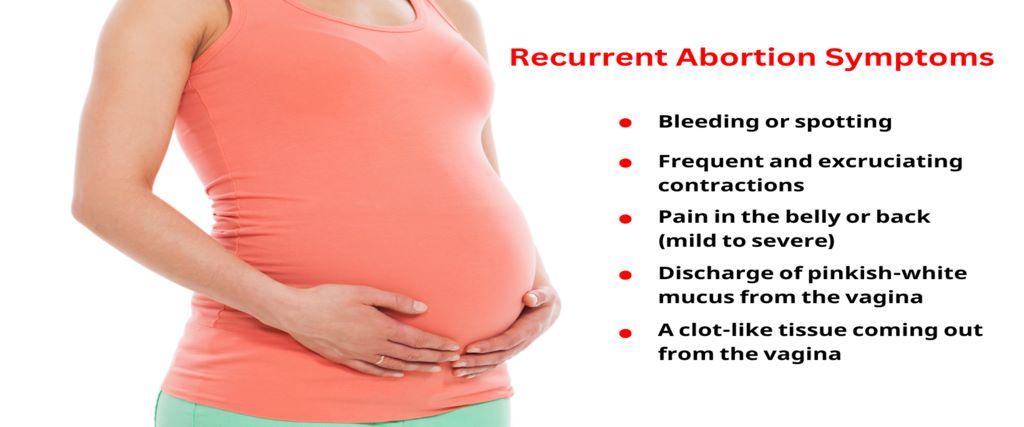
Recurrent Pregnancy Loss Symptoms

Recurrent Pregnancy Loss Symptoms

Recurrent pregnancy loss itself does not usually have a specific set of symptoms between pregnancies. The main concern is repeated pregnancy loss.

During an individual miscarriage, symptoms may include:

  • Vaginal bleeding or spotting
  • Lower abdominal or pelvic cramping
  • Back pain
  • Passing tissue or clots
  • Decreasing pregnancy symptoms

However, these symptoms do not always mean that a miscarriage is occurring. Bleeding and abdominal pain during pregnancy can have several causes.

Seek urgent medical care if you experience heavy bleeding, severe abdominal or pelvic pain, dizziness, fainting, fever or other concerning symptoms during pregnancy.


When Should You See a Doctor for Recurrent Miscarriage?

If you have experienced two or more pregnancy losses, it is reasonable to discuss recurrent pregnancy loss evaluation with a qualified obstetrician-gynaecologist or fertility specialist. Current ASRM guidance recognises RPL after two spontaneous pregnancy losses.

You should especially seek specialist advice if:

  • You have had two or more miscarriages.
  • You have experienced a second-trimester pregnancy loss.
  • You have irregular menstrual cycles.
  • You have a known uterine abnormality.
  • You have a history suggesting autoimmune or metabolic disease.
  • You or your partner has a known genetic condition.
  • You have been trying to conceive again after repeated pregnancy loss.

Tests for Recurrent Pregnancy Loss

There is no single test that can identify every cause of recurrent pregnancy loss.

Your doctor may recommend targeted investigations based on your pregnancy history, age, previous test results and other health factors.

Common Tests

Depending on the individual situation, evaluation may include:

Genetic Testing

Chromosome testing of pregnancy-loss tissue can help determine whether a chromosomal abnormality contributed to the miscarriage.

In selected cases, parental genetic testing may also be considered.

Uterine Evaluation

Tests used to assess the uterus may include:

The appropriate test depends on the suspected condition.

Antiphospholipid Antibody Testing

Testing for antiphospholipid syndrome may be recommended when clinically appropriate.

Thyroid and Metabolic Assessment

Your doctor may recommend blood tests to assess thyroid function, diabetes or other metabolic conditions depending on your medical history.

Evaluation of Other Health Factors

A detailed medical, reproductive and family history can help determine whether additional investigations are required.


Can Recurrent Pregnancy Loss Be Prevented?

There is no guaranteed way to prevent every miscarriage because many early pregnancy losses are caused by chromosomal abnormalities that occur during embryo development.

However, addressing treatable medical conditions and maintaining good preconception health may support a healthy pregnancy.

Steps That May Support a Healthy Pregnancy

Maintain a Healthy Lifestyle

Aim for a balanced diet, regular physical activity and a healthy weight appropriate for your individual circumstances.

Avoid Smoking and Tobacco

Smoking is associated with adverse reproductive and pregnancy outcomes. Avoid tobacco and exposure to tobacco smoke when planning pregnancy.

Avoid Alcohol During Pregnancy

Alcohol should be avoided during pregnancy.

Review Medications Before Pregnancy

Speak with your doctor before starting, stopping or changing any medication while trying to conceive or during pregnancy.

Manage Existing Health Conditions

Conditions such as diabetes and thyroid disease should be appropriately evaluated and managed before and during pregnancy.

Take Recommended Prenatal Supplements

Your doctor may recommend folic acid and other prenatal supplements based on your individual needs.

Attend Preconception Care

A preconception consultation can help identify medical or reproductive factors that may need attention before another pregnancy.


Recurrent Pregnancy Loss Treatment

Recurrent Pregnancy Loss Treatment

Treatment for Recurrent Miscarriage depends on the underlying cause.

There is no single treatment that works for every couple.

After evaluation, treatment may involve:

  • Management of thyroid or metabolic conditions
  • Treatment of confirmed antiphospholipid syndrome
  • Treatment of certain uterine abnormalities
  • Genetic counselling
  • Fertility treatment where appropriate
  • Psychological and emotional support

Current guidelines emphasise evidence-based, targeted treatment and caution against the routine use of tests or therapies that have not demonstrated clear benefit.


Treatment for Uterine Abnormalities

If a uterine abnormality is identified and is considered relevant to the pregnancy losses, treatment may sometimes be recommended.

Depending on the condition, treatment can include procedures such as hysteroscopic surgery.

For example, a uterine septum may be treated surgically in selected patients after appropriate evaluation and counselling.

The decision to operate should be individualised rather than based solely on an ultrasound finding.


Treatment for Antiphospholipid Syndrome

Women with confirmed obstetric antiphospholipid syndrome may benefit from specific treatment during pregnancy.

Depending on the clinical situation, a specialist may prescribe low-dose aspirin and heparin or another appropriate anticoagulant.

These medications are not appropriate for everyone with recurrent miscarriage or for people without a confirmed indication. They can have important side effects and should only be used under medical supervision.


Can IVF Help With Recurrent Pregnancy Loss?

IVF is not automatically required for Recurrent Miscarriage

Many couples with recurrent pregnancy loss can achieve a successful pregnancy without IVF, depending on the cause, age and other fertility factors.

However, IVF may be considered when there is another indication for assisted reproductive treatment or in selected couples where genetic factors are relevant.

IVF allows eggs to be fertilised in the laboratory and embryos to be transferred to the uterus.

IVF and Genetic Testing

In selected cases, preimplantation genetic testing (PGT) may be discussed when there is a known genetic or chromosomal indication.

However, PGT is not a universal treatment for recurrent pregnancy loss. The benefits, limitations, cost and possibility of obtaining a suitable embryo should be discussed with a fertility specialist.

Current ASRM guidance notes that evidence concerning PGT-A in recurrent pregnancy loss is still nuanced, and treatment should be individualised rather than offered routinely to every patient with RPL.


Chances of a Successful Pregnancy

Experiencing recurrent miscarriage does not mean that a future healthy pregnancy is impossible.

The outcome depends on several factors, including:

  • Maternal age
  • Number and timing of previous pregnancy losses
  • Chromosomal findings
  • Underlying medical conditions
  • Uterine factors
  • Whether a treatable cause is identified

Importantly, many cases remain unexplained even after evaluation. The latest ASRM guidance reports that 50%–80% of patients with unexplained recurrent pregnancy loss may go on to have a successful pregnancy, depending on individual circumstances.

Your individual prognosis should be discussed with your fertility specialist rather than estimated from a general percentage.


Emotional Support After Recurrent Miscarriage

Recurrent Miscarriage can be emotionally challenging for both partners.

Feelings of sadness, anxiety, grief, frustration or fear during a subsequent pregnancy are understandable.

Psychological support and counselling are an important part of recurrent pregnancy loss care. Current ASRM guidance specifically recommends emotional support for patients and couples experiencing RPL.

Seeking professional support does not mean that your concerns are being dismissed. Emotional wellbeing is an important part of reproductive healthcare.


Recurrent Pregnancy Loss Treatment in Srinagar

If you are looking for recurrent pregnancy loss treatment in Srinagar, an evaluation by a fertility specialist can help identify possible causes and determine whether further investigations or treatment are appropriate.

At Imprimis IVF & Fertility Centre, Srinagar, couples can seek fertility evaluation and discuss recurrent miscarriage, infertility and available fertility treatment options.

The centre provides fertility-related services including infertility evaluation, IUI and IVF treatment.

Clinic Information

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 9797756111

If you have experienced repeated miscarriages, consult a qualified fertility specialist before starting medicines or fertility treatment on your own.


Frequently Asked Questions

What is recurrent pregnancy loss?

Recurrent pregnancy loss is generally defined as two or more spontaneous pregnancy losses. Current ASRM guidance does not require the losses to be consecutive.

Is recurrent abortion the same as recurrent miscarriage?

The terms may be used to describe repeated pregnancy loss, but recurrent pregnancy loss (RPL) is the preferred modern clinical terminology for patient education.

How many miscarriages are considered recurrent pregnancy loss?

Current ASRM guidance defines recurrent pregnancy loss as two or more spontaneous pregnancy losses.

What is the most common cause of recurrent miscarriage?

Chromosomal abnormalities are a major cause of early pregnancy loss. However, recurrent pregnancy loss can have several possible causes, and some cases remain unexplained.

Can PCOS cause recurrent miscarriage?

PCOS may be associated with certain reproductive and metabolic risks, but recurrent pregnancy loss should not automatically be attributed to PCOS. A proper medical evaluation is needed to identify possible contributing factors.

Can thyroid problems cause recurrent miscarriage?

Thyroid disorders can affect reproductive and pregnancy health. Appropriate thyroid assessment may be part of the evaluation of recurrent pregnancy loss when clinically indicated.

Can recurrent pregnancy loss be treated?

Yes, in some cases an underlying cause can be identified and treated. However, there is no single treatment for all cases of recurrent pregnancy loss.

Is IVF necessary after recurrent miscarriage?

No. IVF is not automatically required after recurrent miscarriage. It may be considered when there is another indication for IVF or in selected situations involving genetic or fertility factors.

Can IVF prevent miscarriage?

IVF cannot guarantee that miscarriage will be prevented. In selected cases, IVF with appropriate genetic testing may be discussed, but it is not a universal treatment.

Should I take aspirin or heparin after repeated miscarriages?

Do not start aspirin or heparin without medical advice. These medications may be appropriate for selected patients, particularly those with confirmed antiphospholipid syndrome, but they are not routinely recommended for everyone.

Can I have a healthy pregnancy after recurrent miscarriage?

Yes. Many people with recurrent pregnancy loss subsequently have a successful pregnancy. Your individual chances depend on factors such as age, medical history, previous pregnancy losses and whether an underlying cause is identified.


Take the Next Step After Recurrent Pregnancy Loss

Experiencing repeated pregnancy loss can be difficult, but it does not mean that a successful pregnancy is impossible.

The right approach is to identify possible causes, treat conditions that can be addressed and develop an individualised pregnancy or fertility plan.

If you have experienced two or more pregnancy losses, consider speaking with a qualified fertility specialist or obstetrician-gynaecologist for appropriate evaluation.

Imprimis IVF & Fertility Centre, Srinagar
2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu & Kashmir – 190014

Phone: +91 9650777084 / +91 979775611

Medical Reviewer: Imprimis IVF & Fertility Centre Team

Last Updated: September 19, 2026

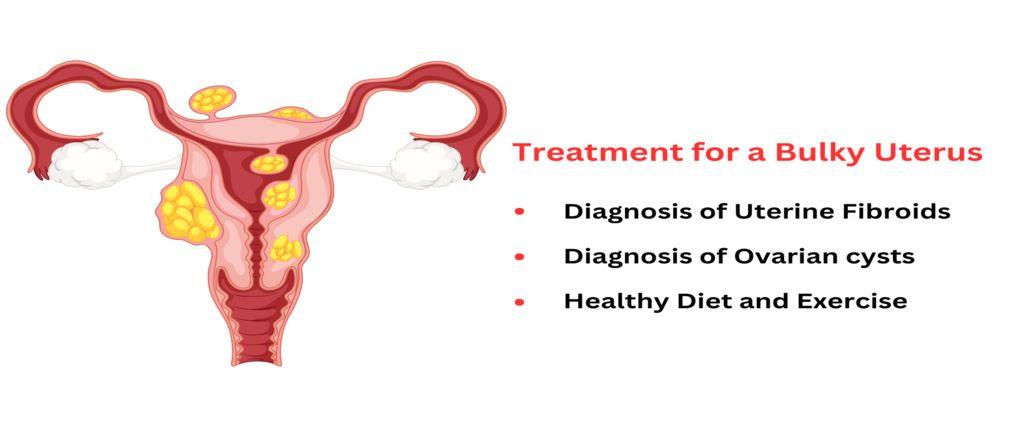
Ovarian Cyst: Symptoms, Causes, Types, Diagnosis & Treatment

An ovarian cyst is a fluid-filled sac that develops in or on an ovary. Ovarian cysts are common, and many cause no symptoms or go away on their own without treatment. However, some cysts can become large, cause pain, rupture, twist the ovary or require further evaluation.

If you have been diagnosed with an ovarian cyst, it is natural to have questions such as:

  • What causes an ovarian cyst?
  • What are the symptoms of an ovarian cyst?
  • Is an ovarian cyst dangerous?
  • Can an ovarian cyst affect fertility?
  • What size ovarian cyst needs treatment?
  • Does every ovarian cyst require surgery?

This guide explains ovarian cyst symptoms, causes, types, diagnosis, treatment and possible effects on fertility in simple language.

What Is an Ovarian Cyst?

An ovarian cyst is a sac that develops within an ovary or on its surface. The ovaries are part of the female reproductive system and contain the eggs that are released during the reproductive years.

Many ovarian cysts develop naturally as part of the menstrual cycle. These are called functional ovarian cysts and are usually harmless. They often disappear within a few menstrual cycles without treatment.

Not every ovarian cyst is the same. The type, size, appearance and symptoms help doctors decide whether monitoring, further testing or treatment is needed.


Ovarian Cyst Symptoms

Many ovarian cysts cause no symptoms and are discovered during an ultrasound or pelvic examination performed for another reason.

When symptoms occur, they may include:

Common Symptoms of Ovarian Cysts

  • Pelvic or lower abdominal pain
  • A feeling of pressure, fullness or heaviness in the abdomen
  • Bloating or abdominal swelling
  • Pain during sexual intercourse
  • Frequent urination or difficulty emptying the bladder
  • Difficulty emptying the bowel
  • Heavy, irregular or unusual menstrual bleeding
  • Feeling full quickly

The symptoms can vary depending on the size and type of cyst and whether a complication such as rupture or ovarian torsion occurs.

When Should You Seek Urgent Medical Care?

Sudden or severe pelvic or abdominal pain, especially when accompanied by nausea, vomiting, fever, weakness or dizziness, requires urgent medical assessment.

These symptoms can occur with complications such as ovarian torsion or a ruptured cyst.


What Causes Ovarian Cysts?

The causes of ovarian cysts vary by type.

1. Functional Ovarian Cysts

Functional cysts develop as part of the normal menstrual cycle.

They include:

  • Follicular cysts: Develop when a follicle does not release an egg and continues to grow.
  • Corpus luteum cysts: Develop after ovulation, when the follicle transforms into the corpus luteum and fluid accumulates within it.

Functional cysts are the most common type and usually resolve without treatment.

2. Endometriosis

Endometriosis can cause tissue similar to the uterine lining to grow outside the uterus. When this tissue affects an ovary, it can form an ovarian cyst called an endometrioma.

Endometriomas may be associated with pelvic pain and difficulties with fertility.

3. Pregnancy

Some ovarian cysts can remain during early pregnancy. For example, a corpus luteum cyst may be seen during pregnancy and may resolve naturally.

4. Fertility Medicines

Some medicines used to stimulate ovulation can increase the chance of developing ovarian cysts or enlarged ovaries. Your fertility specialist can monitor ovarian response during treatment.

5. Pelvic Infections and Other Conditions

Certain pelvic infections and underlying reproductive health conditions may also be associated with ovarian cysts.


What Are the Types of Ovarian Cysts?

Ovarian cysts can be broadly divided into functional and other types.

Functional Cysts

Functional cysts are related to the menstrual cycle and include:

  • Follicular cysts
  • Corpus luteum cysts

They are generally benign and often disappear on their own.

Dermoid Cysts

Dermoid cysts, also called mature cystic teratomas, develop from cells that can form different types of body tissue. They may contain tissues such as hair, skin or teeth.

Cystadenomas

Cystadenomas develop from cells on the surface of the ovary. They may contain watery or mucous-like material and can sometimes become large.

Endometriomas

Endometriomas are ovarian cysts associated with endometriosis. They may affect pelvic health and, in some cases, fertility.


Ovarian Cyst vs PCOS: Are They the Same?

No. An ovarian cyst and PCOS are not the same condition.

Polycystic ovary syndrome (PCOS) is a hormonal and metabolic condition that can affect ovulation and menstrual cycles. Despite its name, PCOS should not be understood simply as having one or more ovarian cysts.

A person can have an ovarian cyst without having PCOS, and a person with PCOS does not necessarily have ovarian cysts in the usual clinical sense.

If you have irregular periods, excess androgen-related symptoms or difficulty conceiving, a fertility specialist can determine whether PCOS or another condition may be involved.


Can Ovarian Cysts Affect Fertility?

In most cases, an ovarian cyst does not prevent pregnancy.

However, fertility effects can depend on the type of cyst and the underlying condition. For example, endometriomas may be associated with difficulty becoming pregnant. PCOS can also affect fertility because irregular ovulation may make conception more difficult.

Some cysts do not generally affect fertility. Functional cysts, cystadenomas and dermoid cysts are not usually associated with infertility.

Ovarian Cyst and IVF Treatment

If you are undergoing fertility treatment, your doctor will assess the cyst’s size, appearance, type and effect on the ovaries before deciding how to proceed.

Treatment is individualised. Removing a cyst is not automatically necessary before IVF.

If surgery is being considered, fertility preservation should be discussed because the effect of surgery can depend on the type of cyst and ovarian involvement.


How Are Ovarian Cysts Diagnosed?

An ovarian cyst may be discovered during a pelvic examination or an imaging test.

1. Pelvic Examination

A doctor may perform a pelvic examination to look for tenderness, swelling or other abnormalities.

2. Ultrasound

Pelvic ultrasound, particularly transvaginal ultrasound when appropriate, is commonly used to evaluate ovarian cysts.

Ultrasound can help assess:

  • Cyst size
  • Location
  • Shape
  • Whether it is fluid-filled or contains solid components
  • Internal features of the cyst

These findings help the doctor determine whether monitoring or further evaluation is appropriate.

3. Pregnancy Test

A pregnancy test may be recommended because pregnancy-related ovarian changes can affect the interpretation of an ovarian mass or cyst.

4. Blood Tests

Blood tests may sometimes be recommended depending on the cyst’s appearance, the patient’s age and other clinical factors.

In selected situations, doctors may use tumour-marker testing. However, an elevated tumour marker does not automatically mean ovarian cancer, because some benign conditions can also affect these results.

5. Additional Imaging or Laparoscopy

Depending on the clinical situation, additional imaging or laparoscopy may be considered.

The appropriate test depends on the cyst’s characteristics and the level of concern.


Ovarian Cyst Treatment

Not every ovarian cyst requires treatment.

Treatment depends on factors such as:

  • Cyst size
  • Cyst appearance
  • Type of cyst
  • Symptoms
  • Age
  • Menopausal status
  • Whether the cyst is changing over time
  • Fertility plans
  • Concern about complications or malignancy

1. Watchful Waiting

Many small, simple ovarian cysts do not need immediate treatment.

Your doctor may recommend observation and a repeat ultrasound after a suitable interval to determine whether the cyst has disappeared or changed.

2. Medicines

Medicines may be prescribed to manage symptoms or treat an underlying condition.

Hormonal contraceptives can reduce the development of some new functional cysts by preventing ovulation, but they generally do not shrink an existing ovarian cyst.

3. Laparoscopic Ovarian Cystectomy

A laparoscopic cystectomy is a minimally invasive procedure used to remove an ovarian cyst while attempting to preserve the ovary when clinically appropriate.

Whether cyst removal is appropriate depends on the cyst’s type, size, and characteristics, as well as the patient’s fertility goals.

4. Laparotomy

A laparotomy is an open surgical procedure involving a larger abdominal incision. It may be considered for very large cysts or when concerns warrant a different surgical approach.

5. Oophorectomy

In selected cases, removal of the affected ovary may be necessary. The decision depends on the cyst’s characteristics, the patient’s age, fertility plans and the possibility of cancer or other complications.

Whenever possible, fertility-preserving options should be discussed with the treating specialist.


What Size of Ovarian Cyst Is Dangerous?

There is no single cyst size that automatically means an ovarian cyst is dangerous.

Size is only one part of the assessment. Doctors also consider:

  • Whether the cyst is simple or complex
  • Its ultrasound appearance
  • Whether it is growing
  • Whether it causes symptoms
  • The patient’s age
  • Menopausal status
  • Whether there are complications
  • Whether there are features that raise concern for malignancy

Therefore, the old rule that “an ovarian cyst larger than 5 cm is dangerous” is too simplistic.

A large cyst may be benign, while a smaller cyst may still require evaluation depending on its appearance and symptoms.


Can an Ovarian Cyst Go Away on Its Own?

Yes. Many functional ovarian cysts resolve on their own within a few months or several menstrual cycles.

Your doctor may recommend follow-up ultrasound to confirm that the cyst is shrinking or has disappeared.

However, persistent, enlarging, symptomatic or complex cysts may require additional evaluation.


Ovarian Cyst Complications

Most ovarian cysts do not cause serious complications. However, complications can occur.

Ovarian Torsion

A large cyst can sometimes cause the ovary to twist, potentially reducing its blood supply.

Sudden severe pelvic pain accompanied by nausea or vomiting requires urgent medical attention.

Cyst Rupture

An ovarian cyst can sometimes rupture and cause sudden pelvic or abdominal pain. In some cases, bleeding can occur.

Infertility or Reduced Fertility

Some ovarian conditions, particularly endometriomas and conditions that affect ovulation, may be associated with difficulty conceiving.

Malignancy

Most ovarian cysts are benign. However, some ovarian masses can be cancerous, and the likelihood of malignancy varies with factors such as age, menopausal status and the characteristics of the cyst.


Can Ovarian Cysts Be Prevented?

There is no guaranteed way to prevent most ovarian cysts because many develop naturally as part of the menstrual cycle.

However, paying attention to changes in your menstrual cycle and seeking medical evaluation for persistent or unusual symptoms can help identify ovarian problems early.

Regular gynaecological care can also be useful, particularly if you have a history of ovarian cysts or an underlying condition such as endometriosis.


When Should You See a Doctor for an Ovarian Cyst?

Consider consulting a gynaecologist or fertility specialist if you have:

  • Persistent pelvic pain
  • Repeated bloating or abdominal pressure
  • Significant changes in your periods
  • Pain during intercourse
  • Difficulty becoming pregnant
  • A cyst that has been detected on ultrasound
  • A cyst that is increasing in size
  • A history of recurrent ovarian cysts

Seek Urgent Medical Care If You Have

  • Sudden severe pelvic or abdominal pain
  • Severe pain with nausea or vomiting
  • Fever with significant abdominal or pelvic pain
  • Severe weakness, dizziness or fainting

These symptoms can indicate a complication and should not be ignored.


Frequently Asked Questions About Ovarian Cysts

Is an ovarian cyst dangerous?

Most ovarian cysts are not dangerous and resolve without treatment. However, some cysts can rupture, cause ovarian torsion, persist, grow or have features requiring further evaluation.

Can an ovarian cyst cause infertility?

Most ovarian cysts do not cause infertility. However, certain conditions associated with ovarian cysts, such as endometriosis and PCOS-related ovulatory problems, can affect fertility.

What is the most common ovarian cyst?

Functional ovarian cysts are the most common type. They develop as part of the menstrual cycle and usually resolve on their own.

Do ovarian cysts need surgery?

Not always. Many cysts can be monitored without surgery. Surgery may be considered when a cyst is large, persistent, symptomatic, growing or has features that require further evaluation.

Can I get pregnant with an ovarian cyst?

Yes, many women with ovarian cysts can become pregnant. The effect on fertility depends mainly on the type of cyst and the underlying condition.

Can an ovarian cyst disappear naturally?

Yes. Many functional ovarian cysts resolve on their own within a few months. Follow-up may be recommended depending on the cyst’s appearance and your symptoms.

Does every ovarian cyst mean cancer?

No. Most ovarian cysts are benign. However, some cysts or ovarian masses require further evaluation, particularly depending on age, menopausal status and ultrasound characteristics.


Ovarian Cyst Treatment in Srinagar

If you have been diagnosed with an ovarian cyst and are concerned about pain, fertility, pregnancy or IVF treatment, an appropriate evaluation can help determine the next step.

At Imprimis IVF & Fertility Centre in Srinagar, fertility specialists can evaluate your ovarian health and discuss appropriate treatment options based on your individual condition and fertility goals.

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: September 2026

Clinic Information

Imprimis IVF & Fertility Centre – Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014
Phone: 9650777084 / 9797756111

If an ovarian cyst has been found on your ultrasound, bring your scan reports and previous medical records to your consultation. Your doctor can explain the cyst’s size, appearance, likely type and whether follow-up or treatment is needed.

Five Stages of IVF: IVF Treatment Process Step by Step

Five Stages of IVF: Starting IVF can bring a mixture of hope, excitement and uncertainty. One of the most common questions couples have is: What actually happens during an IVF cycle?

In vitro fertilisation (IVF) is an assisted reproductive technology (ART) in which eggs are retrieved from the ovaries, fertilised with sperm in a laboratory, and the resulting embryos are transferred into the uterus. The treatment involves several carefully monitored steps rather than one single procedure.

If you are considering IVF treatment in Srinagar, understanding the IVF process step by step can help you know what to expect before, during and after treatment.

What Are the Five Stages of IVF?

The main stages of an IVF cycle are:

  1. Pre-cycle testing and treatment planning
  2. Ovarian stimulation and trigger
  3. Egg retrieval
  4. Sperm collection and fertilisation
  5. Embryo culture and embryo transfer

The exact IVF protocol, medication schedule and timing can vary depending on your age, ovarian reserve, diagnosis, previous treatment and your fertility specialist’s recommendations.


Stage 1: Pre-Cycle Testing and IVF Planning

Before starting an IVF cycle, your fertility specialist will review your medical history and assess both partners.

Depending on your situation, testing may include:

  • Blood tests and hormone evaluation
  • Ovarian reserve assessment
  • Transvaginal ultrasound
  • Assessment of the uterus and ovaries
  • Fallopian tube evaluation when clinically appropriate
  • Semen analysis
  • Screening tests before treatment
  • Review of previous fertility treatments

These tests help the fertility team understand the likely cause of infertility and create an IVF treatment plan suited to your individual needs.

Why Is Pre-IVF Testing Important?

IVF is not a one-size-fits-all treatment. Your doctor may modify the stimulation protocol, medication doses, fertilisation method, or embryo-transfer plan based on your test results.

A personalised treatment plan can also help identify conditions that may need attention before embryo transfer.


Stage 2: Ovarian Stimulation and Trigger Injection

The second stage of IVF is ovarian stimulation.

During a natural menstrual cycle, usually one egg becomes dominant. During IVF, fertility medicines are used to stimulate the ovaries so that multiple follicles can develop.

How Long Does Ovarian Stimulation Take?

Ovarian stimulation typically lasts 8–14 days, though the exact duration varies by patient and treatment protocol.

During this stage, you may have:

  • Regular ultrasound scans
  • Blood tests when required
  • Monitoring of follicle growth
  • Medication adjustments
  • A trigger injection when the follicles are ready

The trigger helps the eggs complete the final stage of maturation before retrieval.

Why Are IVF Scans Important?

Regular monitoring allows the fertility specialist to assess follicle development and adjust treatment when necessary.

The aim is not simply to produce as many eggs as possible. The goal is to achieve an appropriate ovarian response while reducing treatment-related risks.


Stage 3: Egg Retrieval or Egg Pick-Up

Once the follicles have developed appropriately, the next step is egg retrieval, also called egg pick-up or OPU.

Egg retrieval is usually performed approximately 34–36 hours after the trigger injection, depending on the treatment protocol.

How Is Egg Retrieval Done?

The procedure is generally performed using transvaginal ultrasound guidance.

A thin needle is guided through the vaginal wall toward the ovarian follicles. Fluid containing the eggs is aspirated from the follicles and sent to the embryology laboratory.

The procedure itself is usually relatively short, although the exact duration varies.

After egg retrieval, the embryology team assesses the collected eggs and identifies those suitable for further treatment.

Is Egg Retrieval Painful?

Egg retrieval is performed with appropriate pain relief or anaesthesia, in accordance with the clinic’s protocol and the patient’s needs.

Some women may experience mild cramping, pelvic discomfort or light bleeding afterwards. Your fertility team will explain which symptoms to expect and when to contact the clinic.


Stage 4: Sperm Collection and Fertilisation

After egg retrieval, the eggs are prepared in the embryology laboratory.

Sperm may be collected through a semen sample. In certain cases of male-factor infertility or very low sperm availability, a surgical sperm-retrieval procedure may be recommended.

Possible techniques include:

  • TESA – Testicular Sperm Aspiration
  • TESE – Testicular Sperm Extraction
  • MicroTESE – Microdissection Testicular Sperm Extraction
  • PESA – Percutaneous Epididymal Sperm Aspiration
  • MESA – Microsurgical Epididymal Sperm Aspiration

How Are Eggs Fertilised During IVF?

There are two commonly used approaches:

Conventional IVF: Eggs and sperm are placed together in a laboratory dish so that fertilisation can occur naturally.

ICSI: A single sperm is injected directly into a mature egg using a specialised laboratory technique. ICSI may be recommended in selected cases, particularly when there are significant male-factor infertility concerns.

Your fertility specialist and embryologist will decide which fertilisation method is appropriate based on your individual circumstances.


Stage 5: Embryo Culture and Embryo Transfer

After fertilisation, successfully fertilised eggs can develop into embryos in the laboratory.

Embryos are monitored as they develop. Some embryos may reach the blastocyst stage around day 5–6, although embryo development varies.

What Is Embryo Transfer?

Embryo transfer is the stage in which an embryo is placed inside the uterus.

A thin, flexible catheter is passed through the cervix into the uterine cavity. The selected embryo is then released into the uterus.

Embryo transfer is an important part of IVF treatment, and clinical guidelines support techniques designed to make the procedure safe and effective.

Is Embryo Transfer Painful?

For many patients, embryo transfer causes little or no significant discomfort and usually does not require general anaesthesia.

Your doctor will provide individual instructions regarding medicines, activity and follow-up after the procedure.


What Happens After Embryo Transfer?

After embryo transfer, you enter the waiting period before pregnancy testing.

This can be an emotionally difficult part of IVF because you may not immediately know whether implantation has occurred.

Your fertility clinic will tell you when to take the pregnancy test. Testing too early can sometimes produce misleading results.

If the test is positive, your fertility team may arrange blood testing and an ultrasound at the appropriate time to confirm the pregnancy and assess its development.


How Long Does an IVF Cycle Take?

There is no single timeline that applies to every patient.

For many patients, one IVF cycle takes several weeks, including preparation, ovarian stimulation, egg retrieval, embryo development and transfer. Some treatment plans may take longer due to additional testing, frozen embryo transfer, medical conditions, or other factors.

Simple IVF Treatment Timeline

IVF Stage What Happens
Pre-cycle testing Fertility assessment and treatment planning
Ovarian stimulation Medicines stimulate follicle development
Monitoring Ultrasound and blood tests as required
Trigger Final egg maturation is triggered
Egg retrieval Eggs are collected from the ovaries
Fertilisation Eggs are fertilised with sperm
Embryo culture Embryos develop in the laboratory
Embryo transfer The selected embryo is placed in the uterus
Pregnancy test Testing is performed at the time advised by the clinic

Can You Continue Normal Activities After Embryo Transfer?

Many patients can return to their usual routine after embryo transfer, unless their doctor recommends otherwise.

Strict bed rest is generally not required after embryo transfer. ASRM guidance supports immediate ambulation after embryo transfer rather than prolonged immobilisation.

However, your own fertility specialist’s instructions should always take priority.


What Is the Success Rate of IVF?

There is no single IVF success rate that applies to every woman or every fertility centre.

IVF outcomes can vary according to factors such as:

  • Age
  • Ovarian reserve
  • Cause of infertility
  • Egg and sperm quality
  • Embryo development
  • Previous IVF history
  • Type of treatment
  • Use of own or donor eggs
  • Number and timing of embryo transfers

National ART data also show that success rates can vary substantially according to patient and treatment characteristics. Therefore, published percentages should not be treated as a personal prediction of pregnancy or live birth.

Does Age Affect IVF Success?

Yes. Age is an important factor when discussing IVF outcomes, particularly when using a woman’s own eggs. However, the individual prognosis depends on several factors rather than age alone.

Your fertility specialist can explain your expected outcome based on your medical history and test results.


How Much Does IVF Treatment Cost?

The cost of IVF varies from patient to patient.

Expenses may include:

  • Initial consultation
  • Fertility investigations
  • IVF medicines and injections
  • Ultrasound monitoring
  • Egg retrieval
  • Laboratory and embryology services
  • ICSI, when recommended
  • Embryo culture
  • Embryo transfer
  • Embryo freezing and storage, when required
  • Additional procedures or medications

Therefore, it is better to discuss the complete IVF treatment cost with your fertility clinic rather than relying on a single advertised figure.

For couples seeking IVF treatment in Srinagar, the final treatment plan and expected expenses can be discussed during a consultation.


What Are the Risks and Complications of IVF?

IVF is generally considered a safe fertility treatment, but like any medical treatment, it has potential risks.

Possible risks include:

Ovarian Hyperstimulation Syndrome (OHSS)

OHSS can occur when the ovaries respond excessively to fertility medicines. Symptoms can range from mild abdominal discomfort and bloating to more serious complications.

Severe symptoms require prompt medical attention.

Multiple Pregnancy

Transferring more than one embryo can increase the chance of twins or a higher-order multiple pregnancy. Multiple pregnancies carry increased risks for both the mother and babies.

For appropriate patients, single embryo transfer may reduce the risk of multiple pregnancy.

Ectopic Pregnancy

An ectopic pregnancy occurs when a pregnancy develops outside the uterus, most commonly in a fallopian tube. IVF is associated with a risk of ectopic pregnancy, so early follow-up after a positive pregnancy test is important.

Emotional Stress

IVF can be emotionally demanding. The appointments, injections, waiting period and uncertainty around treatment outcomes can create significant stress.

Couples should feel comfortable discussing emotional concerns with their healthcare team and seeking appropriate support when needed.


Frequently Asked Questions About the Five Stages of IVF

1. What are the five stages of IVF?

The IVF process can be broadly explained as pre-cycle testing, ovarian stimulation, egg retrieval, fertilisation and embryo development, followed by embryo transfer.

2. How many days does IVF treatment take?

The duration varies depending on the treatment protocol. An IVF cycle commonly takes several weeks, but individual timelines can be shorter or longer.

3. How many injections are needed during IVF?

There is no fixed number of injections for every patient. The number and type of medicines depend on the stimulation protocol, ovarian response and treatment plan.

4. What happens after egg retrieval?

The collected eggs are assessed in the laboratory. Suitable mature eggs are fertilised with sperm, and resulting embryos are monitored for further development.

5. When is embryo transfer done after egg retrieval?

Depending on embryo development and the treatment plan, transfer may occur a few days after egg retrieval or may be performed later as a frozen embryo transfer.

6. Is bed rest required after embryo transfer?

Prolonged bed rest is generally not required. Your doctor will provide personalised instructions regarding physical activity and medicines after transfer.

7. Is IVF successful on the first attempt?

IVF can result in pregnancy in the first cycle, but success is not guaranteed. Outcomes depend on several individual and treatment-related factors.

8. When should I consult an IVF specialist?

You may consider a fertility evaluation if you have been trying to conceive without success, have known fertility problems, irregular ovulation, blocked tubes, significant male-factor infertility or other factors that may affect fertility.


Why Choose Imprimis IVF & Fertility Centre in Srinagar?

If you are considering IVF treatment in Jammu & Kashmir, Imprimis IVF & Fertility Centre in Srinagar provides fertility evaluation, IVF treatment, and related assisted reproductive services.

The treatment plan is based on the patient’s fertility history, investigations and individual clinical needs rather than using the same protocol for every couple.

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: September 2026

Clinic Information

Imprimis IVF & Fertility Centre – Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014
Phone: 9650777084 / 9797756111

If you are considering IVF, schedule a consultation with a qualified fertility specialist to understand your diagnosis, treatment options, expected timeline and estimated cost.

Female Infertility: Causes, Symptoms, Tests & Treatment

Female infertility is a common reproductive health concern that can make it difficult to conceive or maintain a pregnancy. It may be related to problems with ovulation, the ovaries, fallopian tubes, uterus, hormones or other reproductive factors.

Infertility does not always have a single identifiable cause. Sometimes both partners contribute, while in other cases no clear cause is found.

If you are trying to conceive, understanding the causes of female infertility, female infertility symptoms, fertility tests and treatment options can help you understand when professional evaluation may be appropriate.

What Is Female Infertility?

Female infertility refers to difficulty achieving pregnancy because of factors affecting the female reproductive system.

Infertility is generally defined as not achieving pregnancy after 12 months of regular, unprotected sexual intercourse. For women aged 35 or older, fertility evaluation is generally recommended after 6 months of trying, while women over 40 may benefit from more immediate evaluation. Earlier assessment may also be appropriate when there are known fertility risk factors.

Female infertility can be associated with problems involving:

  • Ovulation
  • Ovarian function
  • Fallopian tubes
  • Uterus
  • Endometrium
  • Reproductive hormones
  • Ovarian reserve
  • Endometriosis
  • Genetic or structural conditions

The WHO notes that infertility may result from disorders affecting the ovaries, uterus, fallopian tubes and endocrine system.

Primary and Secondary Infertility

Female infertility can occur as primary infertility or secondary infertility.

Primary Infertility

Primary infertility refers to difficulty achieving a pregnancy when there has been no previous pregnancy.

Secondary Infertility

Secondary infertility refers to difficulty becoming pregnant after having achieved at least one previous pregnancy.

Both types may require evaluation to identify possible reproductive, hormonal, anatomical or other contributing factors.

What Causes Female Infertility?

There are many possible causes of female infertility. Some affect ovulation, while others involve the ovaries, fallopian tubes, uterus or reproductive hormones.

Common causes include:

  • PCOS and ovulation disorders
  • Endometriosis
  • Blocked or damaged fallopian tubes
  • Uterine fibroids
  • Uterine polyps or structural abnormalities
  • Diminished ovarian reserve
  • Primary ovarian insufficiency
  • Hormonal disorders
  • Pelvic infections
  • Previous pelvic surgery
  • Age-related decline in fertility
  • Certain medical treatments
  • Unexplained infertility

PCOS and Female Infertility

Polycystic ovary syndrome (PCOS) is a common hormonal and metabolic condition that can affect reproductive health.

PCOS may cause irregular or absent periods, abnormal ovulation, excess androgen levels, acne and excess facial or body hair. Because ovulation may occur irregularly or not occur, PCOS can make conception more difficult. WHO describes PCOS as one of the leading causes of infertility associated with abnormal ovulation.

Read more about PCOS and fertility.

Endometriosis

Endometriosis occurs when tissue similar to the lining of the uterus grows outside the uterus.

It can be associated with pelvic pain, painful periods, pain during sexual intercourse and difficulty conceiving. Endometriosis may affect fertility through inflammation, adhesions and changes involving the reproductive organs.

Read more about endometriosis.

Blocked or Damaged Fallopian Tubes

The fallopian tubes provide the pathway where sperm and egg normally meet.

Blocked or damaged tubes can interfere with fertilisation and may prevent the embryo from travelling normally toward the uterus.

Possible causes include:

  • Previous pelvic infections
  • Sexually transmitted infections
  • Pelvic inflammatory disease
  • Previous pelvic surgery
  • Endometriosis
  • Certain abdominal or pelvic conditions

Tubal disease is an important part of infertility evaluation, and tests such as HSG or sonohysterography may be used to assess tubal patency.

Learn more about blocked fallopian tubes.

Uterine Fibroids

Uterine fibroids are non-cancerous growths that develop in or around the uterus.

Many women with fibroids can conceive normally, but depending on their size and location, some fibroids may affect fertility or pregnancy.

Read more about uterine fibroids.

Ovarian Cysts

Ovarian cysts are fluid-filled structures that can develop in or on the ovaries.

Many ovarian cysts are temporary and do not affect fertility. However, certain conditions associated with ovarian cysts, including endometriosis or PCOS, may affect reproductive function.

Read more about ovarian cysts.

Diminished Ovarian Reserve

Ovarian reserve refers broadly to the remaining supply of eggs in the ovaries.

Ovarian reserve generally declines with age. Tests such as AMH, antral follicle count, and FSH/estradiol may be used as part of a fertility evaluation when clinically appropriate.

Importantly, ovarian reserve testing should be interpreted alongside age, medical history and other fertility findings. A low ovarian-reserve test does not by itself mean that natural pregnancy is impossible.

Primary Ovarian Insufficiency

Primary ovarian insufficiency (POI) occurs when normal ovarian function is lost before the age of 40.

It can affect ovulation and fertility and requires medical evaluation.

Read more about primary ovarian insufficiency.

Hormonal Disorders

Hormonal changes can interfere with ovulation and menstrual cycles.

Depending on the symptoms and medical history, a doctor may investigate hormones such as:

  • FSH
  • LH
  • Estradiol
  • TSH
  • Prolactin
  • Androgens

Not every hormone test is required for every woman. Testing should be based on the clinical situation.

Read more about the role of hormones in fertility.

Age and Female Fertility

Age is an important factor affecting female fertility.

Female fertility generally declines with increasing age because both the number and quality of available eggs decrease. The decline becomes more clinically significant during the later reproductive years.

For women aged 35 and older who have been trying to conceive for six months, fertility evaluation is generally recommended. Women over 40 may benefit from more immediate evaluation.

Unexplained Infertility

Sometimes fertility testing does not identify a clear reason for difficulty conceiving. This is known as unexplained infertility.

A normal initial evaluation does not mean that the fertility problem is imaginary or that pregnancy cannot occur. Your fertility specialist can discuss treatment options based on age, duration of infertility, previous pregnancies and other clinical factors.

Risk Factors for Female Infertility

Several factors may affect female reproductive health and fertility, including:

  • Increasing age
  • PCOS
  • Endometriosis
  • Previous pelvic infection
  • Previous pelvic surgery
  • Smoking
  • Excessive alcohol consumption
  • Significant underweight or obesity
  • Certain medications
  • Chemotherapy or radiation treatment
  • Some genetic or medical conditions
  • Certain environmental exposures

Not every woman with a risk factor will experience infertility.

What Are the Symptoms of Female Infertility?

Infertility itself may not cause noticeable symptoms. Difficulty becoming pregnant is often the main sign.

However, certain symptoms may indicate an underlying reproductive condition that deserves medical evaluation.

These may include:

  • Irregular or absent periods
  • Very heavy menstrual bleeding
  • Severe period pain
  • Pelvic pain
  • Pain during sexual intercourse
  • Symptoms of PCOS
  • Excess facial or body hair
  • Persistent acne associated with hormonal changes
  • Symptoms of thyroid or hormonal disorders
  • Previous pelvic infections
  • Repeated pregnancy loss

These symptoms do not automatically mean that a woman is infertile. They may indicate an underlying condition that should be evaluated.

For example, severe menstrual pain can be associated with endometriosis, which may affect fertility.

When Should You See a Fertility Specialist?

Consider a fertility evaluation if:

  • You are under 35 and have tried to conceive for 12 months without pregnancy.
  • You are 35 or older and have tried for 6 months without pregnancy.
  • You are over 40 and are planning pregnancy.
  • You have irregular or absent periods.
  • You have known or suspected endometriosis.
  • You have a history of blocked fallopian tubes.
  • You have undergone pelvic surgery.
  • You have a history of chemotherapy or radiation.
  • You have a known condition that may affect fertility.
  • Your partner has a known fertility problem.

Evaluation may be recommended earlier when there is a known condition associated with infertility.

How Is Female Infertility Diagnosed?

A female infertility evaluation usually begins with a detailed medical and reproductive history.

Your fertility specialist may ask about:

  • Menstrual cycle pattern
  • Previous pregnancies
  • Duration of infertility
  • Previous miscarriages
  • Pelvic pain
  • Previous surgeries
  • Previous infections
  • Medical conditions
  • Medications
  • Family history
  • Previous fertility treatments

The evaluation generally looks at three important areas:

  1. Ovulation
  2. Ovarian function and reserve
  3. The uterus and fallopian tubes

Male-partner evaluation should also be considered because infertility can involve male factors, female factors or both.

Female Infertility Tests

Depending on your symptoms and medical history, fertility tests may include:

1. Pelvic Examination

A physical and pelvic examination may help identify certain reproductive or anatomical problems.

2. Blood Tests

Blood tests may be used to evaluate hormones and other factors relevant to ovulation and reproductive health.

3. AMH Test

Anti-Müllerian hormone (AMH) may be used as one measure of ovarian reserve.

AMH should not be interpreted as a standalone fertility test. It is used alongside age, ultrasound findings and other clinical information.

4. Antral Follicle Count

An antral follicle count (AFC) is performed using transvaginal ultrasound and can help assess ovarian response and reserve.

5. Transvaginal Ultrasound

A transvaginal ultrasound can evaluate the uterus and ovaries and may identify conditions such as fibroids, ovarian cysts or other structural abnormalities.

6. HSG Test

Hysterosalpingography (HSG) is an imaging test used to assess the uterine cavity and whether the fallopian tubes are open.

Read more about the HSG test for infertility.

7. Sonohysterography

Sonohysterography uses ultrasound with fluid introduced into the uterus to assess the uterine cavity and, in some techniques, tubal patency.

8. Hysteroscopy

Hysteroscopy allows a doctor to directly examine the inside of the uterus and may be recommended when a uterine cavity problem is suspected.

9. Laparoscopy

Laparoscopy is a minimally invasive surgical procedure that may be considered in selected cases, particularly when conditions such as endometriosis or pelvic pathology are suspected.

It is not routinely required for every infertility evaluation.

Female Infertility Treatment

The appropriate female infertility treatment depends on the underlying cause, age, ovarian reserve, duration of infertility, previous pregnancy history, partner’s fertility status and other medical factors.

Treatment options may include:

Lifestyle and Preconception Care

Depending on an individual’s circumstances, improving overall health, maintaining a healthy weight, avoiding smoking and recreational drug use, and managing medical conditions may support reproductive health.

Ovulation-Induction Medicines

Women with ovulation disorders may be treated with medicines designed to help induce or regulate ovulation.

PCOS-related infertility is one situation in which ovulation-induction treatment may be considered.

Treatment for Endometriosis

Treatment for endometriosis depends on symptoms, disease severity, fertility goals and individual circumstances.

Surgery may be considered in selected cases, while assisted reproductive treatment may also be discussed.

Treatment for Tubal Problems

Treatment depends on the location and severity of tubal damage.

In selected cases, tubal surgery may be considered. For other patients, IVF may be an appropriate treatment option.

Treatment for Uterine Conditions

Fibroids, polyps, adhesions and other uterine abnormalities may require medical or surgical treatment depending on their size, location and impact on fertility.

IUI

Intrauterine insemination (IUI) involves placing prepared sperm into the uterus around the time of ovulation.

IUI may be considered for selected fertility problems depending on the couple’s diagnosis.

Learn more about IUI treatment in Srinagar.

IVF

In vitro fertilisation (IVF) involves retrieving eggs from the ovaries, fertilising them in a laboratory and transferring a resulting embryo into the uterus.

IVF may be considered for several fertility conditions, including some cases of tubal disease, endometriosis, diminished ovarian reserve and unexplained infertility.

Learn more about IVF treatment in Srinagar.

ICSI

Intracytoplasmic sperm injection (ICSI) involves injecting a single sperm directly into an egg during the laboratory fertilisation process.

ICSI is particularly relevant when male-factor infertility or previous fertilisation problems are present.

Read more about ICSI treatment in Srinagar.

Can Female Infertility Be Treated?

In many cases, fertility problems can be treated or managed once the underlying cause is identified.

However, treatment is highly individual. A treatment that is appropriate for one woman may not be appropriate for another.

Your fertility specialist may consider:

  • Age
  • Ovarian reserve
  • Ovulation
  • Fallopian tube status
  • Uterine health
  • Endometriosis
  • Previous pregnancies
  • Male-partner fertility
  • Duration of infertility
  • Previous treatment
  • Overall health

A comprehensive evaluation helps determine the most appropriate treatment pathway.

Frequently Asked Questions About Female Infertility

What is the most common cause of female infertility?

Ovulation disorders are an important cause of female infertility. PCOS is a leading cause of anovulatory infertility, but infertility can also result from tubal, uterine, endometriosis-related, hormonal, ovarian and other factors.

What are the first signs of female infertility?

There may be no obvious symptoms. Difficulty conceiving is often the main indication. Irregular periods, absent periods, severe pelvic pain or other reproductive symptoms may indicate an underlying condition that affects fertility.

Can PCOS cause infertility?

Yes. PCOS can interfere with regular ovulation and is a leading cause of infertility associated with ovulatory dysfunction.

Can endometriosis cause infertility?

Yes. Endometriosis can be associated with difficulty conceiving and may affect the reproductive organs through inflammation and other mechanisms.

What tests are done for female infertility?

Depending on the individual situation, testing may include ultrasound, AMH, antral follicle count, hormone testing, HSG, sonohysterography, hysteroscopy and other investigations.

Is AMH a fertility test?

AMH is primarily a marker used to assess ovarian reserve. It does not independently determine whether a woman can or cannot become pregnant. ASRM recommends interpreting ovarian-reserve testing in the context of the complete clinical picture.

When should I get an infertility test?

Women under 35 generally should consider evaluation after 12 months of trying without pregnancy. Women aged 35 or older should generally seek evaluation after 6 months, while women over 40 may benefit from more immediate evaluation. Earlier evaluation may be appropriate when there are known risk factors.

Can blocked fallopian tubes be treated?

Treatment depends on the location and severity of the blockage. Depending on the diagnosis, surgery or IVF may be considered.

Can female infertility be treated without IVF?

Yes. IVF is not required in every case. Depending on the cause, treatment may include lifestyle measures, ovulation-induction medicines, treatment of underlying conditions, surgery or IUI.

Female Infertility Treatment in Srinagar

If you are having difficulty conceiving, an appropriate fertility evaluation can help identify possible causes and guide treatment.

Imprimis IVF & Fertility Centre, Srinagar provides fertility evaluation and assisted reproductive treatment for couples seeking fertility care.

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: 19th September 2026

Clinic Information

Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: 2nd Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar – 190014
Services: Fertility evaluation, infertility treatment, IVF, IUI, ICSI and other assisted reproductive services
Phone: 9650777084 / 9797756111

For directions, appointment information and current clinic details, patients should use the clinic’s official contact channels.

Final Thoughts

Female infertility can have many different causes, and identifying the underlying factor is an important first step toward appropriate treatment.

Conditions such as PCOS, endometriosis, blocked fallopian tubes, uterine abnormalities, hormonal disorders and reduced ovarian reserve may affect fertility. Age is also an important factor in female reproductive potential.

If you have been trying to conceive without success, particularly if you are 35 or older or have a known fertility-related condition, consider discussing your situation with a qualified fertility specialist.

Medical Disclaimer: This page is intended for general educational purposes and does not replace an individual medical consultation, diagnosis or treatment plan. Fertility tests and treatment should be selected based on your medical history and a qualified healthcare professional’s evaluation.

Male Infertility: Causes, Symptoms, Tests & Treatment

Male infertility is more common than many people realise. When a couple has difficulty conceiving, fertility problems can involve the male partner, the female partner, or both partners. Therefore, evaluating male fertility is an important part of an infertility assessment.

Male fertility is closely related to sperm count, sperm motility and sperm morphology. Changes in any of these semen parameters can make it more difficult to achieve a pregnancy.

If you and your partner have been trying to conceive without success, understanding the causes, symptoms, diagnosis and treatment of male infertility can help you take the next step.

What Is Male Infertility?

Male infertility refers to difficulty achieving a pregnancy because of factors affecting the male reproductive system. A couple is generally evaluated for infertility when pregnancy has not occurred after 12 months of regular, unprotected sexual intercourse.

Male infertility may be related to problems with sperm production, sperm quality, sperm transport, ejaculation, hormones, genetics or the reproductive organs.

In some men, there are no obvious symptoms. A fertility evaluation may therefore be the first time an underlying problem is identified.

How Common Is Male Infertility?

Infertility affects couples across different age groups and populations, and male factors contribute to a substantial proportion of infertility cases.

Importantly, infertility should not automatically be considered a woman’s problem. Both partners should be evaluated when a couple is experiencing difficulty conceiving.

Male fertility can be affected by several factors, including age, medical conditions, lifestyle habits, hormonal disorders, infections, genetic conditions and problems affecting the testicles or reproductive tract.

What Causes Male Infertility?


The causes of male infertility can be broadly related to sperm production, sperm quality, hormonal function, reproductive anatomy, ejaculation and lifestyle factors.

Some of the most common male infertility causes include:

1. Low Sperm Count

Low sperm count, also called oligozoospermia, means the concentration of sperm in semen is below the laboratory’s reference range.

A low sperm count may reduce the chances of sperm reaching and fertilising an egg naturally. The severity and underlying cause are important when deciding on treatment.

Read more about low sperm count treatment in Srinagar.

2. Poor Sperm Motility

Sperm motility refers to the ability of sperm to move effectively.

Sperm need to move appropriately to travel through the female reproductive tract and reach the egg. Reduced sperm motility is known as asthenozoospermia and may make natural conception more difficult.

3. Abnormal Sperm Morphology

Sperm morphology describes the size and shape of sperm cells.

Abnormalities can involve the sperm head, midpiece or tail. A semen analysis evaluates sperm morphology along with other semen parameters.

Learn more about sperm morphology.

4. Hormonal Imbalance

Hormones play an important role in sperm production and male reproductive function.

Problems involving hormones produced by the hypothalamus, pituitary gland, thyroid or testes may affect sperm production and fertility. Hormone testing may be recommended when a doctor suspects an endocrine cause.

Read more about the role of hormones in fertility.

5. Varicocele

A varicocele is an enlargement of veins within the scrotum. It is relatively common and can sometimes be associated with impaired sperm production or semen quality.

Because sperm production is sensitive to temperature, changes in blood flow and testicular temperature may affect sperm function in some men.

6. Genetic Conditions

Certain genetic conditions can affect sperm production or the development of the male reproductive system.

Examples include Klinefelter syndrome, Kallmann syndrome, Kartagener syndrome and some genetic forms of cystic fibrosis-related infertility.

Genetic testing may be recommended in selected men, particularly when sperm counts are very low or sperm are absent from the semen.

7. Infections

Some infections, including sexually transmitted infections and infections affecting the reproductive tract, can interfere with sperm production or cause scarring and blockage of the reproductive tract.

Appropriate diagnosis and treatment are important when an infection is suspected.

8. Previous Surgery

Previous surgery involving the testicles, scrotum, prostate, bladder, abdomen or reproductive tract may sometimes affect sperm production, sperm transport or ejaculation.

A detailed medical and surgical history can help identify these factors.

9. Smoking and Alcohol

Lifestyle factors can influence male reproductive health.

Smoking and tobacco exposure may adversely affect sperm quality. Heavy alcohol consumption may also affect reproductive hormones and semen quality.

Men trying to improve their fertility should discuss alcohol, tobacco and other lifestyle factors with their healthcare professional.

10. Testicular Injury or Trauma

Previous injury or trauma to the testicles may affect sperm production or testicular function.

A history of significant testicular injury should be discussed during a fertility evaluation.

11. Retrograde Ejaculation

Normally, semen leaves the body through the penis during ejaculation. In retrograde ejaculation, semen enters the bladder instead.

This can result in little or no semen being ejaculated and may affect the ability to conceive naturally.

12. Testicular Tumours and Other Testicular Conditions

Some testicular tumours and other conditions affecting the testicles can interfere with normal sperm production.

Previous treatment for testicular cancer, including surgery, chemotherapy or radiation, can also affect fertility.

13. Medications, Drugs and Anabolic Steroids

Certain medications and recreational drugs can affect male reproductive function.

Of particular importance are anabolic steroids and testosterone supplementation, which can suppress the body’s natural sperm production.

Men using testosterone or other hormonal medicines should discuss fertility plans with their doctor before making changes to treatment.

14. Obesity and Excess Weight

Maintaining a healthy weight, eating a balanced diet and staying physically active can support overall reproductive health.

15. Excessive Physical or Training Load

Regular physical activity is generally beneficial. However, extreme training, inadequate nutrition and overtraining may affect hormonal balance and reproductive function in some individuals.

16. Chronic Stress and Poor Sleep

Long-term stress and inadequate sleep can affect overall health and may influence hormonal and reproductive function.

Managing stress, maintaining adequate sleep and following a healthy lifestyle can form part of a broader approach to improving fertility.

Male Infertility Symptoms

One of the challenges with male infertility is that many men have no obvious symptoms.

In other cases, symptoms may provide clues to an underlying condition.

Possible signs and symptoms include:

  • Difficulty achieving or maintaining an erection
  • Reduced sexual desire
  • Problems with ejaculation
  • Little or no semen during ejaculation
  • Pain, swelling or a lump in the testicle or scrotum
  • Recurrent genital or urinary infections
  • Reduced facial or body hair
  • Enlarged breast tissue
  • A history of testicular problems or surgery
  • Difficulty conceiving despite regular unprotected intercourse

Experiencing one of these symptoms does not necessarily mean that a man is infertile. A proper medical evaluation is needed to identify the cause.

How Is Male Infertility Diagnosed?

The diagnosis of male infertility usually begins with a detailed medical and reproductive history followed by appropriate tests.

A fertility specialist may ask about:

  • Previous pregnancies
  • Duration of infertility
  • Sexual and ejaculation history
  • Previous surgeries
  • Testicular injuries
  • Medications and supplements
  • Lifestyle factors
  • Previous infections
  • Family history
  • Previous fertility treatments

The results help determine which additional investigations may be appropriate.

Male Infertility Tests

Semen Analysis

Semen analysis is one of the most important initial tests for evaluating male fertility.

It assesses factors such as:

  • Sperm concentration
  • Total sperm number
  • Sperm motility
  • Sperm morphology
  • Semen volume
  • Other semen characteristics

A single semen analysis may not provide the complete picture because semen parameters can vary between samples. Your doctor may therefore recommend repeat testing.

You can also explore infertility tests in Srinagar.

Hormone Testing

Blood tests may be used to evaluate reproductive hormones such as testosterone, FSH and LH, depending on the clinical situation.

Hormonal testing can help identify conditions affecting sperm production.

Scrotal Ultrasound and Doppler

A scrotal ultrasound or Doppler study may help evaluate the testicles, epididymis, blood flow and conditions such as varicocele.

Transrectal Ultrasound

A transrectal ultrasound, or TRUS, may be recommended in selected cases when a doctor suspects a blockage involving the ejaculatory ducts or other structures.

Genetic Testing

Genetic tests may be recommended for certain men with severe sperm-production problems, particularly very low sperm counts or azoospermia.

Testicular Biopsy

In selected cases, a testicular biopsy may help determine whether sperm production is occurring within the testicular tissue.

Can Male Infertility Be Treated?

Yes. Male infertility treatment depends on the underlying cause.

Some men may benefit from lifestyle changes or medicines, while others may require surgery or assisted reproductive techniques such as IVF and ICSI.

Treatment should be based on a proper diagnosis rather than simply treating the semen report.

Male Infertility Treatment Options

Lifestyle Changes

Depending on the cause, a doctor may recommend:

  • Stopping tobacco use
  • Limiting excessive alcohol consumption
  • Maintaining a healthy weight
  • Following a balanced diet
  • Regular moderate physical activity
  • Managing stress
  • Getting adequate sleep
  • Avoiding unnecessary exposure to excessive heat
  • Reviewing medicines that may affect fertility with a doctor

Medicines and Hormonal Treatment

When hormonal abnormalities or specific medical conditions are identified, appropriate medicines may help improve reproductive function.

Hormonal treatment should only be taken under medical supervision.

Varicocele Treatment

When a clinically significant varicocele is associated with infertility, a specialist may consider varicocele repair in selected patients.

Vasovasostomy

A vasovasostomy is a surgical procedure used to reconnect the vas deferens, commonly after a previous vasectomy.

Vasoepididymostomy

A vasoepididymostomy connects the vas deferens to the epididymis and may be considered when there is an obstruction that prevents sperm from entering the semen.

Transurethral Resection of the Ejaculatory Duct

In selected cases involving ejaculatory duct obstruction, a transurethral procedure may be considered to improve sperm passage.

IVF for Male Infertility

In vitro fertilisation (IVF) may be considered when male-factor infertility is significant or when other fertility treatments have not been successful.

During IVF, eggs are retrieved from the ovaries and fertilisation takes place in a laboratory. The resulting embryo can then be transferred into the uterus.

Learn more about IVF treatment in Srinagar.

ICSI for Male Infertility

Intracytoplasmic sperm injection (ICSI) is an advanced fertilisation technique commonly used when sperm-related factors make conventional fertilisation difficult.

During ICSI, a single selected sperm is injected directly into a mature egg in the laboratory.

ICSI may be considered in situations such as:

  • Very low sperm count
  • Poor sperm motility
  • Severe sperm morphology abnormalities
  • Previous fertilisation failure
  • Surgically retrieved sperm
  • Certain cases of severe male-factor infertility

Read more about ICSI treatment in Srinagar.

Sperm Retrieval Procedures for Male Infertility

Some men produce sperm inside the testicles but have little or no sperm in the ejaculated semen. In such cases, sperm retrieval may be considered for use with IVF-ICSI.

Common sperm retrieval procedures include:

TESA

Testicular Sperm Aspiration (TESA) uses a needle to obtain sperm-containing tissue from the testicle.

PESA

Percutaneous Epididymal Sperm Aspiration (PESA) retrieves sperm from the epididymis using a needle.

TESE

Testicular Sperm Extraction (TESE) involves obtaining a small amount of testicular tissue to look for sperm.

Learn more about TESE and its success rate.

MESA

Microsurgical Epididymal Sperm Aspiration (MESA) uses microsurgical techniques to retrieve sperm from the epididymis.

MicroTESE

Microdissection TESE (microTESE) uses an operating microscope to identify areas of the testicle that may contain sperm.

The most appropriate sperm retrieval technique depends on the individual’s diagnosis and whether sperm production is present.

Donor Sperm Treatment

When sperm cannot be obtained or when other treatment options are not appropriate, donor sperm treatment may be considered in accordance with applicable medical and legal requirements.

Your fertility specialist can explain the available options, eligibility requirements and treatment process.

When Should a Man Get a Fertility Test?

A male fertility evaluation may be appropriate when:

  • The couple has been trying to conceive for 12 months without pregnancy
  • There is a known history of low sperm count
  • There is a history of testicular injury or surgery
  • There are ejaculation or erectile problems
  • There is a history of reproductive or urinary infection
  • The man has used testosterone or anabolic steroids
  • There is a known hormonal or genetic condition
  • The female partner’s age or fertility history makes earlier evaluation advisable

Both partners may need evaluation because infertility can involve male factors, female factors, or a combination of both.

Can Male Infertility Be Prevented?

Not every cause of male infertility can be prevented, particularly genetic or congenital conditions. However, maintaining overall health may help protect reproductive health.

Helpful measures may include:

  • Avoiding tobacco and recreational drugs
  • Limiting excessive alcohol consumption
  • Maintaining a healthy body weight
  • Exercising regularly without excessive training
  • Managing chronic medical conditions
  • Avoiding unnecessary testosterone or anabolic steroid use
  • Seeking treatment for reproductive or urinary infections
  • Protecting the testicles from significant injury
  • Discussing fertility preservation before treatments that may affect sperm production

Frequently Asked Questions About Male Infertility

What is the main cause of male infertility?

There is no single cause. Male infertility may result from low sperm count, poor sperm motility, abnormal sperm morphology, hormonal problems, varicocele, genetic conditions, reproductive tract obstruction, infections, medications, lifestyle factors or problems with sperm production.

What are the signs of male infertility?

Many men have no noticeable symptoms. When symptoms occur, they may include ejaculation problems, erectile dysfunction, reduced libido, testicular pain or swelling, or changes in semen volume.

Which test is used for male infertility?

A semen analysis is usually one of the first investigations used to assess male fertility. Additional tests, such as hormone testing, ultrasound, Doppler studies, or genetic testing, may be recommended depending on the findings.

Can low sperm count be treated?

Treatment depends on the cause and severity. Depending on the diagnosis, options may include lifestyle changes, medicines, treatment of an underlying condition, surgery, sperm retrieval or assisted reproductive techniques such as IVF-ICSI.

Can a man with zero sperm count have a baby?

In some cases, yes. Men with azoospermia may still produce sperm in the testicles. Depending on the cause, sperm retrieval techniques such as TESE or microTESE may be considered, often together with ICSI.

Is IVF required for every case of male infertility?

No. Treatment depends on the underlying cause. Some men may improve with lifestyle changes, medicines or surgery. Assisted reproductive techniques may be considered when other approaches are not suitable or have not worked.

Is ICSI better than IVF for male infertility?

IVF and ICSI are different fertilisation approaches. ICSI may be particularly useful when there is significant male-factor infertility or when sperm-related problems make conventional fertilisation difficult. The appropriate technique should be decided based on the couple’s clinical circumstances.

Take the Next Step for Male Infertility

Male infertility can have several possible causes, and a semen report alone does not always explain the complete picture. A proper evaluation can help identify whether the issue involves sperm production, sperm quality, hormones, anatomy, ejaculation or another factor.

If you or your partner are having difficulty conceiving, consider consulting a fertility specialist for an individual assessment. At Imprimis IVF & Fertility Centre, fertility evaluation and treatment options are discussed based on your medical history, test results, and reproductive goals.

Explore male fertility and infertility care or consult a fertility specialist to understand the next appropriate step.

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: September 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: Second Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu and Kashmir – 190014
Phone: 7678556881, 9650777084

Sperm Morphology: Normal Range, Test Results & Fertility

Have you received a semen analysis report showing 2% normal sperm morphology? If so, you may be wondering what this number means, whether it can affect your chances of pregnancy, and whether you need sperm morphology treatment.

Sperm morphology is one of the important parameters evaluated during a semen analysis. It describes the size and shape of sperm cells and whether they have a typical structure.

A low morphology result does not automatically mean infertility. Male fertility depends on several factors, including sperm concentration, motility, morphology, overall sperm function, and the fertility status of both partners. The AUA/ASRM guideline notes that an individual semen parameter, including morphology, is generally not sufficient by itself to diagnose infertility.

If your semen analysis shows abnormal sperm morphology, a fertility specialist can help determine whether further evaluation or treatment is appropriate.

What Is Sperm Morphology?

Sperm morphology refers to the shape and structure of sperm cells.

A sperm cell has three main parts:

  • Head
  • Midpiece
  • Tail

Each part plays an important role in sperm function.

The head contains the genetic material and the acrosome, which contains enzymes involved in the process of fertilisation. The midpiece contains structures that provide energy for movement, while the tail helps the sperm move through the female reproductive tract.

During a semen analysis, the laboratory examines sperm under a microscope and estimates the percentage that meet the criteria for normal morphology.

The assessment is commonly performed using strict morphological criteria. The WHO’s sixth edition laboratory manual provides standardized methods for semen examination and reports a lower reference limit of 4% normal forms for sperm morphology.

Sperm Morphology Normal Range

One of the most common questions after receiving a semen analysis report is:

“What is the normal sperm morphology percentage?”

According to the WHO sixth edition reference material, the lower reference limit for morphologically normal sperm forms is 4% when assessed using the standardized criteria described in the manual.

This means that a morphology result below 4% may be reported as below the reference limit.

However, this number should not be interpreted as a simple fertility cut-off.

For example, if your report shows 2% normal morphology, it does not automatically mean that you are infertile or that pregnancy is impossible.

Your doctor will consider the complete semen analysis, including:

  • Sperm concentration
  • Total sperm number
  • Progressive motility
  • Total motility
  • Sperm morphology
  • Semen volume
  • Clinical history
  • Fertility factors affecting both partners

The WHO also emphasizes that semen reference values should not be treated as a strict boundary between fertile and infertile men.

What Does Normal Sperm Look Like?

A sperm with typical morphology generally has:

  • An oval-shaped head
  • A clearly defined acrosome
  • A relatively regular midpiece
  • A long, uncoiled tail
  • Appropriate proportions between its different parts

Not every sperm produced by a healthy man will have a typical shape. In fact, sperm morphology naturally varies considerably between individual sperm cells.

This is why the morphology result represents the percentage of sperm classified as normal, rather than saying that every sperm must have a perfect shape.

What Is Abnormal Sperm Morphology?

Abnormal sperm morphology, sometimes called teratozoospermia, refers to a higher proportion of sperm with atypical structural features.

Abnormalities can affect different parts of the sperm.

Head Abnormalities

Examples include:

  • Abnormally large or small heads
  • Elongated heads
  • Irregular head shapes
  • Abnormal acrosome
  • Vacuoles or other structural abnormalities

Midpiece Abnormalities

The midpiece may be:

  • Thickened
  • Bent
  • Asymmetrical
  • Irregularly attached to the head

Tail Abnormalities

The sperm tail may be:

  • Short
  • Bent
  • Coiled
  • Irregular
  • Abnormally shaped

Some sperm may have abnormalities involving more than one part of the cell.

Does Low Sperm Morphology Mean Infertility?

No. Low sperm morphology alone does not prove infertility.

This is one of the most important points to understand when reading a semen analysis report.

A man may have a low morphology percentage and still achieve pregnancy. Conversely, a man with a morphology result within the reference range may still experience fertility problems because of other factors.

AUA/ASRM guidance states that individual semen parameters such as concentration, motility, and morphology are generally not highly predictive of fertility when considered in isolation. The likelihood of infertility tends to increase when multiple semen parameters are abnormal.

Therefore, if your sperm morphology is 2%, 3%, or another low value, discuss the complete semen analysis with a fertility specialist rather than focusing solely on morphology.

What Causes Abnormal Sperm Morphology?

Several factors may be associated with abnormal sperm morphology. Sometimes, however, no single cause can be identified.

Possible factors include:

Age

Sperm quality can change with age. Changes in reproductive health and hormonal function may influence semen parameters.

Age should therefore be considered as part of the overall fertility evaluation.

Obesity and Excess Weight

Excess body weight may be associated with hormonal and metabolic changes that can affect male reproductive health.

Maintaining a healthy weight, following a balanced diet and staying physically active may support overall reproductive health.

Stress

Chronic stress can affect overall health, sleep, lifestyle habits, and hormonal function.

Although stress should not be considered the sole explanation for abnormal morphology, managing long-term stress is an important part of a healthy lifestyle.

Smoking and Alcohol

Smoking and excessive alcohol consumption may negatively affect male reproductive health.

If you are trying to conceive, reducing or avoiding tobacco and excessive alcohol can be an important part of improving overall reproductive health.

Recreational Drugs and Anabolic Steroids

Certain recreational drugs and anabolic steroids can interfere with normal reproductive function.

Men planning a pregnancy should avoid self-medication and should discuss testosterone or steroid use with a qualified doctor.

Diabetes and Metabolic Health

Diabetes and other metabolic conditions can affect male reproductive health.

If you have diabetes, maintaining appropriate blood glucose control and following your doctor’s treatment plan are important for overall health.

Genetic Factors

Some genetic conditions can affect sperm production and sperm characteristics.

Genetic evaluation may be considered in selected men, particularly when semen abnormalities are severe or accompanied by very low sperm counts or azoospermia.

Exposure to Chemicals

Occupational or environmental exposure to certain chemicals, pesticides, solvents, and heavy metals may affect reproductive health.

If your work involves regular exposure to such substances, discuss appropriate precautions with your doctor.

Heat Exposure

Sperm production is sensitive to temperature.

Repeated or prolonged exposure to excessive heat around the testicles may affect sperm production in some men.

Discuss occupational or lifestyle heat exposure with your fertility specialist if it may be relevant to your situation.

How Is Abnormal Sperm Morphology Diagnosed?

The main test used to assess sperm morphology is a semen analysis.

A semen analysis evaluates several sperm and semen parameters, including:

  • Sperm concentration
  • Total sperm number
  • Sperm motility
  • Progressive motility
  • Sperm morphology
  • Semen volume

If the result is abnormal, your fertility specialist may recommend another semen analysis because semen parameters can vary between samples.

The AUA/ASRM guideline recommends semen analysis as part of the initial male fertility evaluation and recommends further assessment by a male reproductive specialist when one or more semen parameters are abnormal.

Depending on your history and test results, additional evaluation may include:

  • Physical examination
  • Hormonal testing
  • Testicular or scrotal assessment
  • Evaluation for varicocele
  • Genetic testing in selected cases
  • Assessment of other male infertility factors

For more information, see our infertility tests page in Srinagar.

Abnormal Sperm Morphology Treatment

There is no single medicine that can guarantee an improvement in sperm morphology.

Treatment depends on the underlying cause, the complete semen analysis results, and the couple’s fertility goals.

The treatment approach may include lifestyle changes, treatment of an underlying medical condition, or assisted reproductive techniques.

Lifestyle Changes to Support Sperm Health

Healthy lifestyle habits can support overall reproductive health.

Important measures include:

  • Maintain a healthy body weight
  • Eat a balanced and nutritious diet
  • Exercise regularly
  • Avoid smoking and tobacco
  • Limit excessive alcohol consumption
  • Avoid recreational drugs
  • Avoid anabolic steroids unless medically indicated and supervised
  • Get adequate sleep
  • Manage chronic stress
  • Avoid unnecessary heat exposure
  • Take medicines only under medical supervision

Remember that lifestyle changes are not a guaranteed treatment for abnormal morphology. Their role is to support overall health and address potentially modifiable factors.

How Long Does It Take to Improve Sperm Quality?

Sperm production is a continuous biological process, so improvements in semen parameters generally cannot be assessed immediately after making a lifestyle change.

A fertility specialist may recommend reassessing semen parameters after an appropriate interval based on your individual circumstances.

Do not assume that a particular supplement or lifestyle change will automatically increase your morphology percentage.

If your semen analysis remains abnormal, professional evaluation can help determine the next step.

Can Supplements Improve Sperm Morphology?

You may see many products online claiming to improve sperm morphology or “increase normal sperm” quickly.

Be careful with these claims.

Some doctors may recommend specific nutritional supplements in selected patients, but supplements are not a guaranteed treatment for abnormal sperm morphology.

Do not take high-dose vitamins, antioxidants, hormones, or fertility supplements without discussing them with a qualified doctor.

IUI for Abnormal Sperm Morphology

Intrauterine insemination (IUI) involves processing a semen sample in the laboratory and placing prepared sperm directly into the uterus around ovulation.

Whether IUI is appropriate depends on several factors, including:

  • Sperm concentration
  • Sperm motility
  • Total motile sperm count
  • Female partner’s age
  • Ovulation
  • Fallopian tube status
  • Duration of infertility
  • Other fertility factors

A low morphology percentage alone does not automatically mean that IUI cannot be used.

Learn more about IUI treatment in Srinagar.

IVF for Abnormal Sperm Morphology

In vitro fertilization (IVF) involves retrieving eggs from the ovaries and fertilizing them with sperm in a laboratory.

IVF may be considered when:

  • Multiple fertility factors are present
  • Other fertility treatments have not worked
  • There is significant male-factor infertility
  • The couple’s overall fertility evaluation supports IVF

Your fertility specialist will determine whether conventional IVF fertilization or ICSI is more appropriate.

Read more about IVF treatment in Srinagar.

ICSI for Poor Sperm Morphology

Intracytoplasmic sperm injection (ICSI) is a specialized fertilization technique performed during an IVF cycle.

During ICSI, an embryologist selects a viable sperm and injects it directly into the egg to assist fertilization.

ICSI may be considered when there are significant male-factor abnormalities, particularly when sperm concentration or motility is also severely affected or when previous fertilization problems have occurred.

However, low morphology alone does not automatically mean that ICSI is required. The decision should be based on the complete clinical picture.

Learn more about ICSI treatment in Srinagar.

Can You Get Pregnant With 2% Sperm Morphology?

Yes, pregnancy may still be possible when a semen analysis shows 2% normal sperm morphology.

A 2% morphology result means that approximately 2% of the sperm assessed met the laboratory’s criteria for normal morphology. It does not mean that only 2% of the sperm can fertilise an egg, nor does it independently diagnose infertility.

The rest of the semen analysis matters.

For example, your doctor may also consider:

  • Total sperm count
  • Sperm concentration
  • Progressive motility
  • Total motility
  • Semen volume
  • Female partner’s age and fertility
  • Duration of infertility
  • Previous pregnancies or fertility treatments

If several semen parameters are abnormal, the likelihood of fertility problems may be higher.

When Should You See a Fertility Specialist?

Consider consulting a fertility specialist if:

  • Your semen analysis shows low sperm morphology
  • Morphology is accompanied by low sperm count
  • Sperm motility is also low
  • You have been trying to conceive without success
  • You have azoospermia or severe oligospermia
  • You have testicular pain, swelling or a lump
  • You have erectile or ejaculation problems
  • You have a history of testicular surgery or injury
  • You have concerns about male fertility

The AUA/ASRM guideline recommends evaluation by a male reproductive expert for men with one or more abnormal semen parameters or presumed male infertility.

Sperm Morphology Treatment in Srinagar at Imprimis IVF

If you are searching for sperm morphology treatment in Srinagar, the first step is to understand your complete semen-analysis report rather than focusing on one number.

At Imprimis IVF & Fertility Centre, Srinagar, a fertility evaluation can help assess male and female fertility factors and determine whether further testing or treatment may be appropriate.

Depending on the diagnosis, fertility management may include lifestyle guidance, treatment of an underlying medical condition, IUI, IVF or ICSI.

The appropriate treatment varies from couple to couple and should be based on medical evaluation.

For broader information, explore our infertility treatment in Srinagar resources.

Frequently Asked Questions About Sperm Morphology

What is sperm morphology?

Sperm morphology refers to the size, shape and structural characteristics of sperm cells. It is one of the parameters assessed during semen analysis.

What is the normal sperm morphology range?

The WHO sixth edition laboratory manual gives a lower reference limit of 4% normal forms when morphology is assessed using the standardized criteria described in the manual.

Is 2% sperm morphology considered low?

A result of 2% is below the WHO reference limit of 4% for normal forms. However, morphology alone does not diagnose infertility. The complete semen analysis and the fertility status of both partners should be considered.

Can I get pregnant with 2% normal sperm morphology?

Yes, pregnancy may still be possible. A 2% morphology result does not by itself mean that natural conception is impossible.

Can sperm morphology be improved naturally?

Healthy lifestyle habits may support overall sperm health, including maintaining a healthy weight, exercising, avoiding smoking and excessive alcohol, getting adequate sleep and managing health conditions. However, there is no guaranteed natural treatment that can normalize sperm morphology.

Is ICSI required for low sperm morphology?

Not necessarily. ICSI may be considered when significant male-factor infertility is present, but low morphology alone does not automatically mean that ICSI is required.

Is abnormal sperm morphology the same as male infertility?

No. Abnormal morphology is a semen-analysis finding. Male infertility is a broader clinical condition that depends on the couple’s ability to achieve pregnancy and the overall fertility evaluation.

How is sperm morphology tested?

Sperm morphology is assessed as part of a semen analysis in a laboratory. The laboratory evaluates sperm shape and structure using standardized methods.

Medical Review & Author Information

Medically Reviewed By: Imprimis IVF Fertility Specialist Team
Speciality: Reproductive Medicine, IVF & Male Infertility
Clinic: Imprimis IVF & Fertility Centre, Srinagar

This article provides general information about sperm morphology, semen analysis, male infertility, IUI, IVF and ICSI. Individual test results can vary, and treatment recommendations should be based on a qualified fertility specialist’s evaluation.

Last Updated: September 2026

Conclusion

Abnormal sperm morphology can be concerning when you first see it on a semen analysis report, but a low morphology percentage does not automatically mean infertility.

If your report shows 2% normal morphology or another low value, look at the complete semen analysis rather than focusing on morphology alone. Sperm concentration, motility, total sperm number and the fertility status of both partners can all influence the chances of conception.

If you are looking for morphology treatment in Srinagar, a fertility specialist can help identify possible contributing factors and explain whether lifestyle changes, further testing, IUI, IVF or ICSI may be appropriate for your situation.

Low Sperm Count: Causes, Treatment & How to Improve It

Trying to conceive but struggling with low sperm count? If you are searching for low sperm count treatment in Srinagar, you are not alone. Low sperm count is one of the factors that can contribute to male infertility, but it does not automatically mean that natural pregnancy is impossible.

The good news is that several treatment options are available depending on the underlying cause, sperm count, sperm motility, sperm morphology and the fertility status of both partners.

At Imprimis IVF & Fertility Centre, Srinagar, a detailed fertility evaluation can help identify possible male fertility factors and determine whether lifestyle changes, medical treatment, IUI, IVF or ICSI may be appropriate.

If a semen analysis has shown a low sperm count, the first step is to understand what the result means and why it may have occurred.

What Is Low Sperm Count?

Low sperm count means that the concentration or number of sperm in the semen is below the reference range used for semen analysis.

A semen analysis does more than simply count sperm. It generally evaluates several important parameters, including:

  • Semen volume
  • Sperm concentration
  • Total sperm number
  • Sperm motility
  • Progressive motility
  • Sperm morphology

A single semen parameter does not determine whether a man is fertile or infertile. The complete semen analysis should be interpreted along with medical history, physical examination and the fertility status of both partners.

This is particularly important because sperm count and sperm quality can vary between semen samples.

What Is Oligospermia?

Oligospermia, also called oligozoospermia, is the medical term used for a low sperm concentration.

It is diagnosed through semen analysis, which is one of the most important tests used during the evaluation of male infertility.

Depending on the individual case, a fertility specialist may recommend repeating the semen analysis to confirm an abnormal result and assess other sperm parameters.

Oligospermia may occur along with other sperm abnormalities, including:

  • Asthenozoospermia: reduced sperm motility
  • Teratozoospermia: abnormal sperm morphology
  • Oligoasthenoteratozoospermia (OAT): abnormalities involving sperm concentration, motility and morphology
  • Cryptozoospermia: extremely rare sperm detected after laboratory processing
  • Azoospermia: no sperm detected in the ejaculate

Understanding the complete semen profile is important when deciding whether treatment or assisted reproductive techniques may be required.

Can Low Sperm Count Cause Male Infertility?

Yes. Low sperm count can contribute to male factor infertility because fewer sperm may be available to travel through the female reproductive tract and reach the egg.

However, male fertility depends on more than sperm concentration.

Doctors may also consider:

  • Sperm motility
  • Sperm morphology
  • Total motile sperm count
  • Sperm production
  • Hormonal health
  • Testicular health
  • Ejaculation and sperm transport
  • The female partner’s reproductive health
  • Age of both partners
  • Duration of infertility

For this reason, both partners may need a fertility evaluation.

If you are experiencing difficulty conceiving, a comprehensive male and female infertility evaluation can help identify possible causes and guide treatment.

Symptoms of Low Sperm Count

Symptoms of Low Sperm Count

Low sperm count often does not cause obvious symptoms. Many men discover that they have low sperm count only after undergoing fertility testing.

Difficulty conceiving may be the first noticeable sign.

Some men may also experience symptoms related to an underlying medical condition, such as:

  • Reduced sexual desire
  • Erectile difficulties
  • Problems with ejaculation
  • Testicular pain or discomfort
  • Testicular swelling or a lump
  • Reduced facial or body hair
  • Signs of hormonal imbalance

These symptoms do not necessarily mean that sperm count is low. A semen analysis and medical evaluation are needed to identify the actual cause.

What Causes Low Sperm Count?

Causes Low Sperm Count

Low sperm count can have several possible causes. Medical conditions, hormonal problems, genetic factors, environmental exposure, and lifestyle habits may all play a role.

Varicocele

A varicocele is an enlargement of veins within the scrotum around the testicle.

In some men, varicocele may affect the testicular environment and sperm production. It is one of the potentially treatable factors associated with male infertility.

A fertility specialist can determine whether a varicocele may be contributing to abnormal semen parameters.

Hormonal Imbalance

Hormones have an important role in sperm production.

Problems involving the hypothalamus, pituitary gland, or testes can interfere with the hormonal signals required for normal sperm production.

Depending on the medical history and semen analysis results, a doctor may recommend hormonal tests such as testosterone, FSH, and LH.

Hormonal treatment should only be taken after proper medical evaluation.

Infections

Certain infections can affect the male reproductive system and may interfere with sperm production, sperm function, or the transport of sperm.

Some infections can also cause inflammation or scarring within the reproductive tract.

If an infection is suspected, the doctor may recommend appropriate testing and treatment.

Problems With Sperm Production

The testicles produce sperm. Conditions affecting testicular function can reduce sperm production.

Possible factors include:

  • Testicular injury
  • Certain medical conditions
  • Previous infections
  • Hormonal disorders
  • Genetic conditions
  • Certain medications or treatments

Severe problems with sperm production may result in very low sperm counts or azoospermia.

Blockage in the Reproductive Tract

Sometimes sperm production may occur normally inside the testicles, but sperm may be unable to enter the ejaculate because of a blockage.

This can lead to obstructive azoospermia.

The location and cause of the blockage need to be evaluated before deciding on treatment.

Previous Surgery or Injury

Certain surgeries or injuries involving the testicles, scrotum, prostate, bladder, pelvis, or reproductive tract may affect sperm production, sperm transport, or ejaculation.

A detailed medical history can help a fertility specialist identify whether previous surgery or injury may be relevant.

Obesity and Excess Weight

Excess body weight may be associated with hormonal changes and other health conditions that can affect male reproductive health.

Maintaining a healthy weight through a balanced diet and regular physical activity can support overall health and may also benefit reproductive health.

Weight management should be viewed as part of a broader fertility plan rather than a guaranteed treatment for low sperm count.

Heat Exposure

Normal sperm production requires an appropriate testicular temperature.

Repeated or prolonged exposure to excessive heat may affect sperm production in some men.

If your work or lifestyle involves significant heat exposure, discuss it with your fertility specialist.

Smoking, Alcohol and Substance Use

Smoking and excessive alcohol consumption can negatively affect overall health and may be associated with impaired male reproductive function.

Recreational drugs and anabolic steroids can also interfere with normal hormone production and sperm formation.

Men planning to conceive should avoid self-medication, particularly testosterone or anabolic steroid use. Testosterone treatment can suppress sperm production and should only be considered under appropriate medical supervision.

Stress and Poor Lifestyle Habits

Chronic stress, inadequate sleep, physical inactivity, and an unhealthy diet can affect overall health.

A healthy lifestyle can support general reproductive health and may form an important part of a comprehensive male infertility treatment plan.

How Is Low Sperm Count Diagnosed?

The main investigation for low sperm count is a semen analysis.

A semen analysis evaluates several characteristics of the semen and sperm, including:

  • Sperm concentration
  • Total sperm number
  • Sperm motility
  • Progressive motility
  • Sperm morphology
  • Semen volume

Because semen parameters can vary, your doctor may recommend a repeat test when the initial result is abnormal.

Depending on your symptoms, medical history, and semen-analysis results, further evaluation may include:

  • Physical examination
  • Hormonal blood tests
  • Testicular or scrotal evaluation
  • Assessment for varicocele
  • Genetic testing in selected cases
  • Evaluation for reproductive-tract blockage
  • Additional male infertility investigations

A comprehensive evaluation helps determine whether the low sperm count has a potentially treatable cause.

Can You Get Pregnant With a Low Sperm Count?

Yes, pregnancy can still be possible with a low sperm count.

The possibility of pregnancy depends on several factors, including the number of sperm, sperm movement, sperm morphology, the underlying cause, and the fertility status of the female partner.

Some couples may conceive naturally after addressing an underlying problem or improving relevant lifestyle factors.

For others, fertility treatment may be recommended.

Depending on the individual case, options may include:

  • Medical treatment
  • Lifestyle modification
  • IUI
  • IVF
  • ICSI
  • Sperm retrieval procedures in selected cases

The appropriate treatment should be determined after evaluating both partners.

Low Sperm Count Treatment

Treatment for low sperm count depends largely on the underlying cause and severity of the sperm abnormality.

There is no single treatment that works for every man.

A fertility specialist may recommend lifestyle changes, treatment of an underlying condition, or assisted reproductive techniques such as IUI, IVF, or ICSI.

Lifestyle Changes

Healthy lifestyle habits may support overall male reproductive health.

Helpful measures may include:

  • Maintaining a healthy body weight
  • Eating a balanced and nutritious diet
  • Exercising regularly
  • Avoiding smoking
  • Limiting excessive alcohol consumption
  • Avoiding recreational drugs
  • Managing stress
  • Getting adequate sleep
  • Avoiding unnecessary heat exposure
  • Taking medicines only as prescribed

Do not start testosterone, fertility medicines, or supplements without consulting a qualified doctor.

Treatment of an Underlying Medical Condition

If an underlying medical condition is contributing to low sperm count, treating that condition may be an important part of fertility management.

Depending on the diagnosis, treatment may involve:

  • Medical therapy
  • Hormonal treatment in selected cases
  • Treatment of infection
  • Surgical treatment of selected conditions
  • Treatment of varicocele where appropriate
  • Management of other health conditions

The treatment should always be based on an individual medical assessment.

IUI for Low Sperm Count

Intrauterine insemination (IUI) is an assisted reproductive technique in which a semen sample is processed in the laboratory and prepared sperm are placed directly into the uterus around the time of ovulation.

IUI may be considered for selected couples with mild male-factor infertility when the available motile sperm are considered suitable.

When the sperm count or total motile sperm count is very low, IUI may be less suitable, and the fertility specialist may discuss IVF with ICSI.

Learn more about IUI treatment in Srinagar.

IVF for Low Sperm Count

In vitro fertilisation (IVF) is an assisted reproductive treatment in which eggs are collected from the ovaries and fertilised with sperm in a laboratory.

IVF may be considered when:

  • Male-factor infertility is significant
  • Other fertility factors are present
  • Previous fertility treatment has not resulted in pregnancy
  • The overall fertility assessment indicates IVF

During an IVF cycle, the resulting embryo may be transferred into the uterus when the fertility specialist considers it appropriate.

Read more about IVF treatment in Srinagar.

ICSI for Low Sperm Count

Intracytoplasmic sperm injection (ICSI) is a specialised fertilisation technique performed as part of an IVF cycle.

During ICSI, an embryologist injects a single viable sperm directly into an egg to assist fertilisation.

ICSI may be considered in cases of significant male factor infertility, including very low sperm numbers or certain severe sperm abnormalities.

In selected men with very few or no sperm in the ejaculate, sperm may be obtained through a sperm-retrieval procedure and used for ICSI.

Learn more about ICSI treatment in Srinagar.

Low Sperm Count, Severe Oligospermia and Azoospermia

Not every man with a low sperm count requires the same treatment.

Severe oligospermia means sperm concentration is substantially reduced, while azoospermia means that no sperm are detected in the ejaculate.

Azoospermia can have different causes, including:

  • Blockage in the reproductive tract
  • Problems with sperm production
  • Hormonal disorders
  • Genetic conditions
  • Testicular problems

Men with severe oligospermia or azoospermia may require a detailed male fertility evaluation.

In selected cases, genetic testing, hormonal testing, imaging, or sperm retrieval procedures may be recommended.

If you have been diagnosed with azoospermia, learn more about azoospermia treatment.

When Should You See a Male Infertility Specialist?

Consider consulting a male infertility specialist if:

  • You have been trying to conceive without success
  • Your semen analysis shows low sperm count
  • Sperm motility or morphology is abnormal
  • You have been diagnosed with azoospermia
  • You have testicular pain, swelling, or a lump
  • You have erectile or ejaculation difficulties
  • You have a history of testicular injury or surgery
  • You have concerns about your reproductive health
  • You have previously undergone unsuccessful fertility treatment

Early evaluation can help identify potentially treatable causes and clarify which fertility treatment options may be appropriate.

For a broader fertility evaluation, you can explore infertility tests in Srinagar.

Low Sperm Count Treatment at Imprimis IVF

If you are looking for low sperm count treatment in Srinagar, the first step is understanding the reason behind the abnormal semen analysis result.

At Imprimis IVF & Fertility Centre, Srinagar, male and female fertility factors can be evaluated to help develop an individualized treatment plan.

Depending on the diagnosis, treatment may include lifestyle guidance, medical management, IUI, IVF, ICSI or other assisted reproductive techniques.

Our fertility team can also evaluate conditions associated with male factor infertility, including low sperm count, abnormal sperm motility, severe sperm abnormalities and azoospermia.

Explore our male infertility treatment resources to learn more about male reproductive health and fertility treatment.

Frequently Asked Questions About Low Sperm Count

What is considered a low sperm count?

A low sperm count refers to sperm concentration or total sperm number below the applicable laboratory reference range. A semen analysis should be interpreted together with sperm motility, morphology and the overall clinical picture.

Can you get pregnant with a low sperm count?

Yes. Pregnancy may still be possible with a low sperm count. Depending on the cause and severity, couples may consider natural conception, medical treatment, IUI, IVF or ICSI.

Can low sperm count be treated naturally?

Healthy lifestyle habits such as maintaining a healthy weight, exercising regularly, avoiding smoking and excessive alcohol consumption, eating a balanced diet, and managing stress may support overall reproductive health. However, the appropriate treatment depends on the underlying cause.

Can IVF work with low sperm count?

Yes. IVF may be an option for selected couples experiencing male-factor infertility. When significant sperm abnormalities affect fertilisation, ICSI may be performed as part of the IVF cycle.

Is ICSI better than IVF for low sperm count?

ICSI is not a separate alternative to IVF. It is a fertilisation technique performed during an IVF cycle. It may be considered when significant male-factor infertility makes conventional fertilisation less suitable.

Can pregnancy happen with very low sperm count?

Pregnancy may still be possible when very few viable sperm are available. Depending on the cause, IVF with ICSI and, in selected cases, sperm retrieval may be considered.

Is azoospermia the same as low sperm count?

No. Oligospermia means a low sperm concentration, whereas azoospermia means that no sperm are detected in the ejaculate. Azoospermia requires further evaluation to identify the possible cause.

Medical Review & Author Information

Medically Reviewed By: Imprimis IVF Fertility Specialist Team
Speciality: Reproductive Medicine, IVF & Male Infertility
Clinic: Imprimis IVF & Fertility Centre, Srinagar

This article provides general information about low sperm count, oligospermia, male infertility, semen analysis, IVF, IUI and ICSI. Fertility treatment is individualised, and diagnostic or treatment recommendations may differ depending on each patient’s medical history and fertility assessment.

Last Updated: September 2026

Conclusion

Low sperm count can be an important factor in male infertility, but it does not necessarily mean that becoming a parent is impossible.

The right approach is to identify the possible cause through semen analysis and appropriate fertility evaluation. Depending on the diagnosis, treatment may include lifestyle changes, medical management, IUI, IVF, ICSI, or sperm-retrieval procedures.

If you are searching for low sperm count treatment, consult a qualified fertility specialist to understand your diagnosis and available treatment options.

At Imprimis IVF & Fertility Centre in Srinagar, individualised fertility evaluation and treatment planning can help couples understand their options on their journey toward parenthood.

Bulky Uterus: Causes, Symptoms, Treatment & Effect on Fertility

If your ultrasound or transvaginal scan says “bulky uterus” or “enlarged uterus,” it is understandable to feel worried. However, a bulky uterus is not a diagnosis by itself. It is a description in which the uterus appears larger than expected on examination or imaging.

The important question is why the uterus is enlarged.

Conditions such as adenomyosis and uterine fibroids are common causes, although other factors may also contribute. Some women with an enlarged uterus have no symptoms and may not need treatment at all. Others may experience heavy periods, pelvic pain, pressure, or fertility problems depending on the underlying condition.

Therefore, if your ultrasound report mentions a bulky uterus, there is no need to panic. Instead, discuss the scan findings, symptoms, age, reproductive plans, and other fertility factors with a qualified gynaecologist or fertility specialist.

What Is a Bulky Uterus?

The uterus (womb) is a muscular reproductive organ located in the pelvis. Its size can vary considerably depending on factors such as age, pregnancy history, hormonal status and individual anatomy.

A bulky uterus generally means that the uterus appears enlarged on pelvic examination or imaging, such as an ultrasound scan. There is no single measurement that defines a bulky uterus for every woman because uterine size varies with age, parity, menopausal status and other factors.

More importantly, the word “bulky” does not tell you the cause.

For example, an enlarged uterus may be associated with:

  • Adenomyosis
  • Uterine fibroids
  • Pregnancy or the postpartum period
  • Less commonly, other uterine or pelvic conditions

Transvaginal ultrasound can help doctors assess the uterus, including the uterine muscle and endometrial cavity, and can identify conditions such as fibroids and adenomyosis.

Is a Bulky Uterus Always a Problem?

No.

A bulky uterus does not automatically mean cancer, infertility, or a serious disease.

Some women have an enlarged uterus with few or no symptoms. Treatment depends on the underlying cause, the severity of symptoms, whether fertility is a concern, and the woman’s reproductive plans.

For this reason, the ultrasound finding should be interpreted in the context of the complete clinical picture rather than treated as a diagnosis in itself.


Bulky Uterus Causes

Causes of Bulky Uterus

Several conditions can make the uterus appear enlarged. The most important causes include adenomyosis and uterine fibroids.

1. Adenomyosis

Adenomyosis occurs when tissue similar to the endometrium grows into the muscular wall of the uterus. This can cause the uterine muscle to become thickened and the uterus to appear enlarged or “bulky” on ultrasound.

Common symptoms can include:

  • Heavy menstrual bleeding
  • Painful periods
  • Pelvic pain
  • Abdominal bloating or heaviness
  • Pain during sex

However, some women with adenomyosis have no symptoms at all.

Adenomyosis becomes more commonly diagnosed with increasing age and is particularly seen in women over 30. Previous pregnancy may also be associated with a higher likelihood of the condition.

2. Uterine Fibroids

Uterine fibroids are non-cancerous growths that develop in or around the uterus. They can vary greatly in number, location and size.

Large or multiple fibroids can increase the overall size of the uterus.

Depending on their location and size, fibroids may cause:

  • Heavy or prolonged periods
  • Painful periods
  • Pelvic pressure or pain
  • Lower back pain
  • Frequent urination
  • Constipation or bloating
  • Pain during sex
  • Difficulty becoming pregnant in some women

However, many fibroids cause no symptoms and do not always require treatment.

3. Pregnancy and the Postpartum Period

The uterus naturally enlarges substantially during pregnancy. After childbirth, it gradually contracts toward its pre-pregnancy size.

Therefore, uterine size needs to be interpreted in the context of pregnancy status and recent childbirth. A uterus that appears enlarged during or shortly after pregnancy should not automatically be labeled abnormal.

4. Other Uterine Conditions

Less commonly, other uterine abnormalities or pelvic conditions may affect uterine size or appearance.

This is why an ultrasound report should be interpreted by a clinician who can assess the uterine shape, myometrium, endometrial cavity, and surrounding pelvic structures, rather than focusing solely on the term “bulky.”


Symptoms of Bulky Uterus


A bulky uterus itself may not cause symptoms. Symptoms usually depend on the underlying condition responsible for the uterine enlargement.

Possible symptoms include:

  • Heavy menstrual bleeding
  • Prolonged periods
  • Painful periods
  • Pelvic pain or pressure
  • Lower abdominal discomfort
  • Bloating or abdominal heaviness
  • Lower back pain
  • Pain during sexual intercourse
  • Frequent urination
  • Constipation or difficulty passing stools
  • Fatigue related to heavy menstrual blood loss

Adenomyosis, for example, commonly causes painful or heavy periods, pelvic pain, bloating or heaviness, and pain during sex.

Fibroids can also cause heavy or painful periods, pelvic or back pain, urinary symptoms, bowel symptoms and, in some women, difficulty getting pregnant.

When Should You See a Doctor?

You should consider a medical evaluation if you have:

  • Very heavy or prolonged periods
  • Severe or worsening pelvic pain
  • Bleeding between periods or after sex
  • Persistent abdominal or pelvic swelling
  • Pain during sex
  • Difficulty becoming pregnant
  • Repeated miscarriage
  • An ultrasound report showing a bulky uterus along with other abnormalities

Severe or persistent symptoms should not be ignored.


How Is a Bulky Uterus Diagnosed?

A bulky uterus is usually identified during a pelvic examination or imaging test.

Transvaginal Ultrasound

A transvaginal ultrasound (TVS) is commonly used to evaluate the uterus and ovaries. It can provide information about:

  • Uterine size
  • Uterine shape
  • Thickness and appearance of the uterine muscle
  • Endometrial lining
  • Fibroids
  • Adenomyosis
  • Ovaries and surrounding pelvic structures

ASRM notes that transvaginal ultrasound can visualize many uterine conditions, including leiomyomas (fibroids), endometrial polyps, and adenomyosis, which may be relevant when evaluating infertility.

MRI

In some situations, your doctor may recommend a pelvic MRI, particularly when ultrasound findings require further clarification.

MRI can provide additional information about the uterine muscle and may help evaluate suspected adenomyosis or other pelvic conditions.

Additional Fertility Tests

If you are trying to conceive, your doctor may recommend additional investigations depending on your history, such as:

  • Ovarian reserve testing
  • Hormonal tests
  • Semen analysis
  • Fallopian tube evaluation
  • Assessment of the uterine cavity
  • Other infertility investigations

A bulky uterus should therefore be assessed as part of the complete fertility evaluation, not in isolation.


Bulky Uterus and Infertility: Can You Get Pregnant?

Yes, many women with a bulky uterus can become pregnant.

The effect on fertility depends primarily on what is causing the uterus to enlarge.

For example, some fibroids may have little effect on fertility, while fibroids that distort the uterine cavity can be more clinically important.

Similarly, adenomyosis may be associated with fertility difficulties in some women. Current evidence suggests an association between adenomyosis and reduced implantation in certain fertility-treatment populations, although the best treatment approach before embryo transfer is still an area of ongoing research.

Therefore, the phrase “bulky uterus” does not mean “infertile.”

Your fertility specialist will consider:

  • Your age
  • Menstrual symptoms
  • Ovarian reserve
  • Ovulation
  • Sperm parameters
  • Fallopian tube status
  • Uterine cavity
  • Fibroids or adenomyosis
  • Previous pregnancy or IVF history

Can a Bulky Uterus Affect IVF Success?

A bulky uterus does not automatically prevent IVF.

However, if the enlargement is due to a condition such as adenomyosis or fibroids, the underlying condition may need to be evaluated before treatment.

For example, fibroids can sometimes affect fertility depending on their size and location. Adenomyosis has also been associated with reduced implantation and fertility-treatment outcomes in some studies.

The appropriate IVF plan therefore depends on the individual patient.

In some cases, treatment may be recommended before embryo transfer. In others, especially when the patient has no significant symptoms or the uterine cavity is not affected, immediate treatment may not be necessary.


Treatment of Bulky Uterus


There is no single treatment for a bulky uterus.

Treatment depends on the cause, symptoms, age, fertility plans, and severity of the condition.

Treatment for Uterine Fibroids

If fibroids are small and asymptomatic, treatment may not be necessary.

When symptoms are significant, treatment options may include:

  • Pain-relieving medicines
  • Medicines to reduce heavy menstrual bleeding
  • Hormonal treatments in selected patients
  • Myomectomy to remove fibroids
  • Other procedures depending on the location and size of the fibroids

The treatment choice is highly individual. Women who want future pregnancy require a different treatment discussion from those who have completed their family.

Treatment for Adenomyosis

Treatment for adenomyosis depends on symptoms and reproductive goals.

Depending on the individual situation, doctors may consider:

  • Pain-relieving medicines
  • Medicines to reduce heavy menstrual bleeding
  • Hormonal treatment
  • An intrauterine system in appropriate patients
  • Other specialist treatments
  • Surgery in selected severe cases

A hysterectomy removes the uterus and therefore ends the possibility of carrying a future pregnancy, so it is generally considered only in appropriate circumstances, particularly when other treatments have not worked and pregnancy is no longer desired.


Bulky Uterus Treatment for Women Trying to Conceive

If you are trying to become pregnant, treatment needs to balance symptom control with fertility preservation.

For example, a fertility specialist may first determine:

  1. Why the uterus is enlarged
  2. Whether the uterine cavity is distorted
  3. Whether fibroids are present
  4. Whether adenomyosis is suspected
  5. Whether the fallopian tubes are open
  6. Whether ovulation is occurring normally
  7. Whether there are male-factor fertility issues
  8. Whether IVF or another fertility treatment is appropriate

Not every woman with a bulky uterus needs surgery.

In fact, unnecessary treatment can be avoided when the underlying condition is mild and does not interfere with fertility or cause significant symptoms.


Can Diet and Exercise Cure a Bulky Uterus?

A healthy lifestyle is beneficial for overall reproductive and general health, but diet and exercise cannot be considered a cure for an enlarged uterus caused by fibroids or adenomyosis.

A balanced diet, regular physical activity, adequate sleep, and maintaining a healthy weight can support general health. However, they should not replace medical evaluation or treatment when symptoms are present.

If you have heavy bleeding, pelvic pain, or fertility problems, speak with a gynecologist or fertility specialist rather than relying only on dietary changes.


Bulky Uterus: When Is It a Concern?

A bulky uterus deserves closer evaluation when it is associated with:

  • Heavy menstrual bleeding
  • Severe period pain
  • Persistent pelvic pain
  • Rapidly increasing abdominal or pelvic swelling
  • Fibroids
  • Suspected adenomyosis
  • Abnormal uterine bleeding
  • Difficulty conceiving
  • Recurrent pregnancy loss
  • Abnormal findings involving the uterine cavity

On the other hand, an incidental finding of a mildly enlarged uterus does not necessarily mean that you have a serious condition.

The cause matters more than the word “bulky.”


Frequently Asked Questions About Bulky Uterus

Is a bulky uterus dangerous?

Not necessarily. “Bulky uterus” is an imaging description rather than a diagnosis. The significance depends on the cause of the enlarged uterus and whether you have symptoms or other abnormal findings.

Can a bulky uterus cause infertility?

Sometimes, depending on the underlying cause. Fibroids that affect the uterine cavity and adenomyosis may be relevant to fertility in some women. However, having a bulky uterus does not automatically mean infertility.

Can I get pregnant with a bulky uterus?

Yes. Many women with an enlarged uterus can conceive. Your individual fertility outlook depends on the underlying cause, age, ovarian function, sperm quality, fallopian tubes, and uterine anatomy.

Does a bulky uterus mean adenomyosis?

No. Adenomyosis is one possible cause of an enlarged or bulky uterus, but fibroids and other conditions can also cause uterine enlargement. Ultrasound and, when necessary, MRI can help evaluate the cause.

Does a bulky uterus mean fibroids?

No. Fibroids can enlarge the uterus, but a bulky uterus does not automatically mean that fibroids are present. An ultrasound can help identify fibroids and describe their number, size, and location.

Can a bulky uterus affect IVF treatment?

It can, depending on the underlying condition. For example, some fibroids or adenomyosis may affect fertility treatment outcomes. Your fertility specialist can determine whether the uterus requires treatment or monitoring before embryo transfer.

Is surgery always needed for a bulky uterus?

No. Treatment is not automatically required simply because an ultrasound describes the uterus as bulky. Treatment depends on symptoms, the underlying cause, fertility plans, and other clinical findings.

Which test is best for a bulky uterus?

A transvaginal ultrasound is commonly used as an initial evaluation because it can assess the uterus, endometrium and surrounding pelvic structures. MRI may be recommended when additional evaluation is needed.


Bulky Uterus: The Bottom Line

Seeing the words **“bulky uterus” on an ultrasound report can be worrying, but the term itself does not tell you whether you have a serious condition or whether you will have difficulty becoming pregnant.

The next step is to identify the underlying cause.

Adenomyosis and uterine fibroids are important causes of an enlarged uterus, but not every bulky uterus requires treatment. A doctor may recommend monitoring, medicines, further imaging, or fertility-focused treatment depending on your symptoms and reproductive goals.

If you are trying to conceive and your ultrasound has reported a bulky or enlarged uterus, a fertility evaluation can help determine whether the finding is relevant to your fertility and whether any treatment is necessary.

Related Fertility Resources

Medical Reviewer: Imprimis IVF & Fertility Centre
Last Updated: September 2026

Clinic: Imprimis IVF & Fertility Centre, Srinagar
Address: Second Floor, S R Plaza, Hyderpora Flyover, Hyderpora, Srinagar, Jammu and Kashmir – 190014
Phone: 7678556881, 9650777084